Related Experiment Video
Updated: Aug 15, 2026

Treating Low Back Pain in Failed Back Surgery Patients with Multicolumn-lead Spinal Cord Stimulation
Published on: June 26, 2018
Case Report: Single-access epidural adhesiolysis and catheter-delivered pulsed radiofrequency for refractory failed
Rafael Nascimento1,2,3
1Faculty of Medicine, Federal University of Mato Grosso do Sul (UFMS), Campo Grande, MS, Brazil.

Abstract:
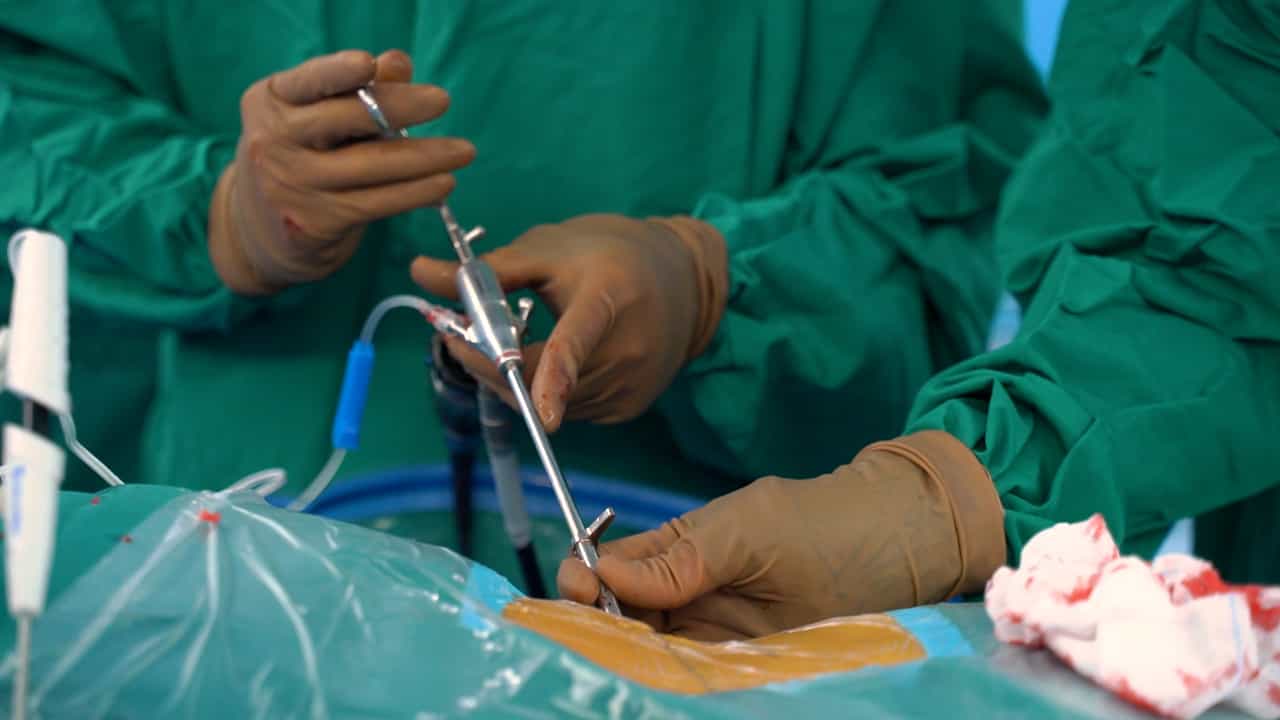
Failed back surgery syndrome (FBSS) frequently involves mixed mechanical, inflammatory, and neuropathic mechanisms and remains challenging to treat, particularly when systemic anti-inflammatory therapy is limited. We report a 55-year-old woman with chronic refractory left lumbosciatica after endoscopic lumbar discectomy and L3-L4 arthrodesis, with established coronary artery disease and prior myocardial infarction limiting the use of nonsteroidal anti-inflammatory drugs (NSAIDs). Lumbar magnetic resonance imaging demonstrated prior L3-L4 arthrodesis, multilevel degenerative disc disease, and an L4-L5 diffuse disc protrusion causing dural-sac compression, degenerative central canal narrowing, and bilateral foraminal narrowing; lower-limb electroneuromyography did not show active large-fiber radiculopathy. A single-session, single-access caudal procedure was performed using a radiopaque steerable epidural catheter-electrode system, allowing both catheter-directed adhesiolysis and sequential epidural pulsed radiofrequency (PRF) delivery through the catheter tip adjacent to the left S1, L5, L4, and L3 dorsal root ganglion/nerve-root regions. At 5 days, the patient reported approximately 60% improvement in the radiating lower-limb pain. At 8 weeks, she reported approximately 70% improvement in the radicular pain component, while overall pain intensity decreased from NRS 9/10 to 5/10, with residual axial low back pain. A transient sacral neuritis with gluteal paresthesia was the only adverse event and resolved with conservative treatment. This case illustrates a combined interventional strategy for selected patients with refractory FBSS, while the single-case, multicomponent design precludes attribution of benefit to any individual element.