Related Experiment Video
Updated: Aug 16, 2026
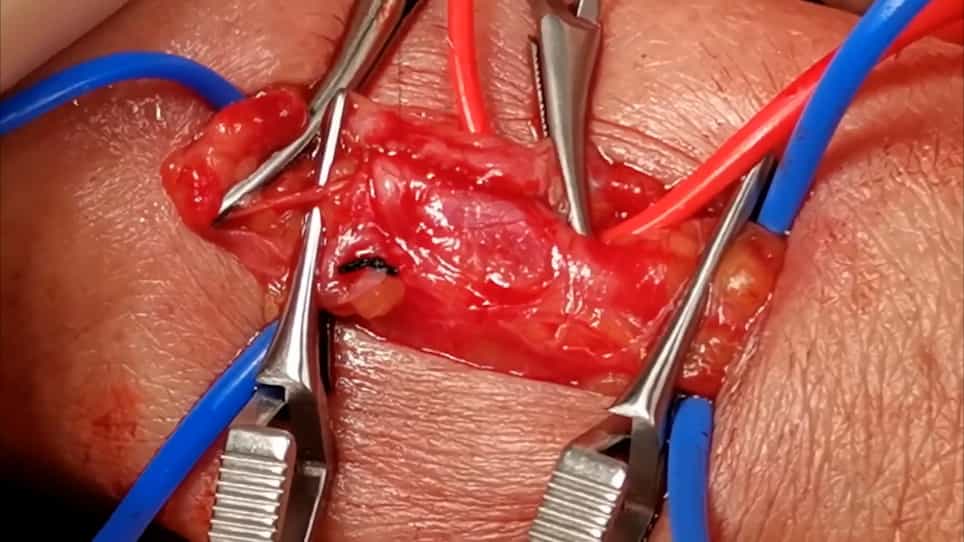
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Association between the CT myelography-based Duke cerebrospinal fluid venous fistula confidence score and outcomes
Bikei Ryu1,2,3, Emanuele Orru4, Neil V Patel4
1Neurointerventional Radiology, Lahey Clinic, Burlington, Massachusetts, USA ryu.bikei@twmu.ac.jp.

Insights
The CT myelography (CTM)-based Duke CSF-Venous Fistula Confidence Score (DCCS) helps predict treatment response in spontaneous intracranial hypotension (SIH). High-confidence scores indicate better outcomes after transvenous embolization (TVE), while renal contrast may aid equivocal cases.
Area of Science:
- Neurosurgery
- Interventional Radiology
- Diagnostic Imaging
Background:
- Spontaneous intracranial hypotension (SIH) diagnosis relies on identifying cerebrospinal fluid-venous fistulas (CVFs).
- The CT myelography (CTM)-based Duke CSF-Venous Fistula Confidence Score (DCCS) standardizes CVF assessment.
- Evaluating DCCS categories' association with transvenous embolization (TVE) response and renal contrast utility is crucial.
Purpose of the Study:
- To assess if DCCS confidence categories correlate with clinical improvement after TVE for CVFs in SIH patients.
- To determine if renal contrast accumulation offers additional prognostic value in equivocal CVF cases.
Main Methods:
- Retrospective single-center cohort study of SIH patients undergoing TVE.
- Patients categorized into definite, high-probability, or low-probability DCCS groups based on pretreatment CTM.
- Primary outcome: overall clinical improvement at 3 months; secondary: renal contrast accumulation as an adjunctive marker.
Main Results:
- Overall clinical improvement was observed in 69.8% of patients.
- Improvement rates varied significantly by DCCS category (80.0% definite, 83.3% high-probability, 47.6% low-probability; p=0.02).
- High-confidence DCCS findings were independently associated with improved outcomes (aOR 4.47; p=0.03). Renal contrast showed similar discrimination but higher sensitivity in a modified model.
Conclusions:
- DCCS categories are associated with TVE treatment response in SIH patients.
- Low-probability DCCS cases show less predictable but still significant improvement rates.
- Renal contrast accumulation may offer adjunctive prognostic information in equivocal CVF diagnoses, warranting prospective validation.
Background:
The CT myelography (CTM)-based Duke CSF-Venous Fistula Confidence Score (DCCS) standardizes diagnostic assessment of suspected CSF-venous fistulas (CVFs) in spontaneous intracranial hypotension (SIH). We evaluated whether confidence categories are associated with response after transvenous embolization (TVE), and whether renal contrast accumulation adds prognostic information in equivocal cases.
Methods:
This retrospective, single-center cohort included patients with SIH attributed to suspected or confirmed CVFs who underwent TVE between May 2023 and January 2026. Based on the DCCS, pretreatment CTM studies were categorized as definite, high-probability, or low-probability groups. The primary outcome was overall clinical improvement, defined as complete or partial symptom improvement without additional intervention at 3 months. Renal contrast accumulation was evaluated as an adjunctive marker.
Results:
Overall clinical improvement occurred in 44/63 patients (69.8%), including complete resolution in 32 (50.8%) and partial improvement in 12 (19.0%). Improvement rates differed by Duke category: 24/30 (80.0%) in the definite, 10/12 (83.3%) in the high-probability, and 10/21 (47.6%) in the low-probability group (p=0.02). High-confidence CTM findings (comprising definite and high-probability) remained independently associated with overall improvement after adjustment for preoperative Bern score (adjusted OR 4.47; 95% CI 1.15 to 20.19; p=0.03). A renal accumulation modified model showed similar discrimination to conventional CTM grading (area under the curve (AUC) 0.691 vs 0.683; p=0.87), but lower corrected Akaike Information Criterion (AICc)/Bayesian Information Criterion (BIC) and higher sensitivity (90.9% vs 77.2%).
Conclusions:
The CTM-based DCCS categories were associated with response after TVE. Low-probability cases had less predictable outcomes but improved in nearly half of patients. Renal contrast accumulation may provide adjunctive information in equivocal cases but requires prospective validation.
