Related Experiment Video
Updated: Aug 16, 2026
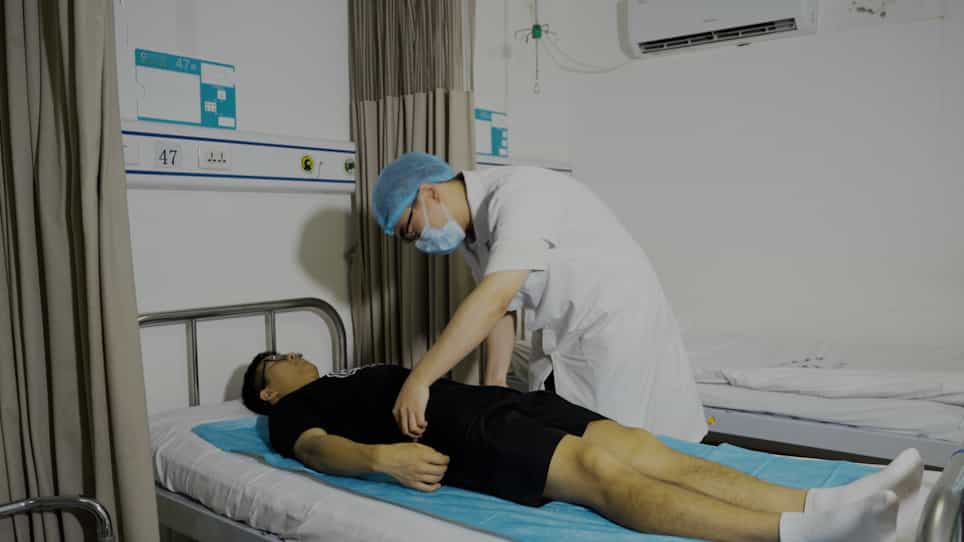

Acupoint Needle-Embedding Combined with Ironing Therapy for Postoperative Pain After Anal Surgery
Published on: June 23, 2023
Effects of Preemptive Analgesia Using Wrist-Ankle Acupuncture on Postoperative Pain and Urinary Retention After
Pingping He1, Jie Kong1, Long Peng1
1Anorectal Department of Jiangsu Province Hospital of Chinese Medicine, Affiliated Hospital of Nanjing University of Chinese Medicine, Nanjing, Jiangsu, People's Republic of China.

Objective:
To evaluate the clinical efficacy of wrist-ankle acupuncture (WAA) at different time points for pain after haemorrhoidectomy and to identify an optimized analgesic strategy.
Methods:
Patients undergoing haemorrhoidectomy between June 2024 and March 2025 were randomly assigned to three groups: control (n=96, conventional care), immediate analgesia (n=89, WAA at lower zone 6 upon first pain [VAS≥1]), and preemptive analgesia (n=90, WAA at lower zone 6 within 1 hour postoperatively before pain onset). Needle retention was 6 hours in both intervention groups. Primary outcomes were 24-hour pain trajectory, cumulative pain burden (AUC), and peak VAS. Secondary outcomes included postoperative urinary retention (POUR) and additional analgesic requirement.
Results:
From 6 to 24 hours postoperatively, the preemptive group consistently showed lower VAS scores than the control and immediate groups. Both intervention groups reduced AUC versus control, with the preemptive group achieving the lowest burden (mean AUC=44.10, 95% CI: 39.08-49.11), representing a 24.5% reduction compared with controls (mean AUC=58.44, 95% CI: 53.67-63.21; MD=-14.34). Peak VAS was lower in the preemptive group versus controls (MD=-0.64, P=0.012), but no significant difference was observed between the immediate and control groups (MD=-0.32, P=0.453). Preemptive analgesia significantly reduced POUR incidence (14.44% vs 29.17% in controls; adjusted OR=0.38, 95% CI: 0.17-0.80). Both intervention groups required fewer additional analgesics than controls (35.42% rescue rate), with the greatest reduction in the preemptive group (13.33%; adjusted OR=0.25, 95% CI: 0.11-0.52), followed by the immediate group (22.47%; adjusted OR=0.46, 95% CI: 0.23-0.90). In patients stratified by types of basic analgesics (Med1 (Flurbiprofen Esters Injection) and Med2 (Parecoxib sodium for injection) subgroups), the preemptive analgesia group consistently showed significantly lower VAS scores (P < 0.01). During the treatment period, no cases of fainting (needle syncope) or subcutaneous haemorrhage occurred in any group.
Conclusion:
Preemptive WAA within 1 hour postoperatively reduces 24-hour pain, cumulative pain burden, peak VAS, POUR incidence, and additional analgesic requirement, with a favourable safety profile. It represents a promising non-pharmacological adjunct for multimodal perioperative care; however, multi-centre trials are needed to confirm its generalisability before routine adoption.
Chinese Clinical Trials Register Identifier:
ChiCTR2400084402.