Related Experiment Videos
A double-hit analysis: Evaluating the nephrotoxicity of dual intravenous and vancomycin impregnated cement exposure
Natalie H Vu1, Garrett W Esper1, Kenneth A Egol2
1Division of Orthopedic Trauma Surgery, NYU Langone Orthopedic Hospital, New York, NY 10003, USA.

Purpose:
The concomitant use of postoperative intravenous vancomycin (IVV) in patients treated with vancomycin-impregnated cement (VIC) may represent a "double hit" contributing to nephrotoxicity, yet its impact on acute kidney injury (AKI) remains unclear. This study evaluated whether postoperative IVV in patients treated with VIC is associated with increased AKI incidence (primary outcome) and greater changes in serum creatinine (secondary outcome) compared with VIC alone.
Methods:
A retrospective cohort study was conducted at a multi-hospital academic health system from 2012 to 2024. Adults undergoing VIC implantation for fracture-related infection were grouped by postoperative IVV exposure (IVV+VIC versus VIC alone). AKI was defined using Kidney Disease: Improving Global Outcomes (KDIGO) creatinine-based criteria. Secondary outcomes included mean absolute and percent serum creatinine change. A subgroup analysis evaluated 81 patients with chronic kidney disease (CKD). Multivariable regression adjusted for baseline creatinine, tobramycin dose, CKD, ASA class, and VIC dose.
Results:
A total of 589 patients were included: 326 (55.4%) received IVV + VIC and 263 (44.6%) received VIC alone, with similar baseline characteristics. Among IVV + VIC patients, mean IV vancomycin dose was 1160 mg (SD 354) over a mean of 6.6 doses (SD 7.6), with a mean VIC dose of 4.9 g (SD 3.3). The VIC alone group had a mean VIC dose of 4.3 g (SD 3.3). AKI incidence did not differ between groups (18.1% vs 14.5%, p = 0.282). However, IVV + VIC was associated with greater mean absolute (0.19 vs 0.00 mg/dL, p < 0.001) and percent serum creatinine change (17.98 vs -0.86). Among CKD patients, AKI rates were similarly elevated in both cohorts (56.8% vs 40.5%, p = 0.216). On multivariable analysis, IVV + VIC was not independently associated with AKI (OR=1.37, 95% CI 0.84-2.23, p = 0.207) but was associated with greater absolute (β = 0.182, 95% CI 0.082-0.282, p < 0.001) and percent creatinine change (β = 17.683, 95% CI 9.659-25.706, p < 0.001).
Conclusion:
Postoperative IV vancomycin in patients treated with vancomycin-impregnated cement was not associated with increased AKI risk. While dual antibiotic therapy resulted in greater creatinine elevations, AKI risk appeared driven primarily by underlying renal disease. These findings support cautious use of dual therapy with close renal monitoring, particularly in patients with pre-existing CKD.
Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:15
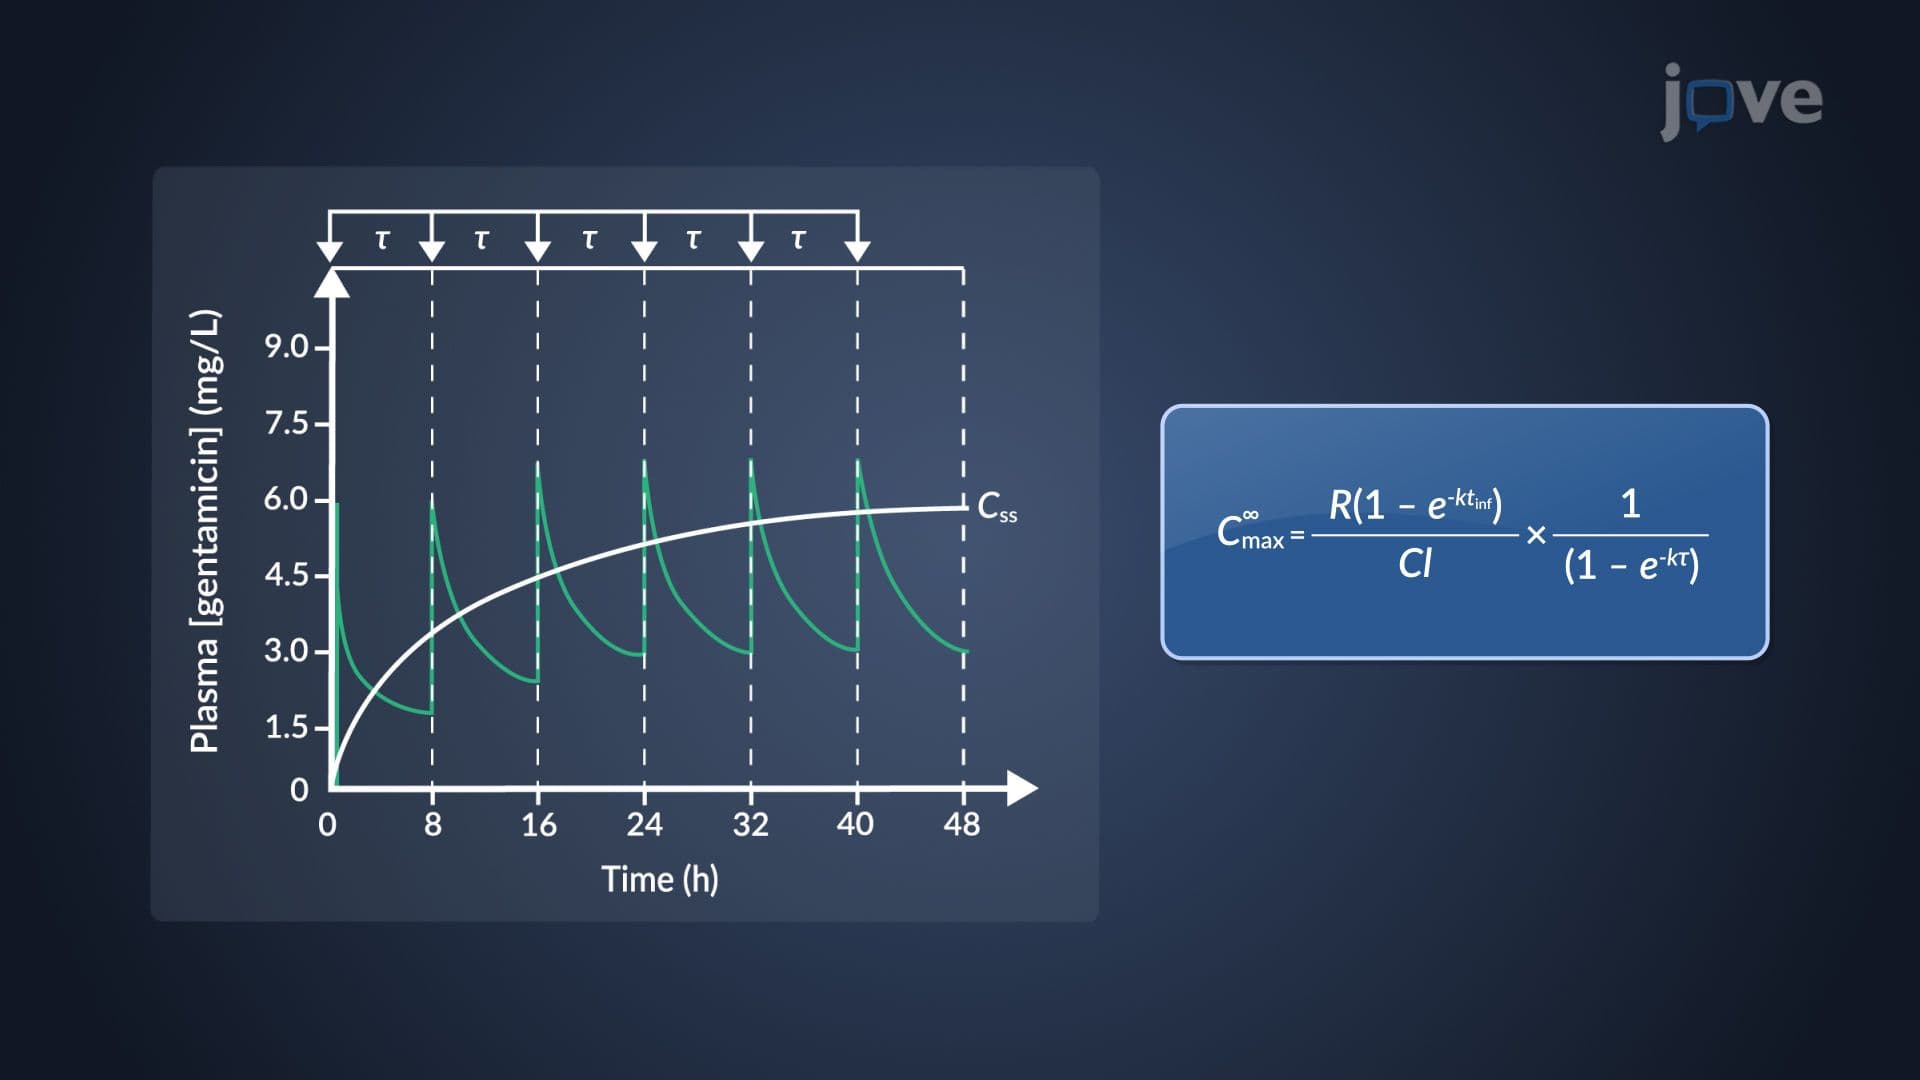
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Kidney Transplant II: Surgical Procedure
 01:19
Imaging Studies VII: Vascular Imaging
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography