Related Experiment Video
Updated: Aug 17, 2026
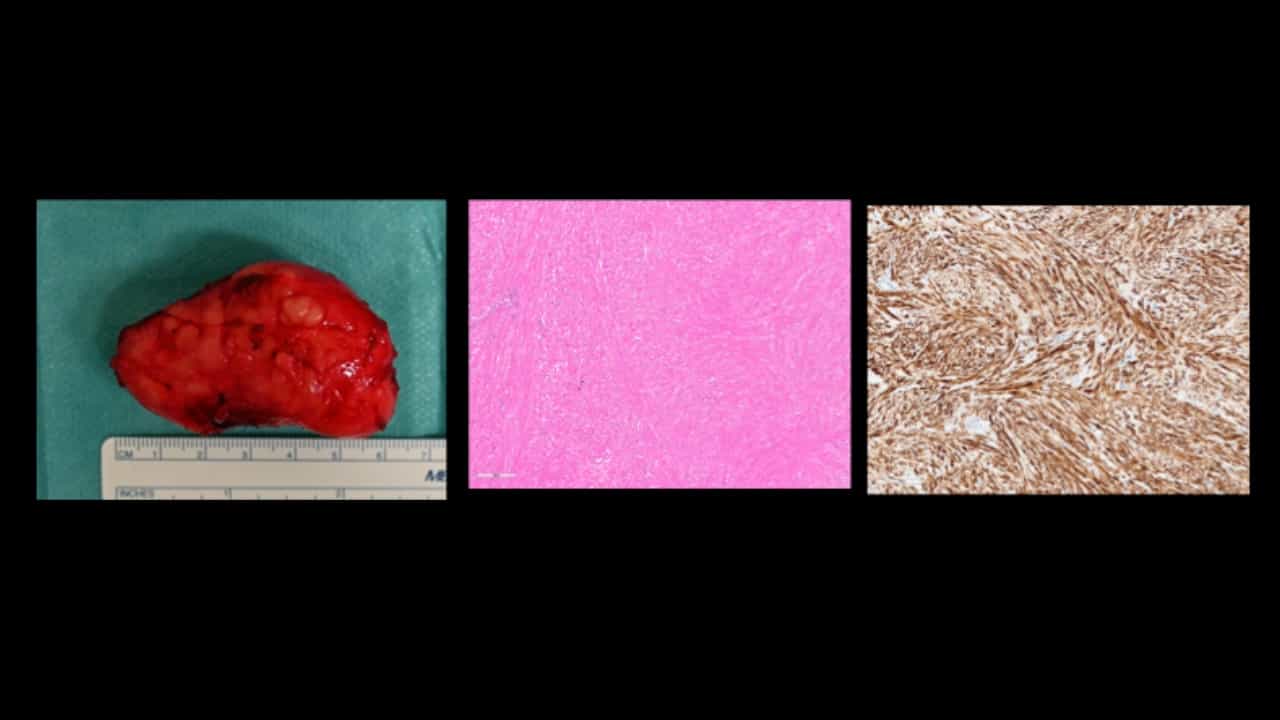

Robotic Enucleation of Esophageal Leiomyoma
Published on: February 20, 2026
Robotic-assisted versus video-assisted thoracoscopic enucleation for esophageal leiomyoma: A propensity-weighted
Hengxuan Xu1,2, Weidong Hu1
1Department of Thoracic Surgery, ZhongNan Hospital of Wuhan University, Wuhan, Hubei, China.

Objective:
The study objective was to compare recovery, operative outcomes, and direct in-hospital costs between robotic-assisted thoracic surgery and video-assisted thoracoscopic surgery for minimally invasive enucleation of esophageal leiomyoma.
Methods:
This was a single-center retrospective cohort (January 2017 to September 2025). The primary end point was postoperative length of stay. Adjusted comparisons used stabilized inverse probability of treatment weighting from a prespecified propensity score model.
Results:
Sixty-one patients were included (23 robotic-assisted; 38 video-assisted). In propensity-weighted analyses (robotic-assisted thoracic surgery - video-assisted thoracoscopic surgery), robotic-assisted thoracic surgery was associated with shorter postoperative length of stay (-0.85 days [-1.53 to -0.16]; P = .015), earlier chest drain removal (-0.83 days [-1.30 to -0.35]; P < .001), and lower estimated blood loss (-31.51 mL [-41.02 to -22.00]; P < .001), whereas total length of stay was similar (-0.81 days [-2.19 to 0.57]; P = .253) and direct in-hospital cost was higher (15,895 Chinese yuan [13,126-18,664; P < .001). Adverse events were infrequent. Length of stay end points were interpreted within a standardized institutional pathway.
Conclusions:
In this small single-center cohort, robotic-assisted thoracic surgery was associated with shorter selected recovery milestones at higher direct in-hospital cost. These hypothesis-generating findings describe local trade-offs rather than definitive evidence of platform superiority or subgroup selection.
