Related Experiment Video
Updated: Aug 19, 2026

Breathing-controlled Electrical Stimulation (BreEStim) for Management of Neuropathic Pain and Spasticity
Published on: January 10, 2013
Ventral cervical epidural electrical stimulation failed to increase respiratory activity in anesthetized humans
Ruyi Huang1,2,3, Yan Zhou1,2, Jordan Peyer1,2
1Department of Neurosurgery, David Geffen School of Medicine, University of California, Los Angeles, California, United States.

Abstract:
Respiratory depression is the leading cause of death during opioid overdoses. Epidural electrical stimulation (EES) may facilitate rhythmic motor activities such as locomotion and respiration. We investigated whether tonic, submotor threshold, EES of the ventral cervical spinal cord would activate muscles innervated by motor neurons outside the ventral cervical spinal site of stimulation and increase tidal volume, respiratory frequency, and decrease end-tidal Pco2, or activate a more restricted set of muscles innervated by motor neurons near the stimulating electrodes. We studied 24 patients who were anesthetized with propofol and low-dose or high-dose remifentanil for treatment of anterior cervical spinal impingement. Cervical EES was delivered between cervical levels 3 to 7 (C3 to C7) for up to 90 s at an intensity ranging from 0.5 mA to 5 mA and a frequency of 5, 30, or 90 Hz at each dose of remifentanil. Ventral cervical EES did not reset the respiratory rhythm. There were no significant changes, on average, in tidal volume, respiratory frequency, or end-tidal Pco2 during or after ventral cervical EES. In contrast, dorsal cervical EES reset the respiratory rhythm, augmented respiratory activity beyond the period of stimulation, and increased both tidal volume and respiratory frequency and decreased end-tidal Pco2 in a similar, previous study in anesthetized humans. These observations suggest that the mild to moderate intensity, ventral cervical EES at frequencies < 100 Hz cannot access ventral motor neurons directly or activate interneuronal circuits that might increase motor neuron output indirectly during opioid-induced respiratory depression.NEW & NOTEWORTHY Submotor threshold, dorsal cervical epidural stimulation increased ventilation during opioid-induced respiratory depression by augmenting afferent information that accessed the pontomedullary and spinal circuits driving respiratory motor neurons. Ventral cervical epidural stimulation was unable to achieve a similar effect; ventral stimulation, at the field strength and frequencies tested, did not access or augment ventral respiratory motor neurons during opioid-induced respiratory depression.

Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:28
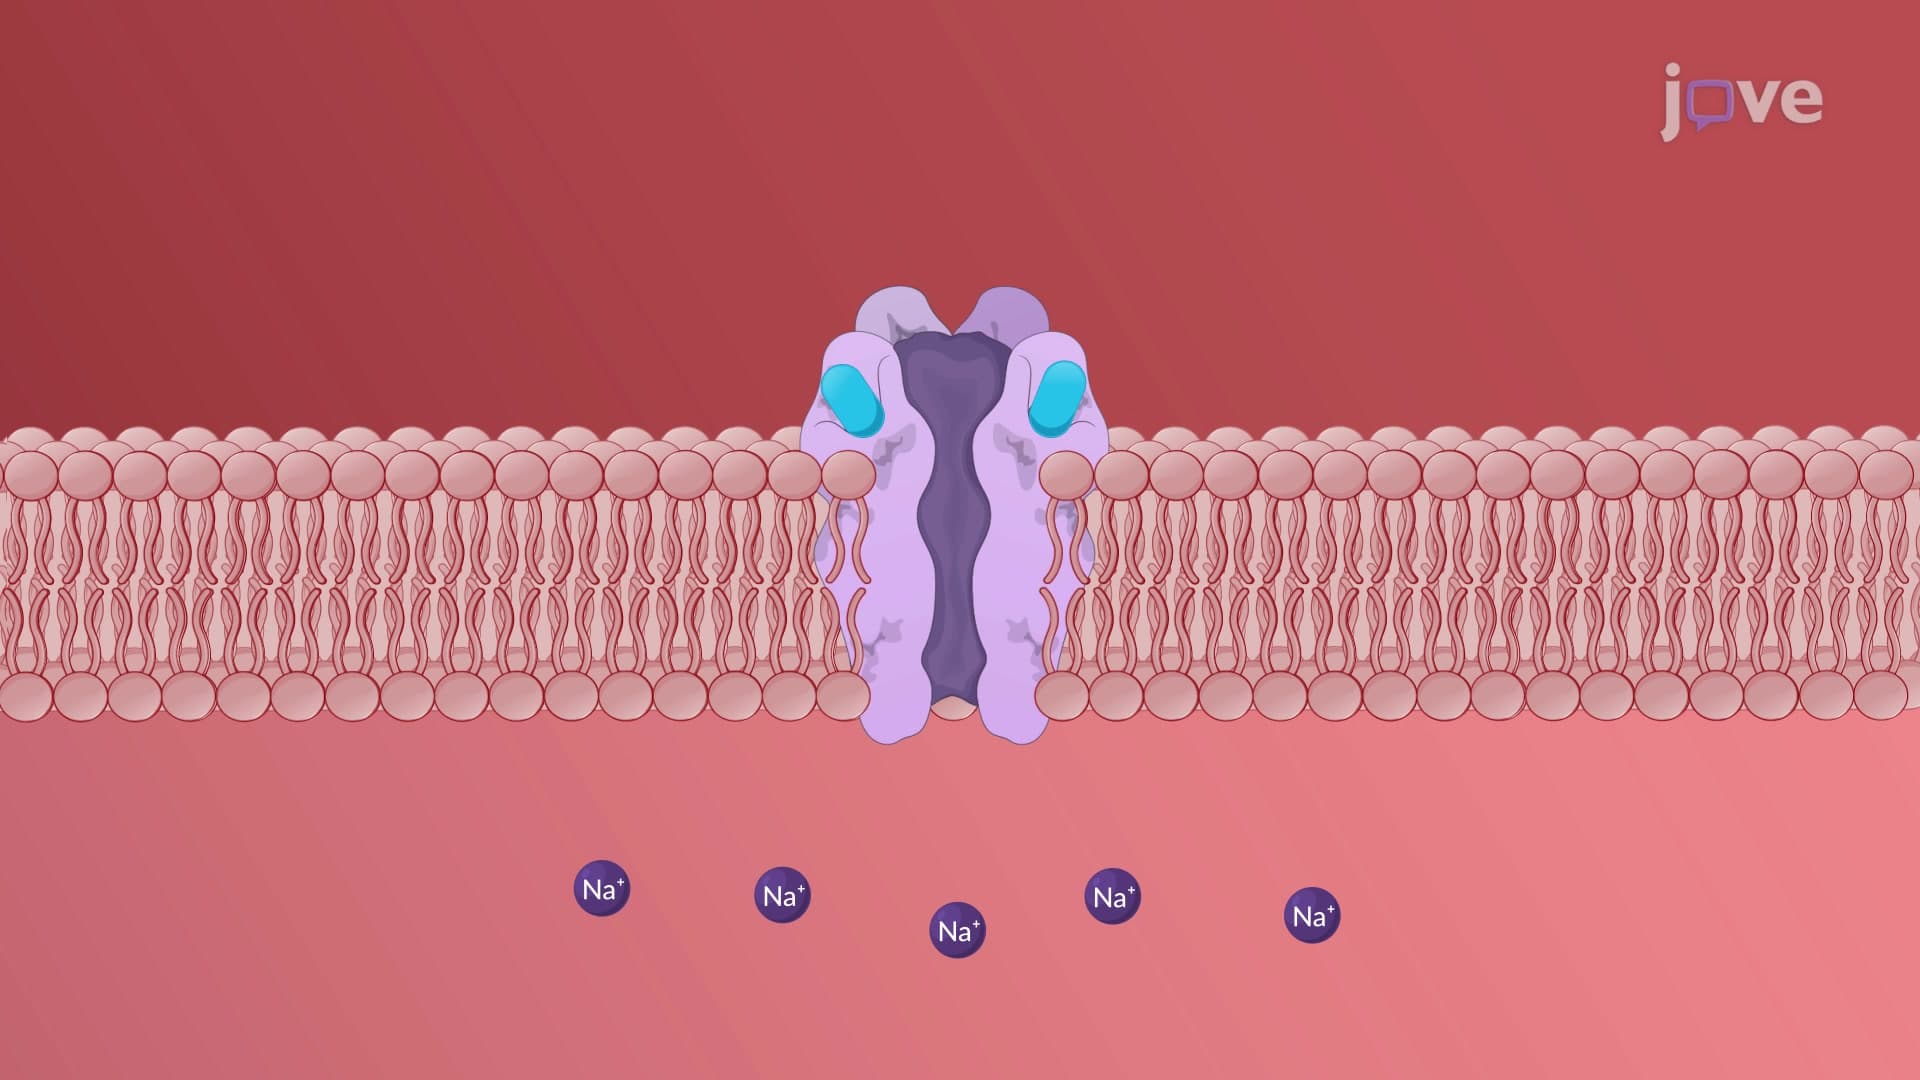
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management