Related Experiment Video
Updated: Aug 21, 2026
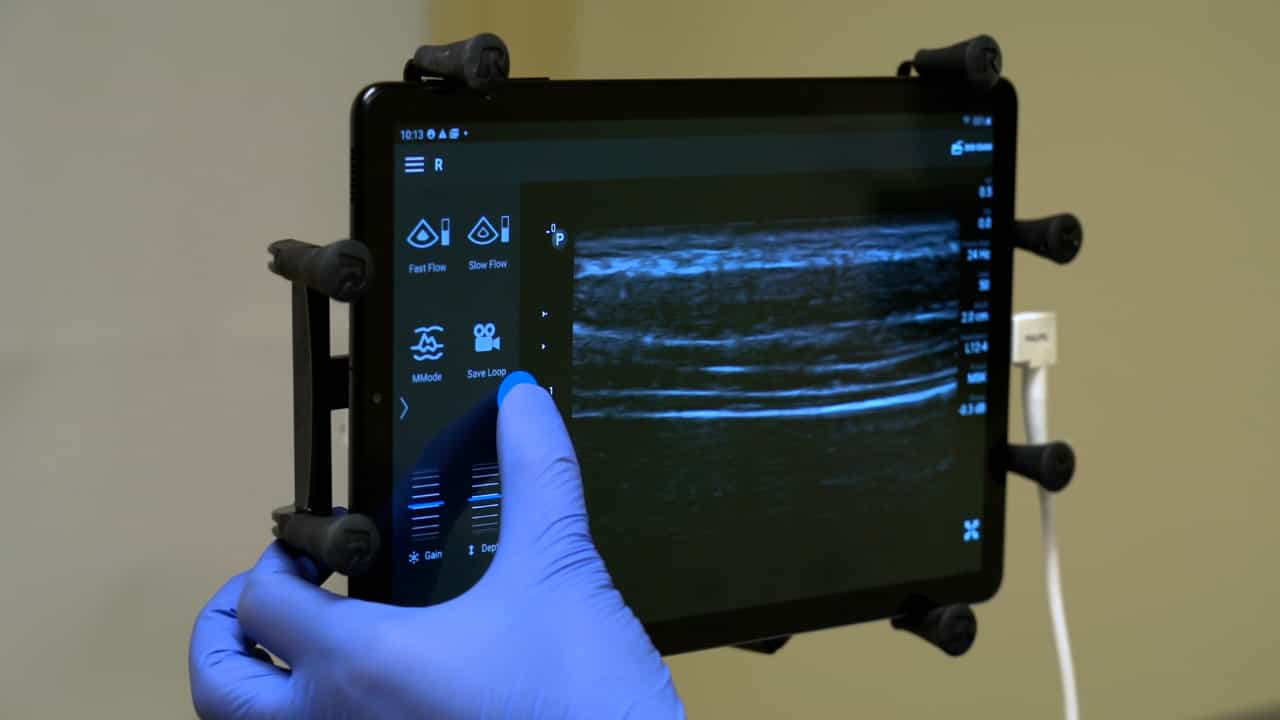

Measuring Diaphragm Thickness and Function Using Point-of-Care Ultrasound
Published on: November 3, 2023
Diaphragm ultrasound parameters and rapid shallow breathing index for predicting weaning failure in mechanically
Marwa Ibrahem Abdelrazic1, Reham Mohamed Mokhtar2, Ahmed Hussein Ahmed3
1Department of Pediatrics, Faculty of Medicine, Minia University, Minya, Egypt. marwa.ibrahem@minia.edu.eg.

Abstract:
Weaning from mechanical ventilation in infants admitted to the pediatric intensive care unit remains a challenging clinical decision. Premature extubation may lead to respiratory failure and reintubation, whereas delayed weaning may prolong exposure to invasive ventilation and its complications. Bedside transthoracic ultrasound may provide an objective assessment of diaphragmatic function during spontaneous breathing trials. This study aimed to evaluate the value of diaphragm ultrasound-derived parameters and the rapid shallow breathing index in predicting weaning failure among mechanically ventilated infants in the PICU. This prospective observational study included 40 mechanically ventilated infants aged 28 days to 12 months who were admitted to the PICU of Minia University Children and Maternity Hospital between January 2024 and January 2025 and were considered ready for weaning assessment. Diaphragmatic thickness at inspiration, diaphragmatic thickness at expiration, diaphragm thickening fraction, inferior vena cava diameter, contractility, and rapid shallow breathing index were assessed during the spontaneous breathing trial. The primary outcome was weaning failure, defined as the requirement for post-extubation noninvasive ventilation or reintubation within 24-72 h after extubation. Successful weaning occurred in 34 infants (85.0%) and weaning failure in 6 (15.0%). Infants with weaning failure had significantly lower diaphragmatic thickness at inspiration [1.65 (1.61-1.66 mm) vs. 1.83 (1.79-1.92 mm), P < 0.001] and lower diaphragm thickening fraction [12.0 (11.3-13.5%) vs. 26.0 (23.0-28.0%), P < 0.001] than successfully weaned infants. RSBI was significantly higher in the weaning failure group [9.0 (9.0-9.8) vs. 7.0 (6.0-7.0), P < 0.001]. Diaphragmatic thickness at expiration, inferior vena cava diameter, and contractility did not differ significantly between groups. In this small cohort with only six weaning failure events, apparent ROC AUCs were 0.998 for diaphragmatic thickness at inspiration and 1.000 for both diaphragm thickening fraction and RSBI. After leave-one-out cross-validation of the sample-derived cutoffs, sensitivity/specificity was 83.3%/97.1% for diaphragmatic thickness at inspiration, 83.3%/100.0% for diaphragm thickening fraction, and 100.0%/100.0% for RSBI.
Conclusion:
In this small single-center cohort with only six weaning failure events, lower diaphragm thickening fraction and diaphragmatic thickness at inspiration, together with higher RSBI, were strongly associated with weaning failure. These findings and the sample-derived cutoffs should be considered exploratory and require external validation in larger multicenter cohorts before routine clinical application.
What Is Known:
• Weaning mechanically ventilated infants is challenging, and failed or delayed extubation may increase morbidity. • Diaphragm ultrasound and RSBI may support weaning assessment, but infant-specific evidence remains limited.
What Is New:
• Lower inspiratory diaphragm thickness, lower diaphragm thickening fraction, and higher RSBI were associated with weaning failure. • Leave-one-out validation retained 100% sensitivity and specificity for RSBI but reduced sensitivity to 83.3% for diaphragmatic thickness at inspiration and diaphragm thickening fraction, underscoring the need for external validation.

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:10
Atelectasis II: Pathophysiology
 01:23
Acute Respiratory Failure-IV