Related Experiment Video
Updated: Aug 21, 2026

Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
Sixth Cranial Nerve Paresis Secondary to Intracranial Hypotension: Etiology, Clinical Characteristics, and Treatment
Pilar Merino1, Ariana Fuentes2, Lourdes Bermejo2
1Ocular Motility Section, Gregorio Marañón University General Hospital, Madrid.

Intracranial hypotension is a typically self-limiting or treatable condition characterized by orthostatic headache and neck stiffness. However, it may be severe and may be associated with neurological complications, particularly sixth cranial nerve palsy. We report two young women who presented to the emergency department with diplopia secondary to acute unilateral sixth cranial nerve paresis in the context of intracranial hypotension following anesthetic procedures. In both cases, clinical and radiological findings consistent with a cerebrospinal fluid (CSF) deficit were documented, including bilateral subdural collections in one case. One case required an epidural blood patch, which resulted in complete resolution, whereas the other resolved spontaneously. The clinical manifestations, radiological findings, and therapeutic options are reviewed. These cases underscore the importance of careful clinical and radiological assessment in patients with acute ophthalmoplegia, in whom orthostatic headache is a key diagnostic clue, as well as of treatment aimed at correcting the CSF deficit.
Intracranial hypotension is a typically self-limiting or treatable condition characterized by orthostatic headache and neck stiffness. However, it may be severe and may be associated with neurological complications, particularly sixth cranial nerve palsy. We report two young women who presented to the emergency department with diplopia secondary to acute unilateral sixth cranial nerve paresis in the context of intracranial hypotension following anesthetic procedures. In both cases, clinical and radiological findings consistent with a cerebrospinal fluid (CSF) deficit were documented, including bilateral subdural collections in one case. One case required an epidural blood patch, which resulted in complete resolution, whereas the other resolved spontaneously. The clinical manifestations, radiological findings, and therapeutic options are reviewed. These cases underscore the importance of careful clinical and radiological assessment in patients with acute ophthalmoplegia, in whom orthostatic headache is a key diagnostic clue, as well as of treatment aimed at correcting the CSF deficit.
Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:26
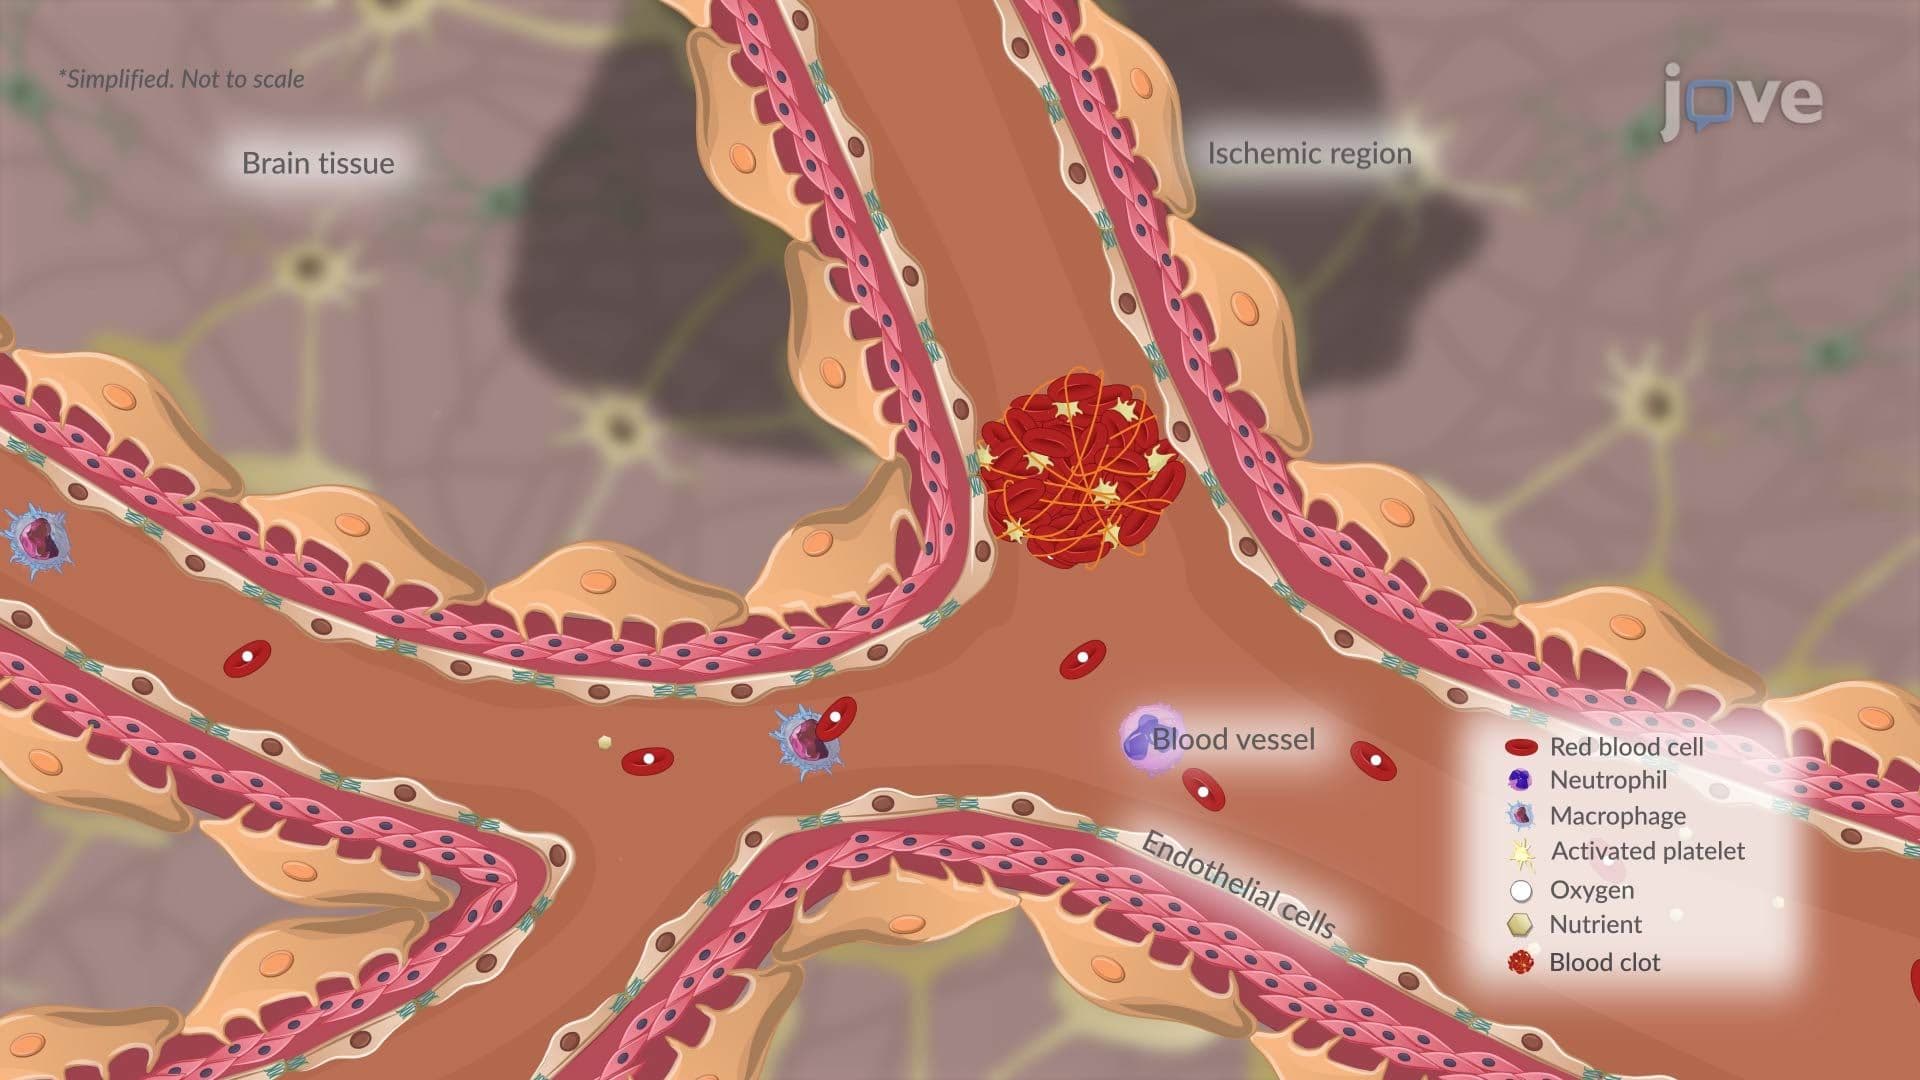
Transient Ischemic Attack l: Introduction
 01:14
Increased Intracranial Pressure l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies