Related Experiment Video
Updated: Aug 21, 2026
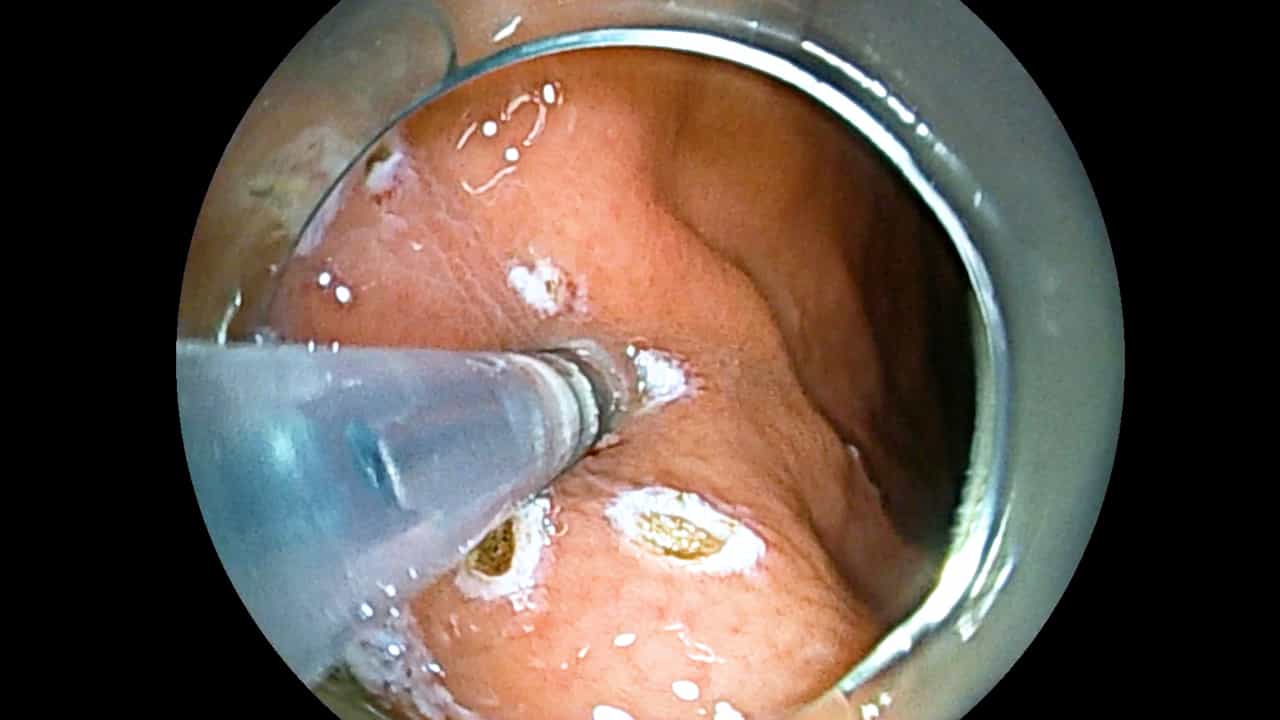
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Study on endoscopic management of foreign bodies in the upper gastrointestinal tract and practice recommendations for
Easwaramoorthy Sundaram1, Sonal Kapoor2, Emaya Anand3
1Department of General Surgery, Lotus Hospital and Research Center, Erode, Tamil Nadu, India.

Introduction:
Foreign bodies (FBs) in the upper gastrointestinal (GI) tract often present as a surgical emergency. Swift diagnosis and an expert endoscopic management are paramount for a good outcome. In this study, we reviewed the endoscopic management of 60 cases of FB in the upper GI tract and outlined the recommendations for such an emergency in a rural setting.
Patients And Methods:
This was a retrospective study on 60 consecutive patients with FB ingestion who underwent endoscopic removal of FB over 12 months. The present study aimed to assess the effectiveness of various endoscopic tools and techniques for retrieving different foreign objects, along with their associated success rates.
Results:
Amongst the 60 patients, 38 were male and the remaining 22 were female. The mean age of the patients was 36.4 years. Most cases presented with ingestion of blunt objects (36.7%), followed by food bolus (30%), sharps (18.3%) and finally long objects (15%). Most FBs were seen lodged in the lower oesophagus. Rat-toothed forceps and Roth Net ® were the common endoscopic tools used for FB retrieval.
Discussion:
The FB oesophagus needs immediate attention and removal within 24 h to avoid the risk of perforation and aspiration. Button battery, denture with sharp wire and impacted fish or chicken bones are problem cases and need immediate attention by experts. If the FB is already in the stomach and beyond, one may choose to observe for spontaneous expulsion in the next 2-5 days. In adults, removal can be accomplished under xylocaine spray or conscious sedation, but in children, it invariably requires the presence of an anaesthetist and general anaesthesia, as airway control is vital.
Conclusion:
Endoscopic removal of FB from the upper GI tract is safe and effective, provided the right tools, team and technical expertise are available. An endoscopic skillset is essential for future surgeons.
Related Concept Videos
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:25
Endoscopic Procedures II: Colonoscopy
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease