Related Experiment Video
Updated: Aug 23, 2026
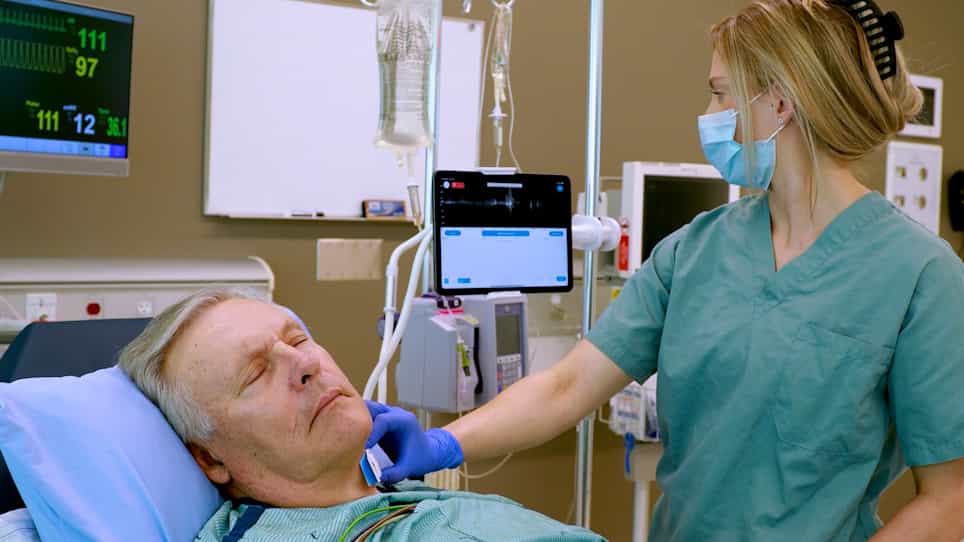

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Development and Independent Validation of a Machine Learning-Based Noninvasive Venous Waveform Analysis for Heart
Bret D Alvis1, Jeffrey Schmeckpeper2, Aniket S Rali2
1Department of Anesthesiology, Vanderbilt University Medical Center, Nashville, Tennessee; College of Biomedical Engineering, Vanderbilt University, Nashville, Tennessee; VoluMetrix, LLC, Nashville, Tennessee.

Background:
Hemodynamic-guided management improves outcomes in heart failure (HF), but implantable pulmonary artery pressure monitoring is limited by cost and invasiveness. Noninvasive venous waveform analysis for heart failure (NIVAHF) is a machine learning-based device that estimates the pulmonary capillary wedge pressure (PCWP) from peripheral venous waveforms.
Objectives:
To describe the development and multicenter validation of the NIVAHF Device by evaluating agreement between the NIVA Score and invasively measured PCWP.
Methods:
In this prospective, multicenter study, peripheral venous waveforms were acquired noninvasively with the NIVAHF Device and analyzed by a supervised neural network using a 60:20:20 training, validation, and independent test allocation, with one site held out as the dominant contributor to the locked test cohort. Agreement between the NIVA Score and the invasively measured PCWP was assessed by Bland-Altman analysis in the locked, independent, right heart catheterization test cohort. Discrimination for elevated filling pressure (PCWP >15 mm Hg) was evaluated by receiver operating characteristic analysis, with PCWP-left ventricular end-diastolic pressure (LVEDP) and pulmonary artery diastolic pressure-LVEDP agreement analyzed for context.
Results:
In the independent right heart catheterization test cohort (n = 122), the NIVA Score showed a mean bias of -1.06 ± 5.57 mm Hg and 95% limits of agreement of -11.98 to 9.87 mm Hg vs the PCWP, falling between the invasive surrogate comparisons (PCWP-LVEDP, -9.31 to 7.54; pulmonary artery diastolic pressure-LVEDP, -14.85 to 8.63). The area under the curve for a PCWP of >15 mm Hg was 0.71 (95% CI 0.61-0.80; P < 0.0001; 89% sensitivity, 36% specificity).
Conclusions:
The NIVA Score demonstrated agreement with the PCWP, comparable with accepted invasive surrogates and detected elevated filling pressures with high sensitivity, supporting the NIVAHF as a noninvasive congestion marker in HF.