Related Experiment Video
Updated: Aug 23, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
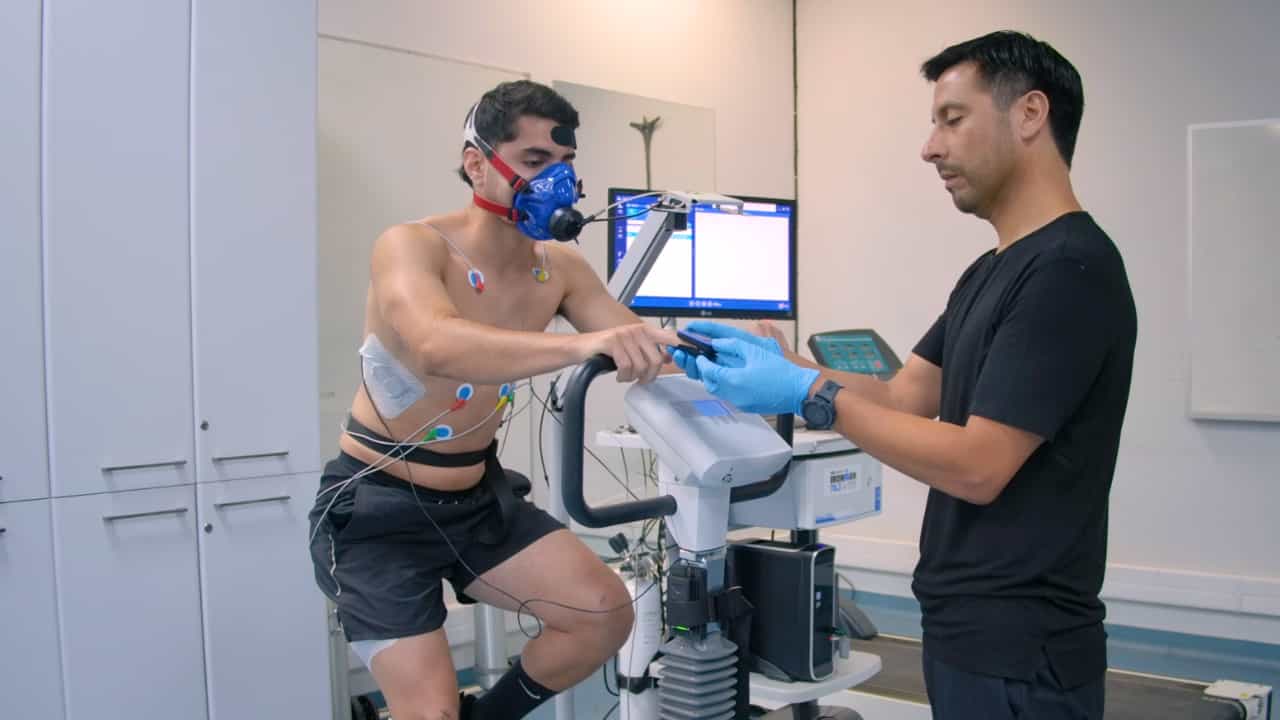
Clinical utilization of CPET in obesity-associated unexplained exertional dyspnea: Narrative review and expert
Fa-Chang Yu1, Cho-Kai Wu2, Shih-Hsien Sung3
1Division of Cardiovascular Intervention, Department of Cardiovascular Medicine, Department of Internal Medicine, MacKay Memorial Hospital, Taipei, Taiwan; School of Medicine and Graduate Institute of Biomedical Sciences, College of Medicine, MacKay Medical University, New Taipei City, Taiwan.

Abstract:
Obesity-associated exertional dyspnea is a major diagnostic blind spot in contemporary heart failure care. In many patients, symptoms reflect overlapping contributions from mechanical ventilatory constraint, low cardiorespiratory fitness, regional cardiac adiposity, peripheral skeletal muscle dysfunction, and occult heart failure with preserved ejection fraction (HFpEF). Diagnosis is frequently delayed because obesity lowers natriuretic peptide concentrations, reduces the sensitivity of resting echocardiography, and overlaps with noncardiac causes of exercise intolerance. Current evidence supports obesity-related HFpEF as a distinct phenotype shaped by visceral and epicardial adiposity, maladaptive adipokine signaling, inflammation, plasma volume expansion, and abnormal exercise hemodynamics. In this context, cardiopulmonary exercise testing (CPET) is best viewed as a mechanistic phenotyping tool that helps refine suspicion, characterize the dominant physiological limitation, and guide further testing when resting evaluation is inconclusive. Emerging anti-obesity therapies have strengthened the clinical importance of recognizing obesity-related HFpEF, but whether treatment-induced benefit is accompanied by improvement in CPET-defined physiology remains uncertain.
Related Concept Videos
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations