
Traumatic complete pyloric transection following blunt abdominal trauma: A case report and literature review
Khac Thao Thai1, Trong Hoe Nguyen1, Thanh Son Le2
1Department of Gastrointestinal Surgery, Military Hospital 103, Hanoi, Vietnam.

Rationale:
Gastric rupture after blunt abdominal trauma is rare, and complex disruptions such as complete pyloric transection are exceptionally uncommon, having been described only in isolated case reports. Early diagnosis and timely surgical intervention are crucial to prevent septic complications resulting from peritoneal contamination.
Patient Concerns:
A 31-year-old male presented with severe abdominal pain after a motorcycle collision following a heavy meal and alcohol intake.
Diagnoses:
The patient presented with agitation and impaired communication due to alcohol intoxication. Vital signs included a respiratory rate of 28 breaths/min, a pulse of 112 bpm, blood pressure of 110/60 mm Hg, and he was afebrile. Abdominal examination revealed epigastric bruising, mild distension, diffuse tenderness with epigastric predominance, abdominal guarding, and rebound tenderness suggestive of peritonitis. Whole-body contrast-enhanced computed tomography demonstrated pneumoperitoneum, extraluminal food spillage, and a clear discontinuity of the gastric wall, consistent with traumatic gastric rupture.
Interventions:
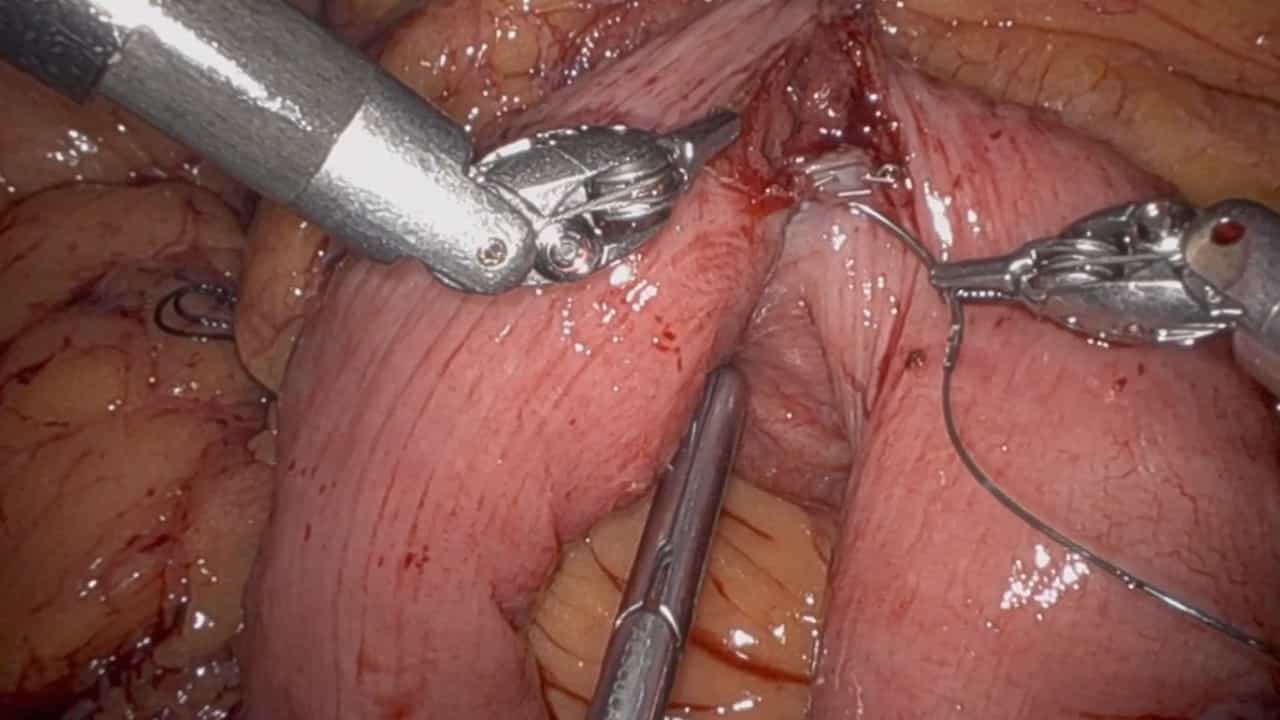
Emergency laparoscopy converted to laparotomy revealed complete pyloric transection, anterior antral rupture, and colonic seromuscular tears. The patient underwent two-thirds distal gastrectomy with Roux-en-Y reconstruction, extensive peritoneal lavage, and abdominal drainage.
Outcomes:
The postoperative course was favorable. Oral intake resumed on postoperative day 5, and the patient was discharged in stable condition on day 20. At the 30-day follow-up, he had normal eating and bowel habits, gained 3 kg, and endoscopy demonstrated a healed and patent anastomosis.
Lessons:
Whole-body contrast-enhanced computed tomography is highly valuable in the early evaluation of blunt polytrauma and may replace routine radiographs in centers with rapid pan-scan capability. However, when computed tomography is negative or inconclusive, operative decisions should still rely on clinical deterioration such as progressive abdominal distension and guarding. Complex gastric injuries, including complete pyloric transection, require prompt resection and restoration of gastrointestinal continuity to achieve favorable outcomes.
Insights
Severe blunt abdominal trauma can cause rare gastric rupture, including complete pyloric transection. Prompt diagnosis via computed tomography and surgical repair are crucial for favorable outcomes in complex gastric injuries.
Area of Science:
- Trauma Surgery
- Surgical Gastroenterology
- Emergency Medicine
Background:
- Gastric rupture from blunt abdominal trauma is rare.
- Complete pyloric transection is an exceptionally uncommon gastric injury.
- Early diagnosis and surgical intervention are vital to prevent septic complications.
Purpose of the Study:
- To report a rare case of complete pyloric transection following blunt abdominal trauma.
- To highlight the diagnostic value of whole-body contrast-enhanced computed tomography (CT) in polytrauma.
- To emphasize the importance of timely surgical management for complex gastric injuries.
Main Methods:
- A 31-year-old male with severe abdominal pain after a motorcycle collision was evaluated.
- Whole-body contrast-enhanced computed tomography revealed pneumoperitoneum and gastric rupture.
- Emergency laparoscopy converted to laparotomy identified complete pyloric transection and other injuries.
- The patient underwent distal gastrectomy with Roux-en-Y reconstruction and peritoneal lavage.
Main Results:
- The patient's postoperative course was favorable with resumption of oral intake on day 5.
- Discharge occurred on postoperative day 20 in stable condition.
- At 30-day follow-up, the patient had normal eating and bowel habits with a healed anastomosis.
Conclusions:
- Whole-body contrast-enhanced CT is valuable for early evaluation of blunt polytrauma.
- Clinical deterioration should guide operative decisions when CT is inconclusive.
- Prompt resection and reconstruction are essential for favorable outcomes in complex gastric injuries like complete pyloric transection.
Related Concept Videos
 01:11
Pyloric Obstruction
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:07
Intestinal Obstruction II: Pathophysiology
 01:27
Peptic Ulcer