Related Experiment Videos
Impact of pressure -regulated volume control vs volume -controlled ventilation on respiratory mechanics in pediatric
Jing Shi1, Wenjuan Bao1, Wenjing Chen1
1Department of Anesthesiology, Hebei Clinical Research Center for Children's Health and Diseases, Hebei Children's Hospital, Shijiazhuang Hebei, China.

Insights
Pressure-regulated volume control (PRVC) ventilation lowered peak and mean airway pressures in young children during laparoscopic surgery compared to volume-controlled ventilation (VCV). However, plateau and driving pressures were similar, indicating comparable alveolar distention between the two ventilation modes.
Area of Science:
- Pediatric Anesthesiology
- Respiratory Mechanics
- Mechanical Ventilation
Background:
- Pneumoperitoneum during pediatric laparoscopic surgery can negatively impact respiratory mechanics and increase the risk of ventilator-induced lung injury.
- Optimal mechanical ventilation strategies in this setting remain a subject of debate.
Purpose of the Study:
- To compare the efficacy of pressure-regulated volume control (PRVC) versus volume-controlled ventilation (VCV) in young children undergoing laparoscopic surgery.
- To assess the impact of these ventilation modes on airway pressures and gas exchange.
Main Methods:
- A randomized controlled trial involving 120 children aged 1-3 years undergoing prolonged laparoscopic surgery (≥120 min).
- Patients were assigned to either PRVC or VCV group.
- Primary outcome was peak inspiratory pressure (Ppeak) at 30 minutes post-pneumoperitoneum; secondary outcomes included other airway pressures, gas exchange, hemodynamics, and complication rates.
Main Results:
- PRVC resulted in significantly lower Ppeak and mean airway pressure (Pmean) compared to VCV at 30 minutes post-pneumoperitoneum.
- No significant differences were observed in plateau pressure (Pplat) or driving pressure (ΔP) between the groups.
- The arterial-to-end-tidal CO2 gradient was wider with PRVC, though hemodynamic variables and complication rates were similar between modes.
Conclusions:
- PRVC ventilation reduces peak and mean airway pressures in pediatric laparoscopic surgery but does not alter plateau or driving pressures, suggesting similar alveolar distention compared to VCV.
- Both ventilation modes provide adequate gas exchange and hemodynamic stability.
- While PRVC may offer benefits in airway pressure management, its routine adoption over VCV should not solely depend on Ppeak reduction.
Introduction:
Optimal ventilation during pediatric laparoscopic surgery is a debated issue, as pneumoperitoneum impairs respiratory mechanics and may increase ventilator-induced lung injury.
Aim:
We aimed to compare pressure-regulated volume control (PRVC) and volume-controlled ventilation (VCV) in young children, focusing on airway pressures and gas exchange.
Materials And Methods:
A total of 120 children aged 1-3 years undergoing elective laparoscopic surgery (≥120 min) were enrolled and assigned to the PRVC or VCV groups. The primary outcome was peak inspiratory pressure (Ppeak) at 30 minutes after pneumoperitoneum. Secondary outcomes included mean airway (Pmean), plateau (Pplat), and driving pressures (ΔP), partial pressure of end-tidal carbon dioxide (PETCO2), arterial carbon dioxide partial pressure (PaCO2), hemodynamics, PaCO2-PETCO2 Bland-Altman agreement, and complication rates.
Results:
At 30 minutes, PRVC produced lower mean (SD) Ppeak than VCV (22.67 [4.18] vs 26.24 [4.51] cm H2O; P <0.001) and lower mean Pmean at multiple time points. However, Pplat and ΔP did not differ between the groups. The arterial-to-end-tidal CO2 gradient was wider with PRVC at 30 minutes and after desufflation. Hemodynamic variables remained stable and similar between the groups. The Bland-Altman analysis showed acceptable agreement between PaCO2 and PETCO2 in both modes, with mean (SD) bias of 3.21 (0.48) in the PRVC and 1.91 (0.82) in the VCV cohorts. The complication rates were similar in both groups.
Conclusions:
In young children undergoing prolonged laparoscopic surgery, PRVC lowered Ppeak and Pmean but did not reduce Pplat or ΔP, suggesting similar alveolar distention to that occurring in VCV. Both modes maintained adequate ventilation and stable hemodynamics. PRVC may improve airway pressure profiles, but its routine replacement with VCV should not rely on Ppeak reduction alone.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:15
Respiratory Volumes
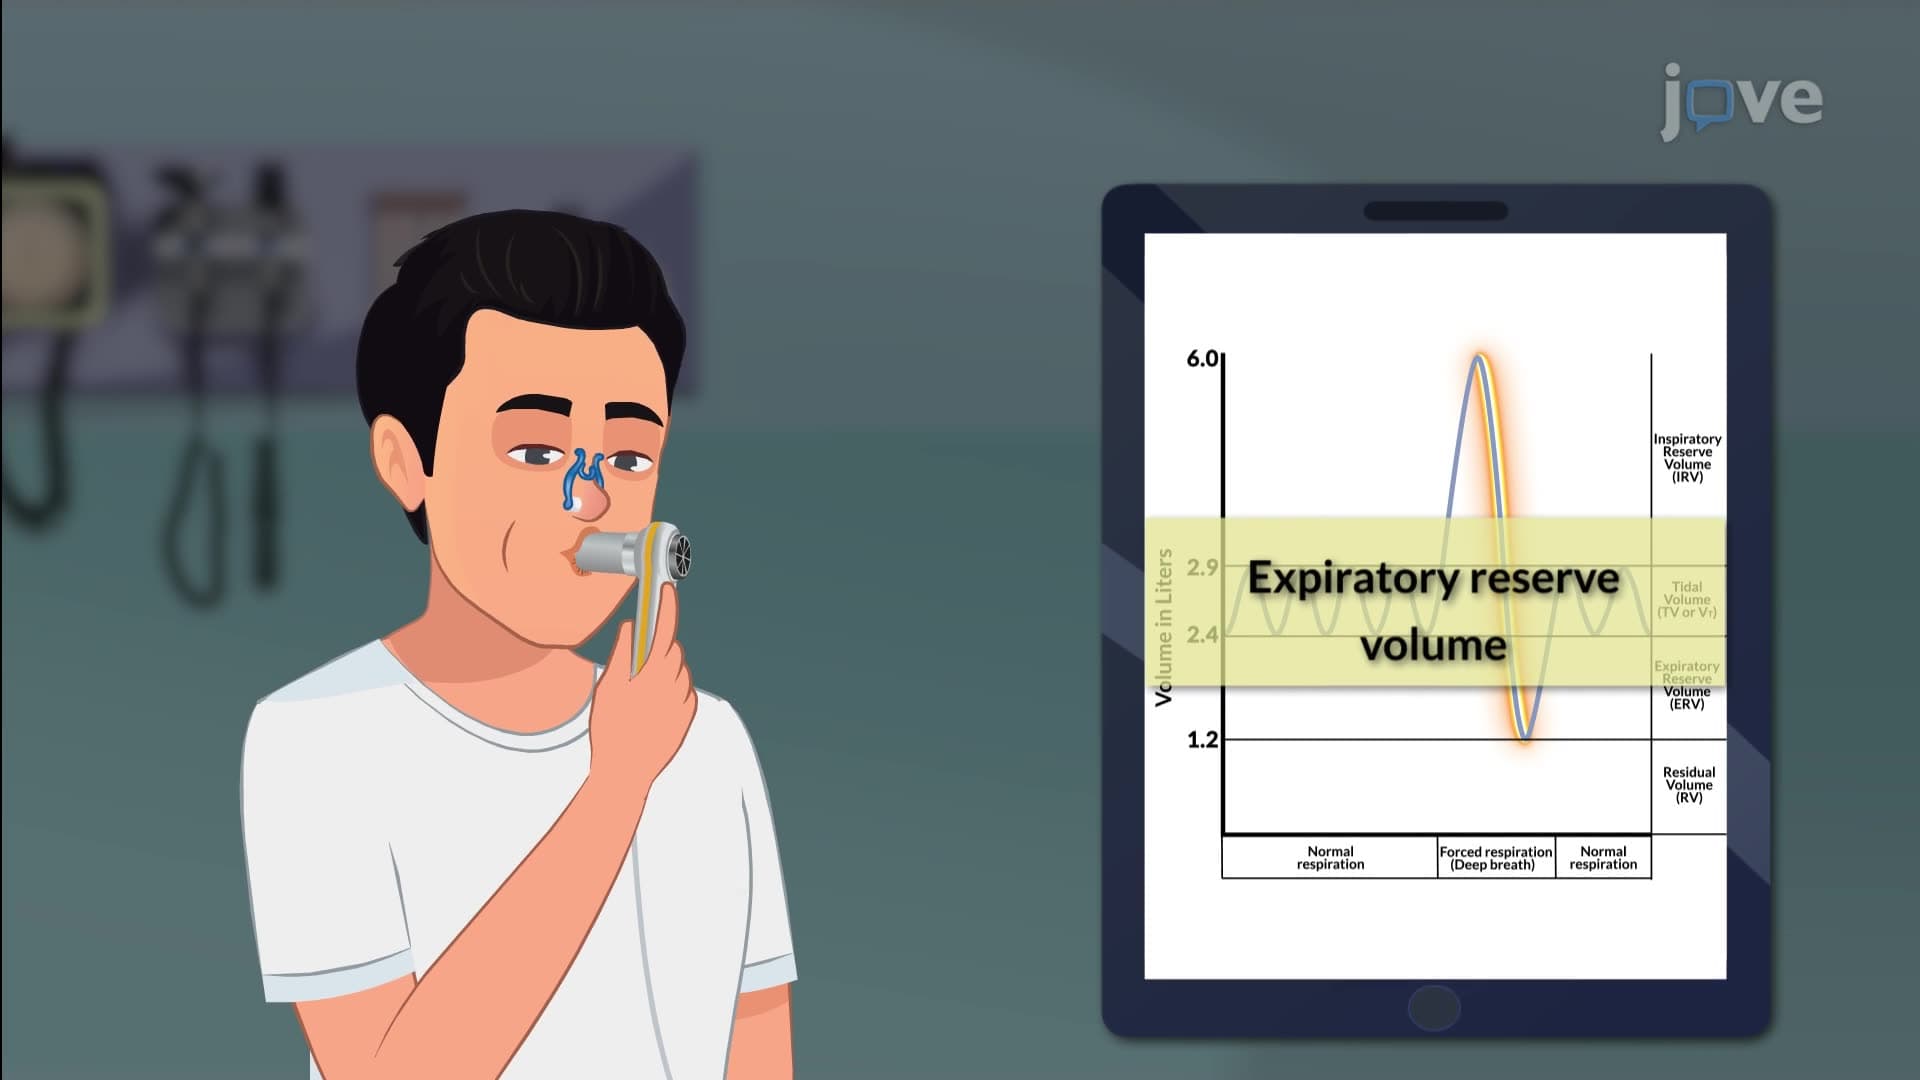
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: