Related Experiment Video
Updated: Aug 25, 2026
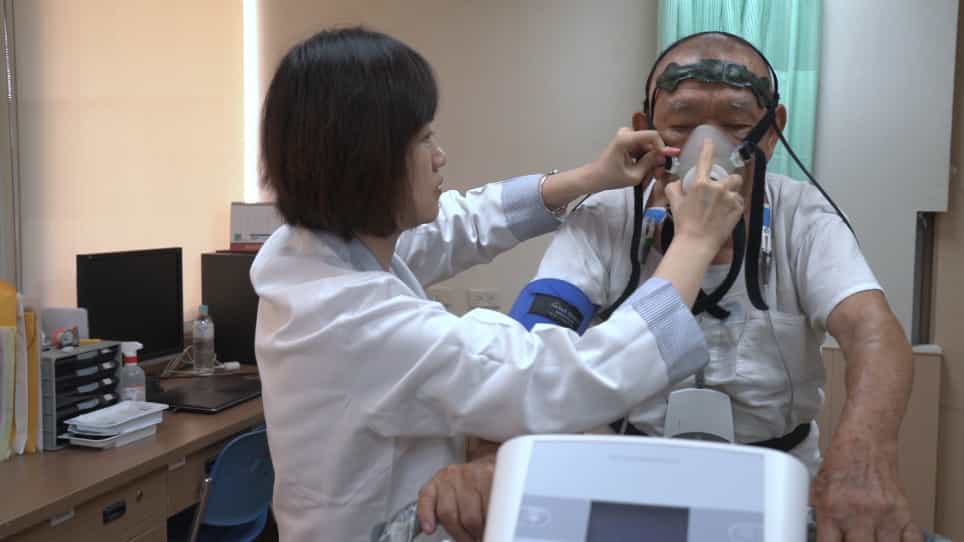

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Impact of systemic inflammation on exercise haemodynamics in unexplained dyspnoea and heart failure with preserved
Giulio M Mondellini1,2, Jannik Heemann1,3, Xavier Galloo1
1Centre for Cardiovascular Diseases, University Hospital Brussels, Jette, Belgium.

Aim:
Systemic inflammation in heart failure with preserved ejection fraction (HFpEF) predicts worse outcomes. This study investigates its impact on exercise haemodynamics in patients with unexplained dyspnoea.
Methods:
This prospective cohort study includes subjects referred for unexplained dyspnoea to a multidisciplinary dyspnoea clinic between January 2021 and August 2023 for cardiopulmonary exercise testing with concomitant exercise echocardiography. Systemic inflammation was defined as a high-sensitivity C-reactive protein level ≥2 mg/L. HFpEF was diagnosed with an H2FPEF score ≥6, HFA-PEFF score ≥5, or in case of exercise pulmonary hypertension together with a left atrial reservoir strain <24.5% at rest or positive diastolic stress test during exercise.
Results:
A total of 70/191 consecutively evaluated subjects (37%) had systemic inflammation, which was linked with anthropometrics of increased adiposity. Subjects with vs. without systemic inflammation had smaller end-diastolic volume indices (40.9 ± 9.7 vs. 47.2 ± 13.3 mL/m2, respectively; p = .002), a lower tricuspid annular plane systolic excursion over pulmonary artery systolic pressure ratio [0.96 (0.75-1.10) vs. 1.04 (0.85-1.28) mm/mmHg, respectively; p = .033], but otherwise similar echocardiography findings at rest. For a similar respiratory exchange ratio at peak exercise, they had lower peak oxygen consumption (16.9 ± 5.3 vs. 20.6 ± 6.6 mL/min/kg, respectively; p < .001). The right ventricular end-systolic pressure area ratio change with exercise indicated less right ventricular contractile reserve when systemic inflammation was present. In the HFpEF subgroup, patients with vs. without systemic inflammation had a decreased cardiac output reserve with exercise.
Conclusion:
In subjects with dyspnoea, systemic inflammation is linked to increased adiposity and lower exercise capacity because of impaired right ventricular reserve.
Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:21
Myocarditis I: Introduction
 01:27
Heart Failure I: Introduction