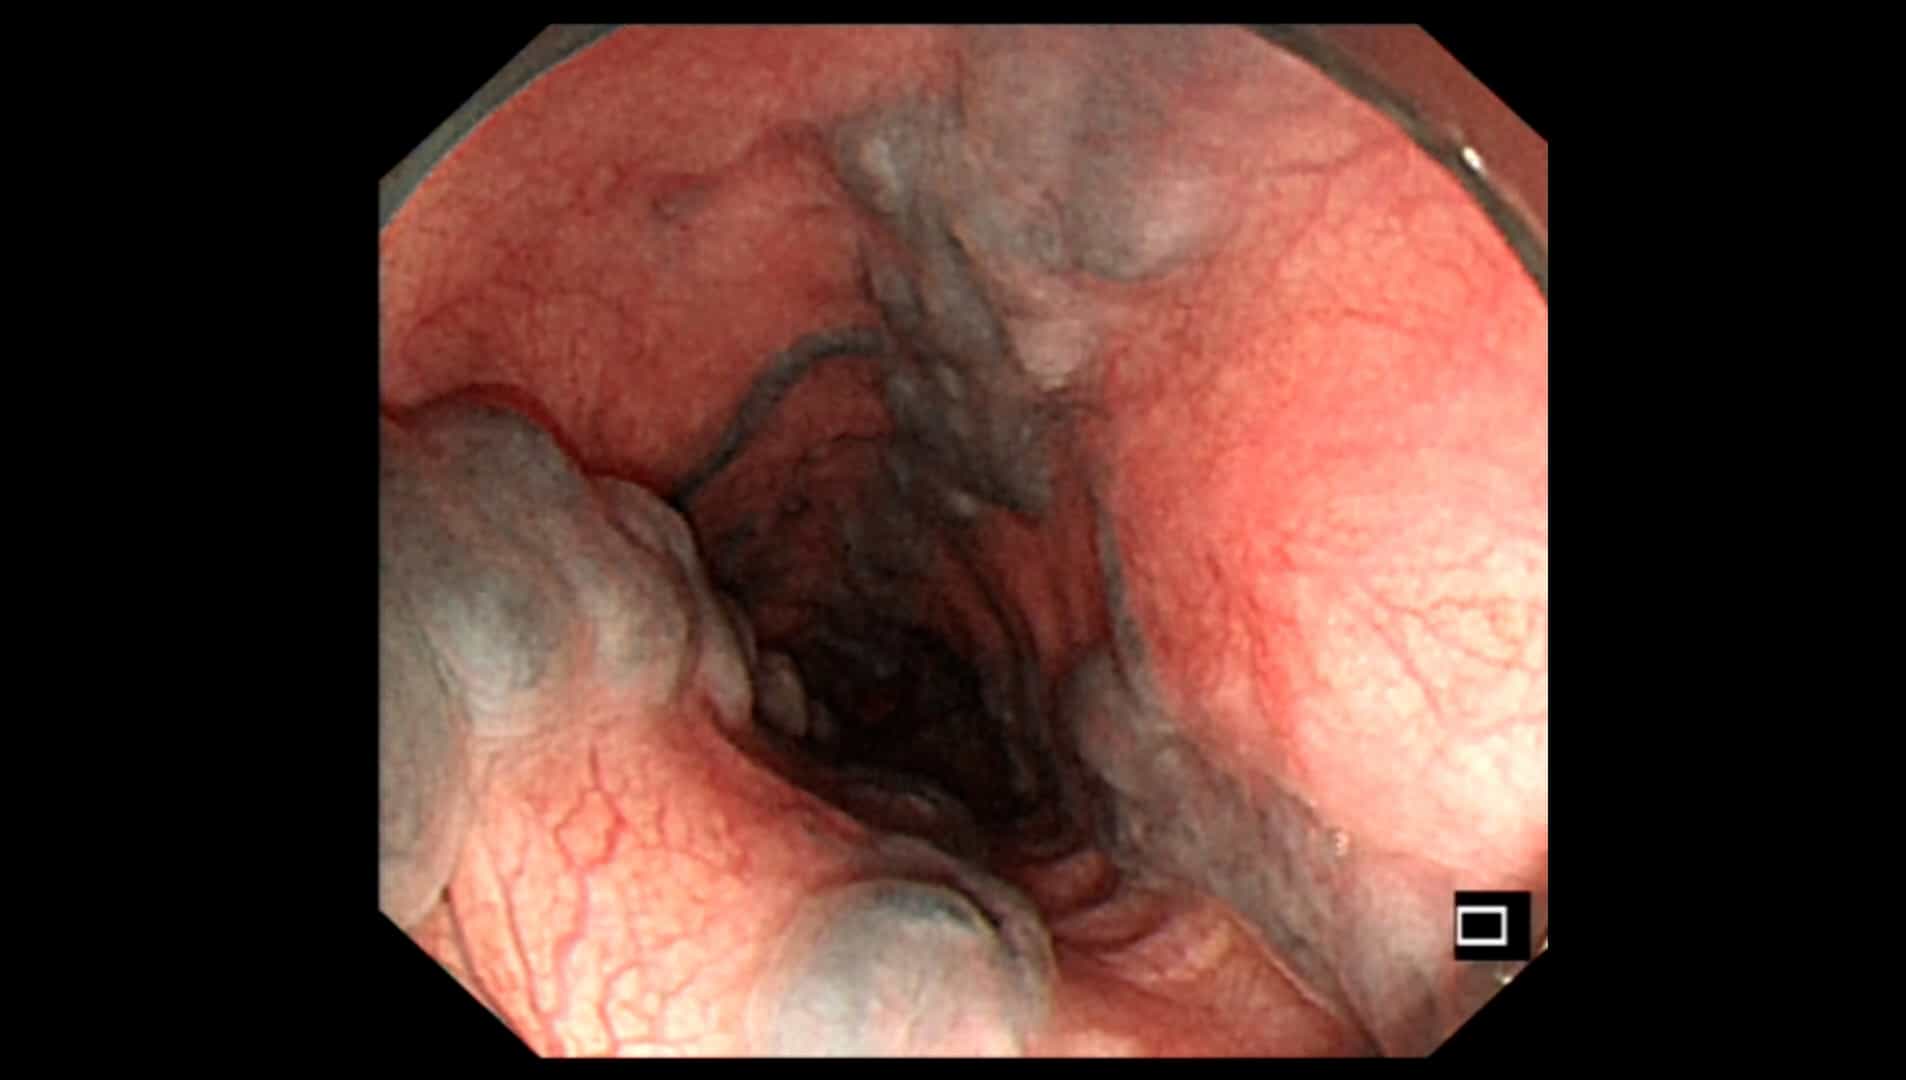
Related Experiment Video
Updated: Aug 26, 2026


Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Laser cryo-sclerotherapy versus conventional sclerotherapy for reticular veins and telangiectasias: A randomized
Marcos Fonseca1, Lara Poltronieri2, Rodrigo Argenta2
1Postgraduate Program in Surgery, Ribeirão Preto Medical School, University of São Paulo (USP), Ribeirão Preto, São Paulo, Brazil; Prime Vascular Clinic, Division of Vascular Surgery and Phlebology, Porto Alegre, Rio Grande do Sul, Brazil.

Objective:
To evaluate whether the hybrid laser cryo-sclerotherapy (LCS; Nd:Y-AG 1064 nm + 75% hypertonic glucose [HG]) protocol produces superior aesthetic outcomes compared with combined conventional sclerotherapy (CS: 67.5% glucose + 0.3% polidocanol [POL]) for the treatment of lower limb reticular veins and telangiectasias (CEAP C1).
Methods:
For this single-center, prospective randomized controlled trial, 60 patients were assessed for eligibility; 4 did not provide informed consent and were not randomized. A total of 56 female patients with CEAP C1 disease and Fitzpatrick phototypes I-III were randomized, with only one lower limb treated per participant: 32 to the LCS group (Nd:YAG 1064 nm + HG75%) and 24 to the CS group (HG67.5% + POL0.3%). Two participants who underwent LCS were subsequently lost to follow-up between Day 1 and Day 30; 54 participants (30 and 24 from the LCS and CS groups, respectively) completed the 90-day follow-up and were analyzed per protocol. Standardized photographs were obtained on Day 1, Day 30, and Day 90, with and without augmented reality (AR; VeinViewer Flex), and were assessed by two blinded external vascular physicians using the Global Aesthetic Improvement Scale (GAIS). Complications, residual pigmentation, and quality of life (Aberdeen Varicose Vein Questionnaire) were evaluated as secondary end points.
Results:
Both groups had equivalent baseline characteristics. The LCS group was superior to the CS group in all GAIS outcomes: D1→D90 without AR (P = .026; r = 0.34; 95% confidence interval [CI], 0.04-0.58; moderate effect); D1→D90 with AR (P < .001; r = 0.53; 95% CI, 0.28-0.72; large effect); D30→D90 without AR (P < .001; r = 0.56; 95% CI, 0.31-0.74; large effect); D30→D90 with AR (P < .001; r = 0.52; 95% CI, 0.26-0.71; large effect). After Bonferroni correction for these four primary comparisons (α = .0125), the D1→D90 comparison without AR no longer reached significance, whereas the remaining three comparisons did. Temporal analysis revealed a progressive late aesthetic response in the LCS group; 80.0% of participants continued improving between Day 30 and Day 90 vs 29.1% in the CS group (70.8% with No Change). The ecchymosis duration was significantly shorter in the LCS group (median, 5.0 vs 10.0 days; P = .012). Severe pigmentation on Day 90 was observed exclusively in the CS group (8.3% vs 0%; P = .019; r = 0.22; small effect; power = 36.4%; this finding is exploratory, see the Discussion section). No cases of deep vein thrombosis or ulcer occurred. Aberdeen Varicose Vein Questionnaire score improvement was significant in both groups (P < .001), with no intergroup difference. Inter-rater agreement was substantial to near-perfect for GAIS assessments (κ = 0.735-0.913) and perfect for complication grading (κ = 1.000).
Conclusions:
The LCS protocol was superior to CS in all GAIS outcomes, with moderate-to-large effect sizes and consistent inter-rater agreement. The aesthetic response was progressive, consolidating between Day 30 and Day 90, with the largest effect size in the late period. AR amplified the magnitude of the detected effects and improved inter-rater agreement, reinforcing its role as a standardizing tool in aesthetic phlebology randomized controlled trials. These statistical findings should be weighed against the higher costs and complexity of LCS relative to CS in a purely cosmetic CEAP C1 population (see the Discussion section).