Related Experiment Video
Updated: Aug 27, 2026
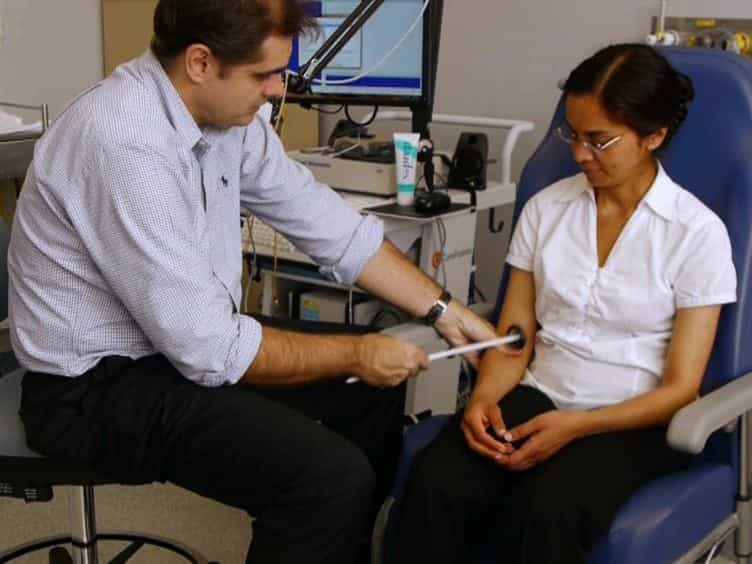

Utility of Dissociated Intrinsic Hand Muscle Atrophy in the Diagnosis of Amyotrophic Lateral Sclerosis
Published on: March 4, 2014
Nociceptive pain in late-onset Pompe disease: prevalence, distribution, and clinical correlates
Stephan Wenninger1, Marcela Arndt2, Daniel H Mendelsohn2
1Friedrich Baur Institute at the Department of Neurology, LMU University Hospital, LMU Medizin, Ludwig-Maximilians-Universität München, Ziemssenstr. 1, 80336, Munich, Germany. stephan.wenninger@med.uni-muenchen.de.

Background:
Nociceptive pain is often recognized as a relevant symptom in late-onset Pompe disease (LOPD), yet its prevalence, distribution, and underlying determinants remain insufficiently characterized. We aimed to systematically assess nociceptive pain in LOPD and to explore its relationship with muscle function, structural muscle alterations, and potential modifiers.
Methods:
In this multicenter cross-sectional study, 42 patients with LOPD and 61 disease controls (IBM, FSHD, SMA3) were evaluated. Pain was assessed using validated questionnaires and pain drawings. Motor function tests, pressure pain thresholds, muscle ultrasound, laboratory parameters, and genetic polymorphisms (ACE, ACTN3) were obtained. Associations between pain and clinical, structural, and biological variables were analyzed.
Results:
Chronic nociceptive musculoskeletal pain was highly prevalent, particularly in LOPD (83.3%) compared to disease controls (p=0.005). However, pain reported on the assessment day was significantly lower in LOPD (30.9%, p<0.001) and SMA3 (25%, p=0.016). No significant associations were found between pain and muscle strength, motor function tests, ultrasound-detected muscle alterations, ACTN3 and ACE, and laboratory parameters.
Conclusion:
Musculoskeletal pain is highly prevalent in LOPD but remains dissociated from objective measures of motor impairment, structural changes of muscle tissue, or genetic modifiers. The significant discrepancy between chronic pain history and acute pain reporting particularly in LOPD and SMA3 suggests that pain represents an independent clinical domain that is not fully captured by single-point assessments. Clinical management should focus on individualized pain assessment, as standard functional tests and snapshot pain assessments do not adequately reflect the patient's pain burden.

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:24
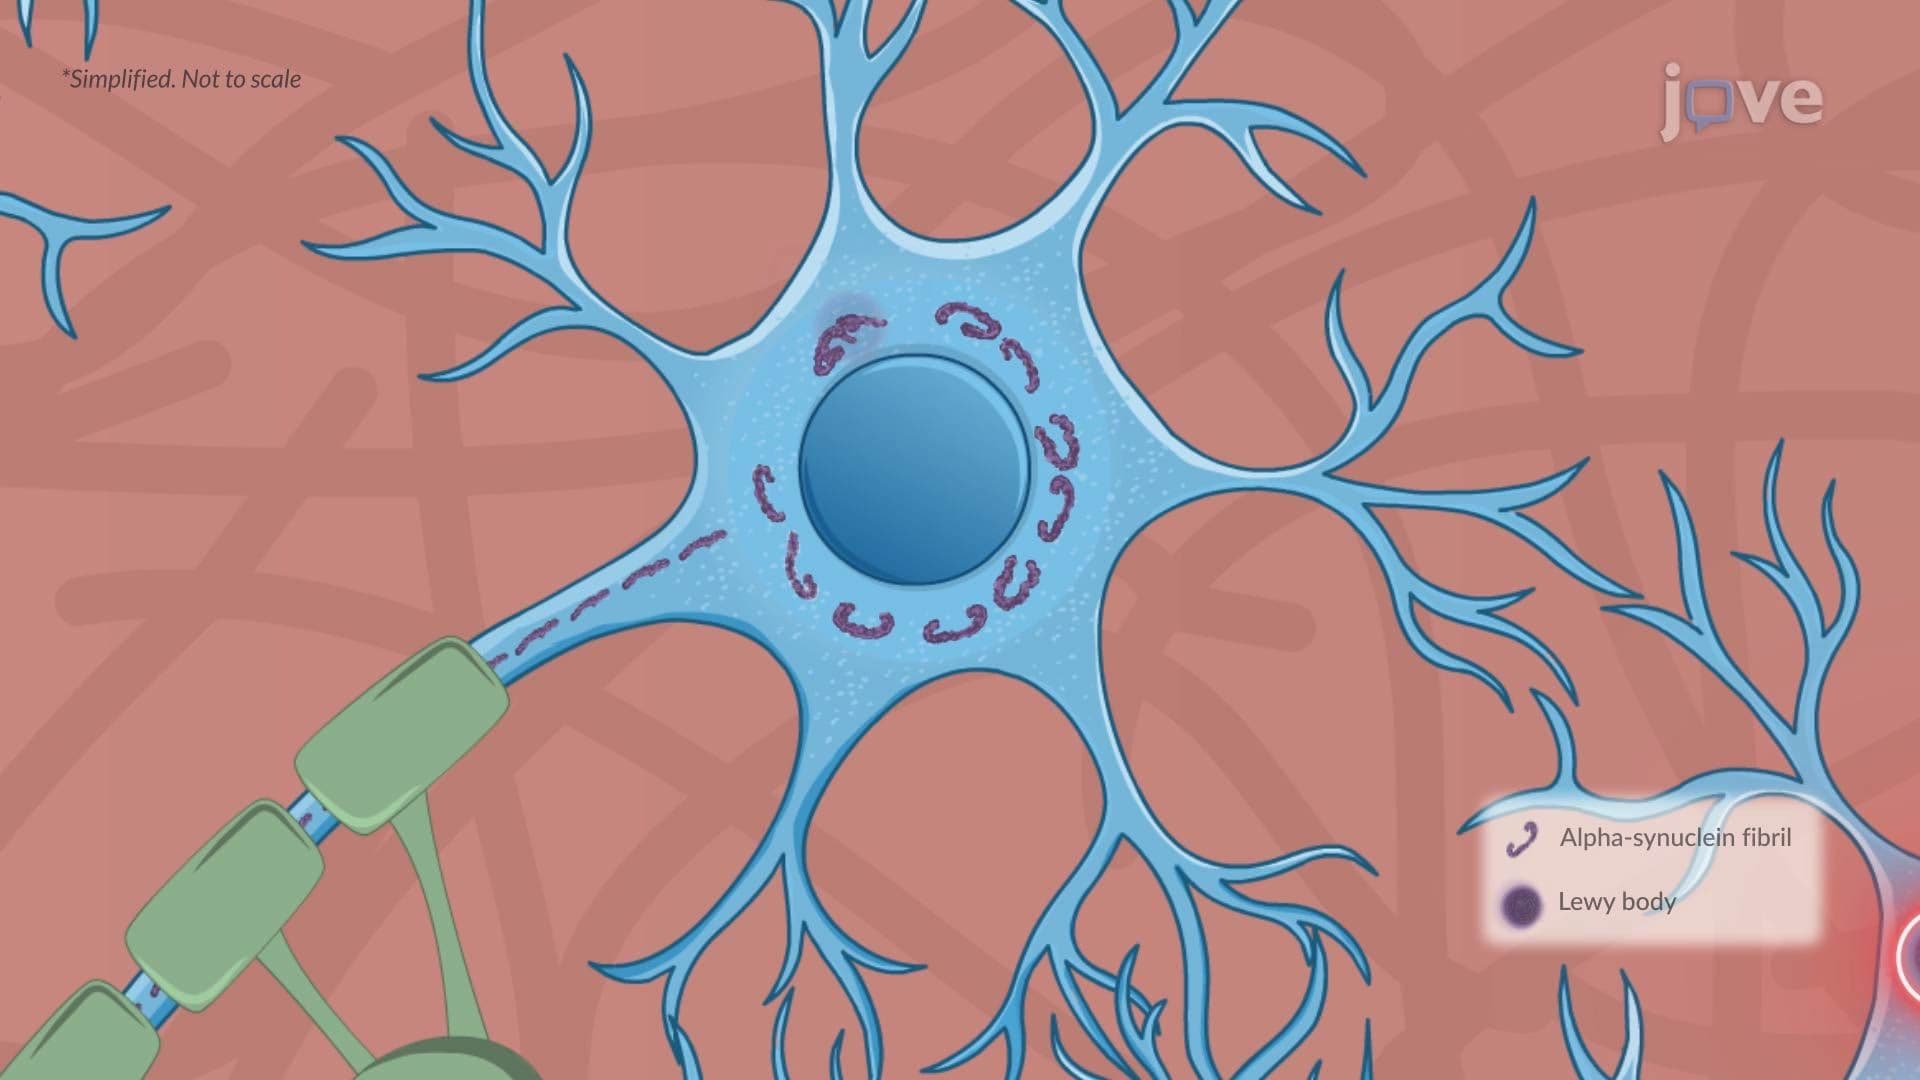
Parkinson Disease ll: Pathophysiology
 01:30
Peripheral Artery Disease I: Introduction
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:15
Parkinson's Disease: Overview