Related Experiment Video
Updated: Aug 28, 2026
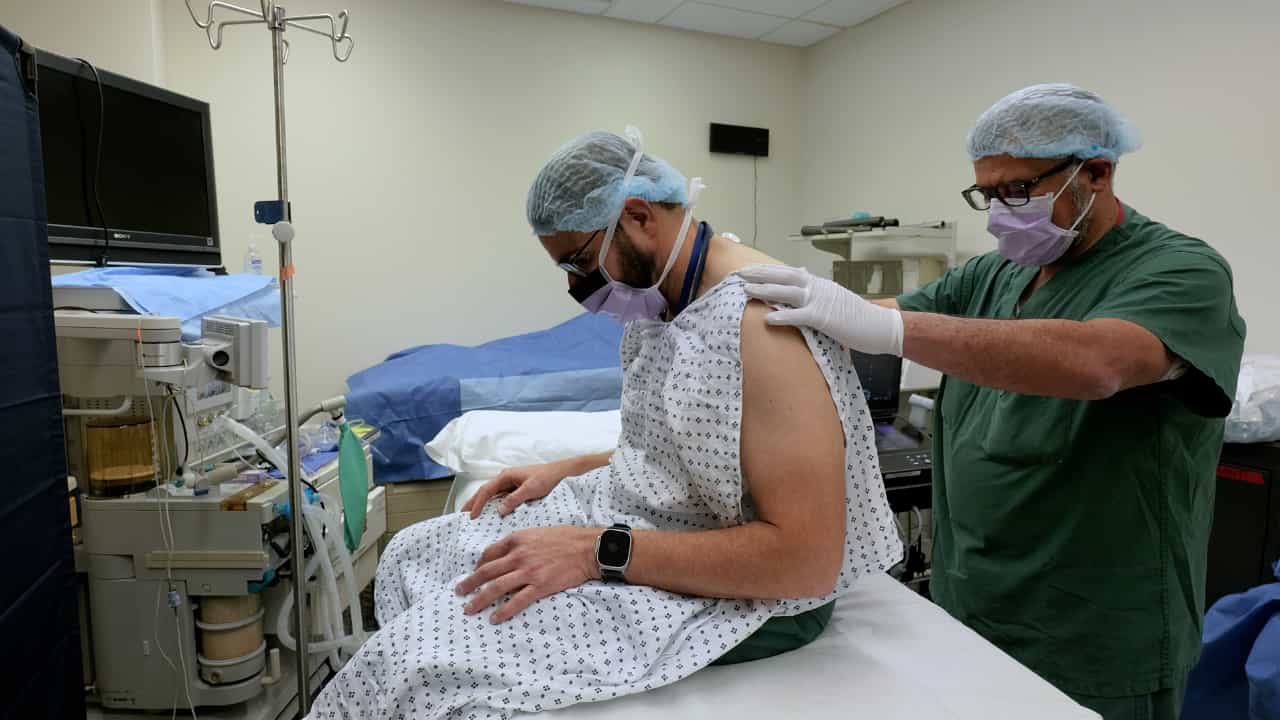

Spinal Sonography for Ultrasound-Guided Lumbar Neuraxial Anesthesia
Published on: January 31, 2025
Dural Puncture Epidural, Standard Epidural, and No Epidural: Comparative Effects on Labor Progression and Neonatal
Kubra C Yilmaz1, Humeyra E Ates Eminoglu1, Mariah Arif2
1Department of Obstetrics and Gynecology, Gazi Yaşargil Training and Research Hospital, 21500 Diyarbakır, Turkey.

Objective: To compare non-epidural labor, standard epidural analgesia, and dural puncture epidural analgesia with respect to labor progression, obstetric outcomes, analgesia-related outcomes, and neonatal results. Methods: This single-center retrospective observational cohort study included 168 term singleton parturients: 58 without epidural analgesia, 56 with standard epidural analgesia, and 54 with dural puncture epidural analgesia. The primary outcome was the duration of the second stage of labor. Secondary outcomes included first-stage duration, mode of delivery, blood loss, transfusion, analgesia quality, maternal side effects, umbilical venous pH, biochemical acidosis, Apgar scores, neonatal intensive care unit admission, and neonatal resuscitation. Analyses included group comparisons, adjusted models, quantile regression, Firth penalized logistic regression, propensity-score inverse probability weighting, and a nulliparous sensitivity analysis. Results: Second-stage duration was comparable across groups (median 40.0, 45.0, and 48.5 min in the no-epidural, standard epidural, and dural puncture epidural groups, respectively; p = 0.118). Active pushing time was likewise comparable (8.0, 8.5, and 12.0 min, respectively; p = 0.292), and quantile regression, together with a nulliparous sensitivity analysis-in which the second stage was longest in the no-epidural group-did not indicate epidural-related labor prolongation. Compared with standard epidural analgesia, dural puncture epidural analgesia showed numerically lower pain scores and a numerically lower rescue bolus requirement (30/54 [55.6%] vs. 39/56 [69.6%]; p = 0.183), although neither difference reached statistical significance. Umbilical cord venous pH and biochemical acidosis (cord venous pH < 7.20) did not differ significantly among groups (p = 0.266 and p = 0.335, respectively). The only neonatal endpoint that differed between groups was a recorded fetal acidosis flag, which was more frequent in the epidural groups (0%, 7.1%, and 16.7%; p = 0.004) but was not corroborated by objective cord pH, Apgar scores, neonatal resuscitation, or a significant increase in neonatal intensive care unit admission (5.2%, 10.7%, and 16.7%; p = 0.145). Conclusions: Contemporary low-dose standard epidural and dural puncture epidural analgesia were not associated with clinically meaningful prolongation of labor, active pushing time, or major obstetric intervention. Dural puncture epidural analgesia showed a non-significant trend toward more favorable analgesic performance compared with standard epidural analgesia. Objective neonatal acid-base measures (cord venous pH and biochemical acidosis) did not differ significantly between groups; only a recorded fetal acidosis flag was more frequent in the epidural groups, without correlation to objective cord pH or to adverse clinical neonatal outcomes. These results support the obstetric and neonatal safety of contemporary low-dose epidural techniques; the isolated recorded acidosis signal warrants confirmation in prospective studies with standardized cord blood gas sampling.
Objective: To compare non-epidural labor, standard epidural analgesia, and dural puncture epidural analgesia with respect to labor progression, obstetric outcomes, analgesia-related outcomes, and neonatal results. Methods: This single-center retrospective observational cohort study included 168 term singleton parturients: 58 without epidural analgesia, 56 with standard epidural analgesia, and 54 with dural puncture epidural analgesia. The primary outcome was the duration of the second stage of labor. Secondary outcomes included first-stage duration, mode of delivery, blood loss, transfusion, analgesia quality, maternal side effects, umbilical venous pH, biochemical acidosis, Apgar scores, neonatal intensive care unit admission, and neonatal resuscitation. Analyses included group comparisons, adjusted models, quantile regression, Firth penalized logistic regression, propensity-score inverse probability weighting, and a nulliparous sensitivity analysis. Results: Second-stage duration was comparable across groups (median 40.0, 45.0, and 48.5 min in the no-epidural, standard epidural, and dural puncture epidural groups, respectively; p = 0.118). Active pushing time was likewise comparable (8.0, 8.5, and 12.0 min, respectively; p = 0.292), and quantile regression, together with a nulliparous sensitivity analysis-in which the second stage was longest in the no-epidural group-did not indicate epidural-related labor prolongation. Compared with standard epidural analgesia, dural puncture epidural analgesia showed numerically lower pain scores and a numerically lower rescue bolus requirement (30/54 [55.6%] vs. 39/56 [69.6%]; p = 0.183), although neither difference reached statistical significance. Umbilical cord venous pH and biochemical acidosis (cord venous pH < 7.20) did not differ significantly among groups (p = 0.266 and p = 0.335, respectively). The only neonatal endpoint that differed between groups was a recorded fetal acidosis flag, which was more frequent in the epidural groups (0%, 7.1%, and 16.7%; p = 0.004) but was not corroborated by objective cord pH, Apgar scores, neonatal resuscitation, or a significant increase in neonatal intensive care unit admission (5.2%, 10.7%, and 16.7%; p = 0.145). Conclusions: Contemporary low-dose standard epidural and dural puncture epidural analgesia were not associated with clinically meaningful prolongation of labor, active pushing time, or major obstetric intervention. Dural puncture epidural analgesia showed a non-significant trend toward more favorable analgesic performance compared with standard epidural analgesia. Objective neonatal acid-base measures (cord venous pH and biochemical acidosis) did not differ significantly between groups; only a recorded fetal acidosis flag was more frequent in the epidural groups, without correlation to objective cord pH or to adverse clinical neonatal outcomes. These results support the obstetric and neonatal safety of contemporary low-dose epidural techniques; the isolated recorded acidosis signal warrants confirmation in prospective studies with standardized cord blood gas sampling.
Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:24
Parenteral Anesthetics: Overview