Related Experiment Video
Updated: Aug 28, 2026
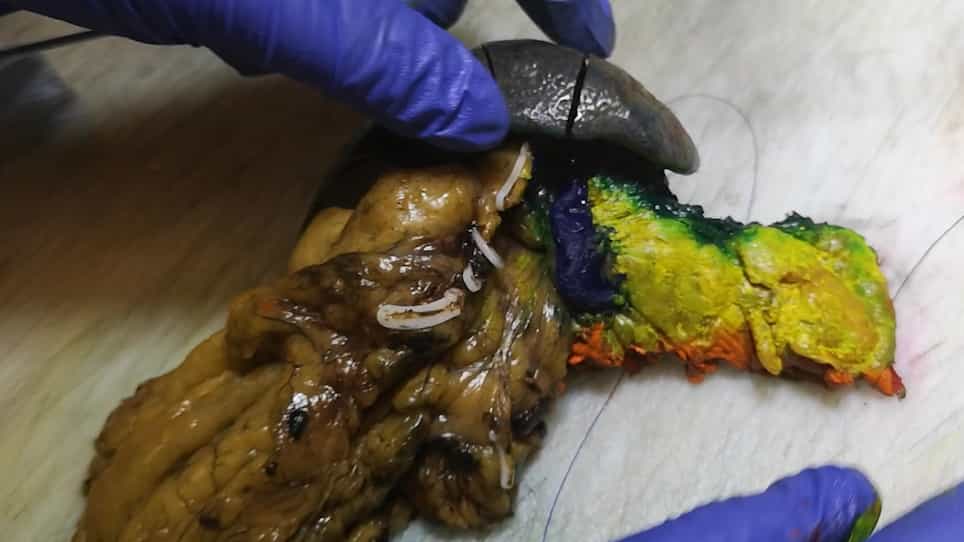

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Prognostic Determinants of Overall Survival After Resection for Pancreatic Ductal Adenocarcinoma: A Consensus-Based
Muhammad Maisam Ali1, Kaleem S Ahmed1, Clayton T Marcinak1
1Division of Surgical Oncology, Department of Surgery, University of Wisconsin School of Medicine and Public Health, Madison, Wisconsin, USA.

Abstract:
Pancreatic ductal adenocarcinoma (PDAC) carries a dismal prognosis despite surgical resection, yet the prognostic literature remains fragmented across hundreds of single-institution studies that vary in design, covariates, and analytical approaches. A synthesis of this evidence is needed to identify which factors most consistently predict overall survival (OS) after curative-intent resection and standardize covariate selection for future outcomes research and trial design. Following PRISMA guidelines, we systematically searched PubMed, Embase, Scopus, and CINAHL (1990-2023) for studies reporting on factors associated with OS following curative-intent resection for PDAC. Prognostic variables from multivariable analyses were extracted and categorized into six conceptual domains: demographics and socioeconomic factors, clinical characteristics, laboratory parameters, molecular biomarkers, tumor characteristics, and treatment-related factors. Strength of agreement across studies was classified as consensus (≥ 75% concordance), fair (> 50%-74%), or weak/none (≤ 50%). The protocol was pre-registered in PROSPERO (CRD42021278699). Of 49 867 identified records, 947 studies encompassing 1 430 411 patients met inclusion criteria. A total of 650 prognostic factors were tested with OS across the literature; 58 were incorporated into the conceptual framework. Among tumor characteristics, pathological nodal status (pN; 82.1%, consensus) and tumor grade (75.0%, consensus) were the strongest and most consistent negative predictors of OS. Margin status, perineural invasion, and lymph node ratio reached fair-level negative agreement. Receipt of adjuvant chemotherapy was the most robust positive predictor (80.4%, consensus), followed by treatment at an academic medical center (75.0%, consensus). Socioeconomic determinants-including private insurance and higher income-demonstrated consensus-level positive associations with OS. Most comorbidities, laboratory parameters, and preoperative clinical characteristics showed fair-to-no association with OS in multivariable analyses. Tumor biology and receipt of adjuvant chemotherapy are the most consistent determinants of OS post-PDAC resection. Socioeconomic and structural factors carry consistent prognostic weight and warrant routine inclusion in survival models. Our findings provide a framework for future prognostic modeling, clinical decision-making, and trial design.
