Related Experiment Videos
De Garengeot hernia with intestinal obstruction and appendiceal abscess in an elderly Peruvian patient: a case report
Alvaro Veleto1, Cesar Sapaico-Del-Castillo1, Roberto Orta-Barriga1
1Faculty of Human Medicine, Universidad Católica de Santa María, Arequipa, Peru.

Background:
De Garengeot hernia is a rare entity defined by the presence of the vermiform appendix within the sac of a femoral hernia, with a reported incidence of 0.5-5% of femoral hernias; concurrent acute appendicitis is exceptional, with a reported incidence of 0.08-0.13%. Its association with secondary mechanical intestinal obstruction is rarely described in the literature, and preoperative diagnosis remains an ongoing clinical challenge. We report this uncommon presentation in an elderly Peruvian woman.
Case Presentation:
An 86-year-old woman presented to the emergency department with a one-day history of colicky abdominal pain accompanied by progressive abdominal distension, nausea, and vomiting of alimentary content. She reported passing flatus per rectum and disclosed a history of drainage of a right inguinal abscess performed one day prior to admission at a private clinic. On examination, she was in a fair general condition with signs of dehydration and moderate subcutaneous tissue. Focused abdominal examination revealed distension with tympanic resonance, metallic bowel sounds, and tenderness over the lower abdomen Laboratory studies revealed a normal leukocyte count (9.95 × 10⁹/L), hyponatremia (Na, 127 mmol/L), hypochloremia (Cl, 88.2 mmol/L), neutrophilia (92%) with a left shift, and a markedly elevated C-reactive protein level (244.7 mg/L). Plain abdominal radiography showed dilated small-bowel loops with multiple air-fluid levels. Contrast-enhanced computed tomography (CT) corroborated signs of intestinal obstruction and additionally identified a femoral mass containing a tubular gas-filled structure within the hernial sac, consistent with De Garengeot hernia complicated by intestinal obstruction.
Diagnostic Assessment And Outcomes:
The patient underwent exploratory laparotomy with appendectomy, peritoneal lavage and drainage, adhesiolysis, and primary closure of the femoral hernia defect. The postoperative diagnosis was acute appendicitis complicated by appendiceal abscess in the setting of De Garengeot hernia with secondary intestinal obstruction. Postoperative antibiotic therapy comprised intravenous ceftriaxone and metronidazole. The nasogastric tube was removed on postoperative day three, and the patient was discharged on postoperative day ten without complications.
Conclusion:
De Garengeot hernia complicated by appendicitis and intestinal obstruction represents a diagnostic challenge owing to its rarity and the non-specific nature of its clinical presentation. It should be suspected in elderly patients presenting with a painful femoral hernia associated with signs of intestinal obstruction, particularly in obese women, in whom body habitus may impair physical examination and conceal the hernial finding. A high index of clinical suspicion, contrast-enhanced multiplanar abdominopelvic CT, and timely surgical intervention are essential to establish the diagnosis and prevent life-threatening complications.
Related Concept Videos
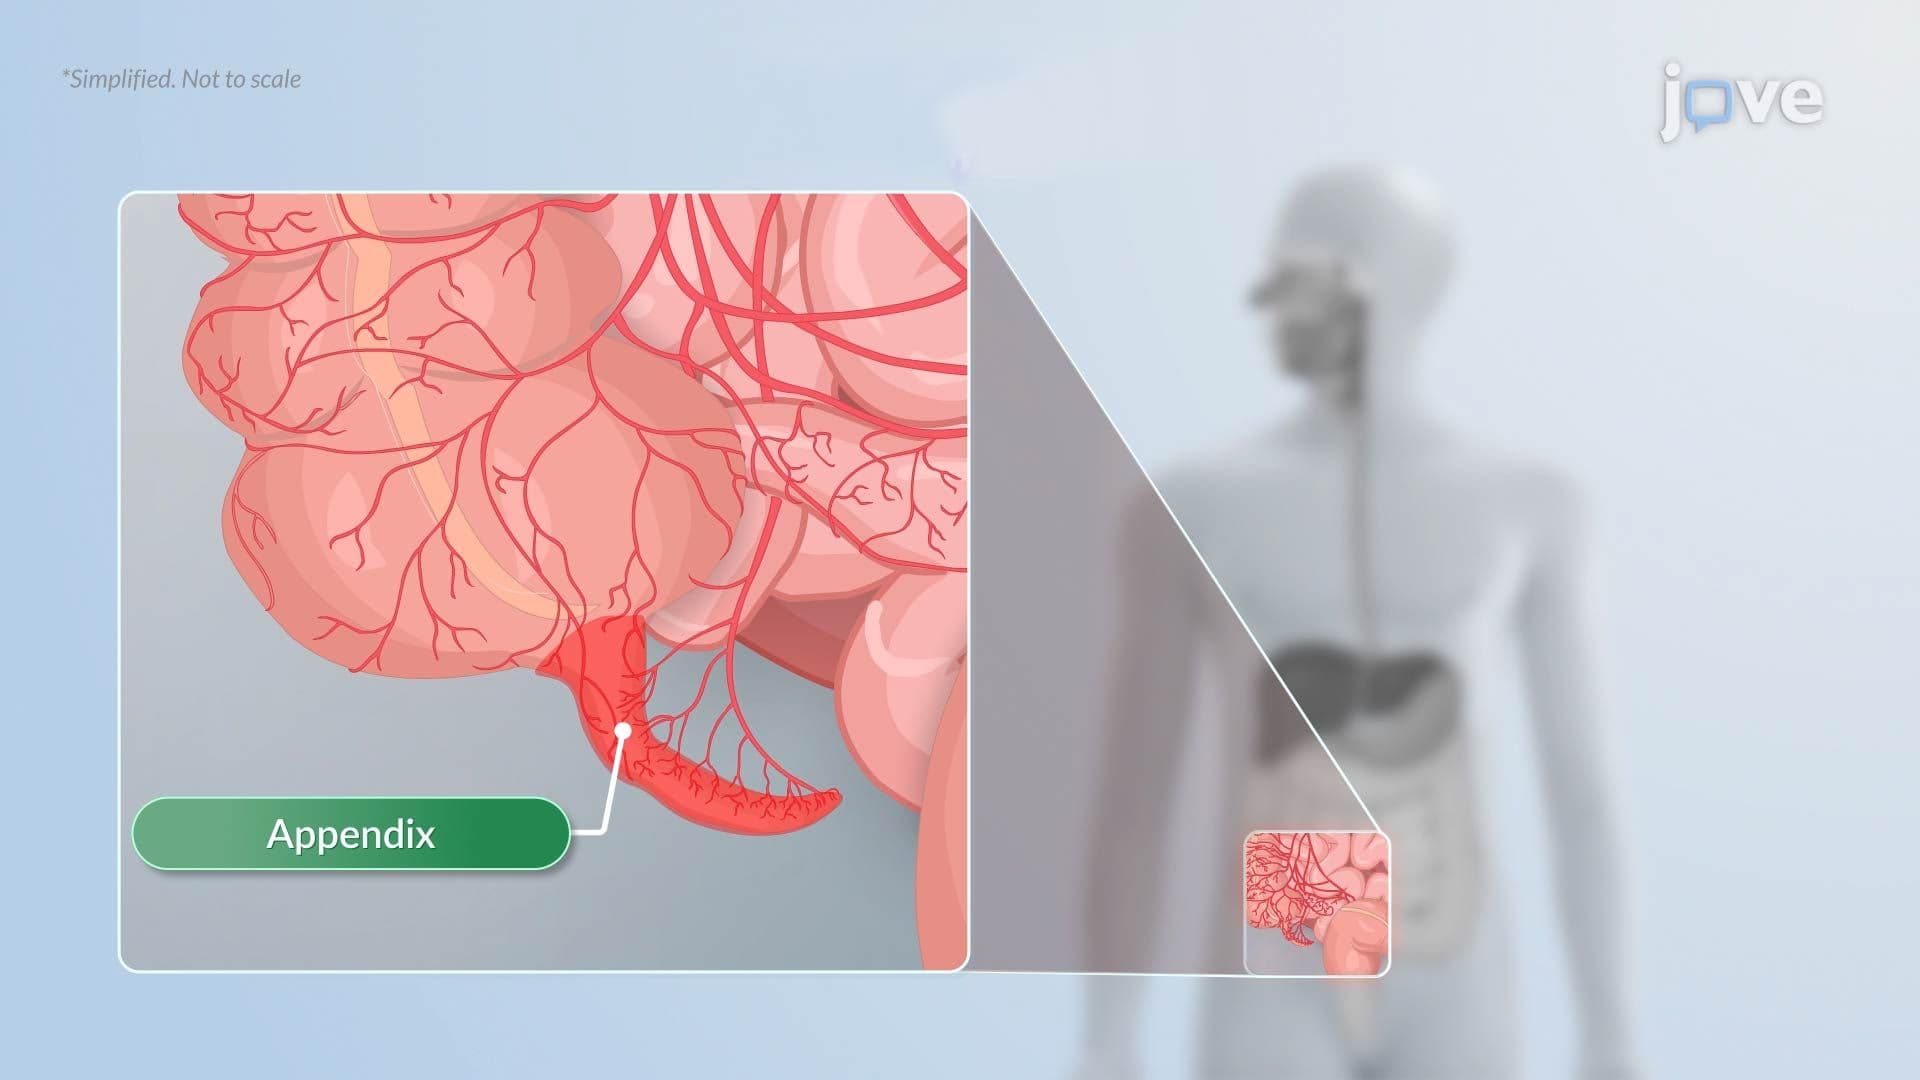 01:19
Appendicitis
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:29
Intestinal Obstruction I: Introduction
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:07
Intestinal Obstruction II: Pathophysiology