Related Experiment Video
Updated: Aug 29, 2026
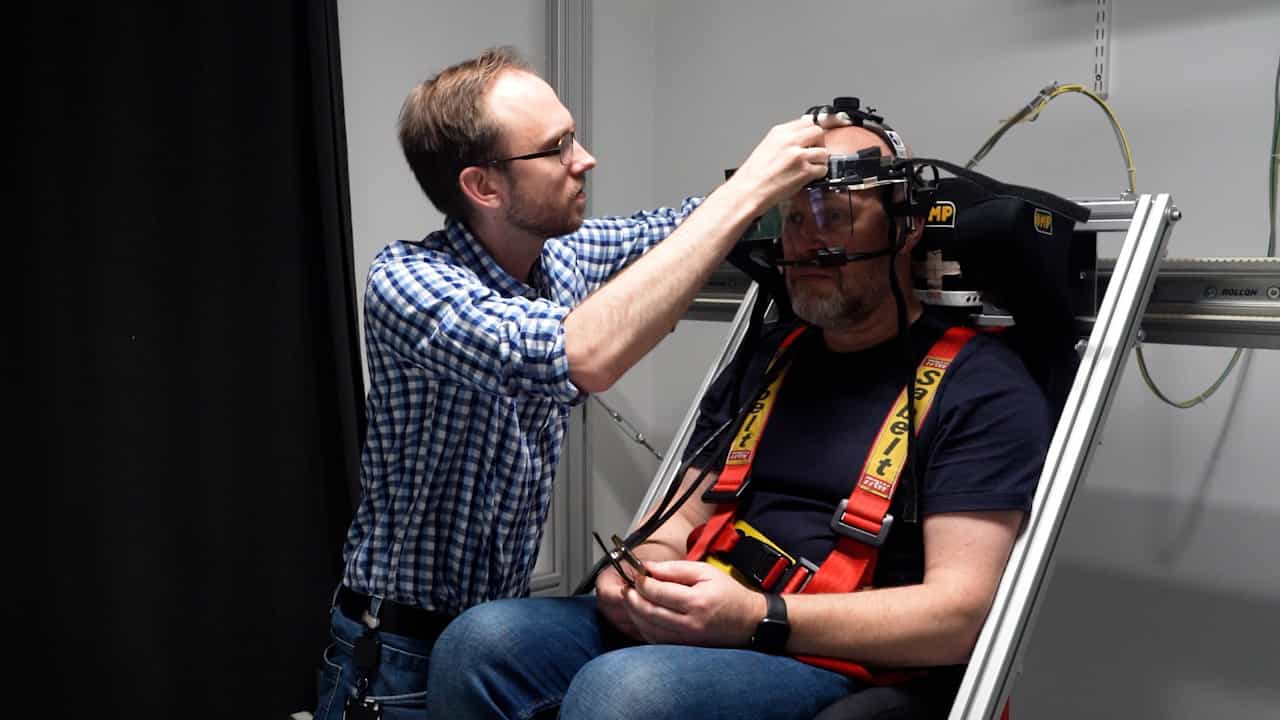

Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Distinguishing isolated epileptic vertigo/dizziness from vestibular paroxysmia: Clinical clues from a retrospective
Xi Lu1, Yufen Peng1, Bo Fang1
1Department of Neurology, The First Affiliated Hospital, Jiangxi Medical College, Nanchang University, Nanchang, 330047, China.

Purpose:
Recurrent brief vestibular attacks are often evaluated as peripheral disorders, but some reflect epileptic vestibular seizures requiring electroencephalographic (EEG) assessment. We sought to identify clinical clues distinguishing isolated epileptic vertigo/dizziness (iEVD) from vestibular paroxysmia (VP).
Methods:
We retrospectively compared 50 patients with iEVD and 50 with VP at a tertiary centre. Vestibular symptom descriptions were summarised according to the predominant motion percept documented in the initial clinical account. Clinical features, associated symptoms, EEG findings, and short-term treatment outcomes were reviewed. Independent discriminators were assessed using Firth's penalised logistic regression.
Results:
Attack frequency independently distinguished iEVD from VP (odds ratio 0.024, 95% confidence interval 0.005-0.120, p < 0.001); daily attacks were uncommon in iEVD but typical in VP (10.0% vs. 88.0%). Heave-like vertical linear motion (floating, rising, sinking, or falling) occurred in 13/50 patients with iEVD (26.0%) and in no patient with VP (specificity 100.0%, 95% CI 92.9-100.0; sensitivity 26.0%). Cortical sensory auras (auditory or visual hallucinations, paraesthesia) affected 20.0% of iEVD patients; auditory hallucinations occurred only in iEVD and unilateral tinnitus only in VP. EEG abnormalities most often involved the temporal region (56.0%).
Conclusion:
Lower attack frequency and heave-like vertical linear motion help distinguish iEVD from VP. Heave-like motion is specific but insensitive, so its absence does not argue against iEVD. Targeted history-taking on motion quality and associated symptoms may help physicians identify patients warranting epilepsy or EEG evaluation before epileptic vestibular events are misclassified as VP.

Related Concept Videos
 01:15
Equilibrium and Balance
 01:29
The Vestibular System