Related Experiment Video
Updated: Aug 29, 2026
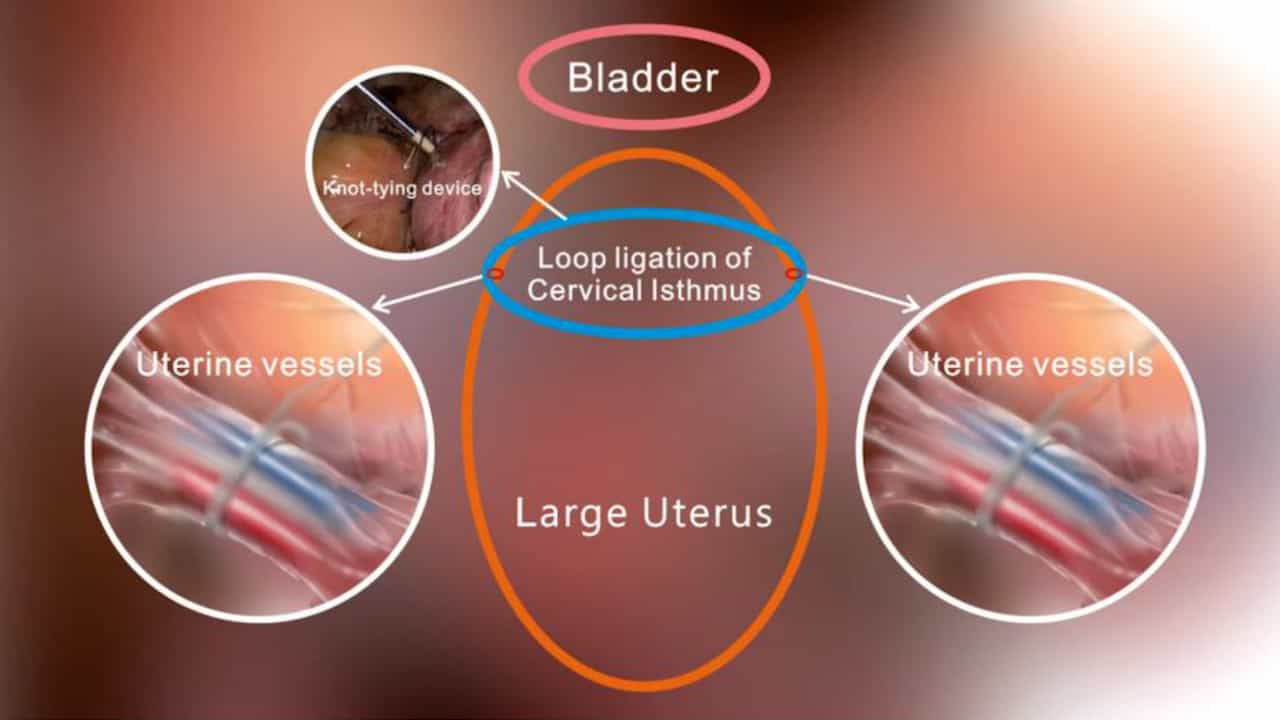
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Low Lying Obstacles: Approaches to Cervical Fibroid During Hysterectomy
Shobha Sridhar1, Maria C Alzamora Schmatz1, Lindsey Valentine1
1Minimally Invasive Gynecologic Surgery, Obstetrics and Gynecology Institute, Cleveland Clinic Foundation, Cleveland, Ohio (all authors).

Objective:
To show techniques for safe dissection, optimizing visualization, and reducing blood loss when approaching cervical fibroids during hysterectomy.
Setting:
Tertiary care academic medical center.
Participants:
Two patients with symptomatic uterine fibroids involving the cervix who underwent total laparoscopic hysterectomy. Case 1 is a 51-year-old patient with a multifibroid uterus and a 5.6 cm cervical fibroid filling the anterior lip of the cervix. Case 2 is a 44-year-old patient with an 11.1 cm posterior uterine body, lower uterine segment subserosal fibroid. (The patient(s) included in this video gave consent for publication of the video and posting of the video online, including social media, journal websites, scientific literature websites (such as PubMed, ScienceDirect, Scopus, etc.), and other applicable sites.) INTERVENTION: Total laparoscopic hysterectomy was safely completed in both cases. The techniques that are reviewed include identification of the ureter and ureterolysis if possible, use of the fibroid pseudocapsule to help mobilize the bladder, identification and isolation of the uterine artery at its origin, use of vasopressin for improved hemostasis, a single-tooth tenaculum for fibroid manipulation, use of vaginal retractors to delineate the cervicovaginal junction, and use of the cervical fibroid for the colpotomy border. These techniques are discussed in the context of the altered anatomy and increased surgical complexity posed by cervical fibroids, especially those distorting the lower uterine segment and vaginal cuff border.
Conclusion:
Cervical fibroids can significantly distort pelvic anatomy and increase surgical complexity during hysterectomy. A deliberate stepwise approach, including early vascular control, ureter identification, strategic retraction, and thoughtful colpotomy planning, can reduce complications and optimize outcomes. This video provides a practical framework for approaching these challenging cases with safety and confidence.