Related Experiment Video
Updated: Aug 30, 2026


Safety Precautions and Operating Procedures in an (A)BSL-4 Laboratory: 1. Biosafety Level 4 Suit Laboratory Suite Entry and Exit Procedures
Published on: October 3, 2016
When knowledge is not enough: infection prevention and control practices and occupational biological exposures among
Tanusha Singh1, Kundai Mavis Makozho1
1Department of Environmental Health, Faculty of Health Sciences, University of Johannesburg, Johannesburg, South Africa.

Background:
Dental professionals are routinely exposed to occupational biological hazards, yet evidence from low-resource settings remains limited. This study assessed infection prevention and control (IPC) knowledge and practices, quantified occupational biological exposures, and identified factors associated with sharps injuries and occupational infections.
Methods:
A cross-sectional analytical study was conducted among 220 dental professionals in Bulawayo, Zimbabwe. Data were collected using a structured self-administered questionnaire and analysed using descriptive statistics and bivariate and multivariable logistic regression. Adjusted odds ratios (aORs) with 95% confidence intervals (CIs) were reported.
Results:
Lifetime sharps injury was reported by 61.2% of participants, 14.7% reported a sharps injury during the preceding 12 months, and 18.3% reported an occupational infection. Despite high awareness of core IPC principles, occupational exposure remained common. Recent sharps injury was independently associated with early-career role (aOR = 4.01; 95% CI: 1.26-12.76), eye protection use (aOR = 2.88; 95% CI: 1.21-6.84), poor hand hygiene adherence (aOR for often/always = 0.34; 95% CI: 0.12-0.97), and lower perception scores (aOR = 0.49 per unit increase; 95% CI: 0.32-0.75). Public-sector employment was independently associated with self-reported occupational infection (aOR = 2.66; 95% CI: 1.25-5.64).
Conclusion:
Dental professionals in Bulawayo experienced substantial occupational biological hazards despite generally high awareness of IPC principles. These findings demonstrate that IPC knowledge alone is insufficient to prevent occupational exposure. Strengthening competency-based IPC training, post-exposure management, institutional IPC systems, and targeted support for early-career dental professionals can reduce occupational injuries and occupational infections.

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:20
Infection
The chain begins with pathogens: bacteria, viruses, fungi, prions, or parasites such as protozoa helminths. These can be present on the skin as transient or resident flora, or they can be acquired from the environment. Identifying and treating the type of infection and...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
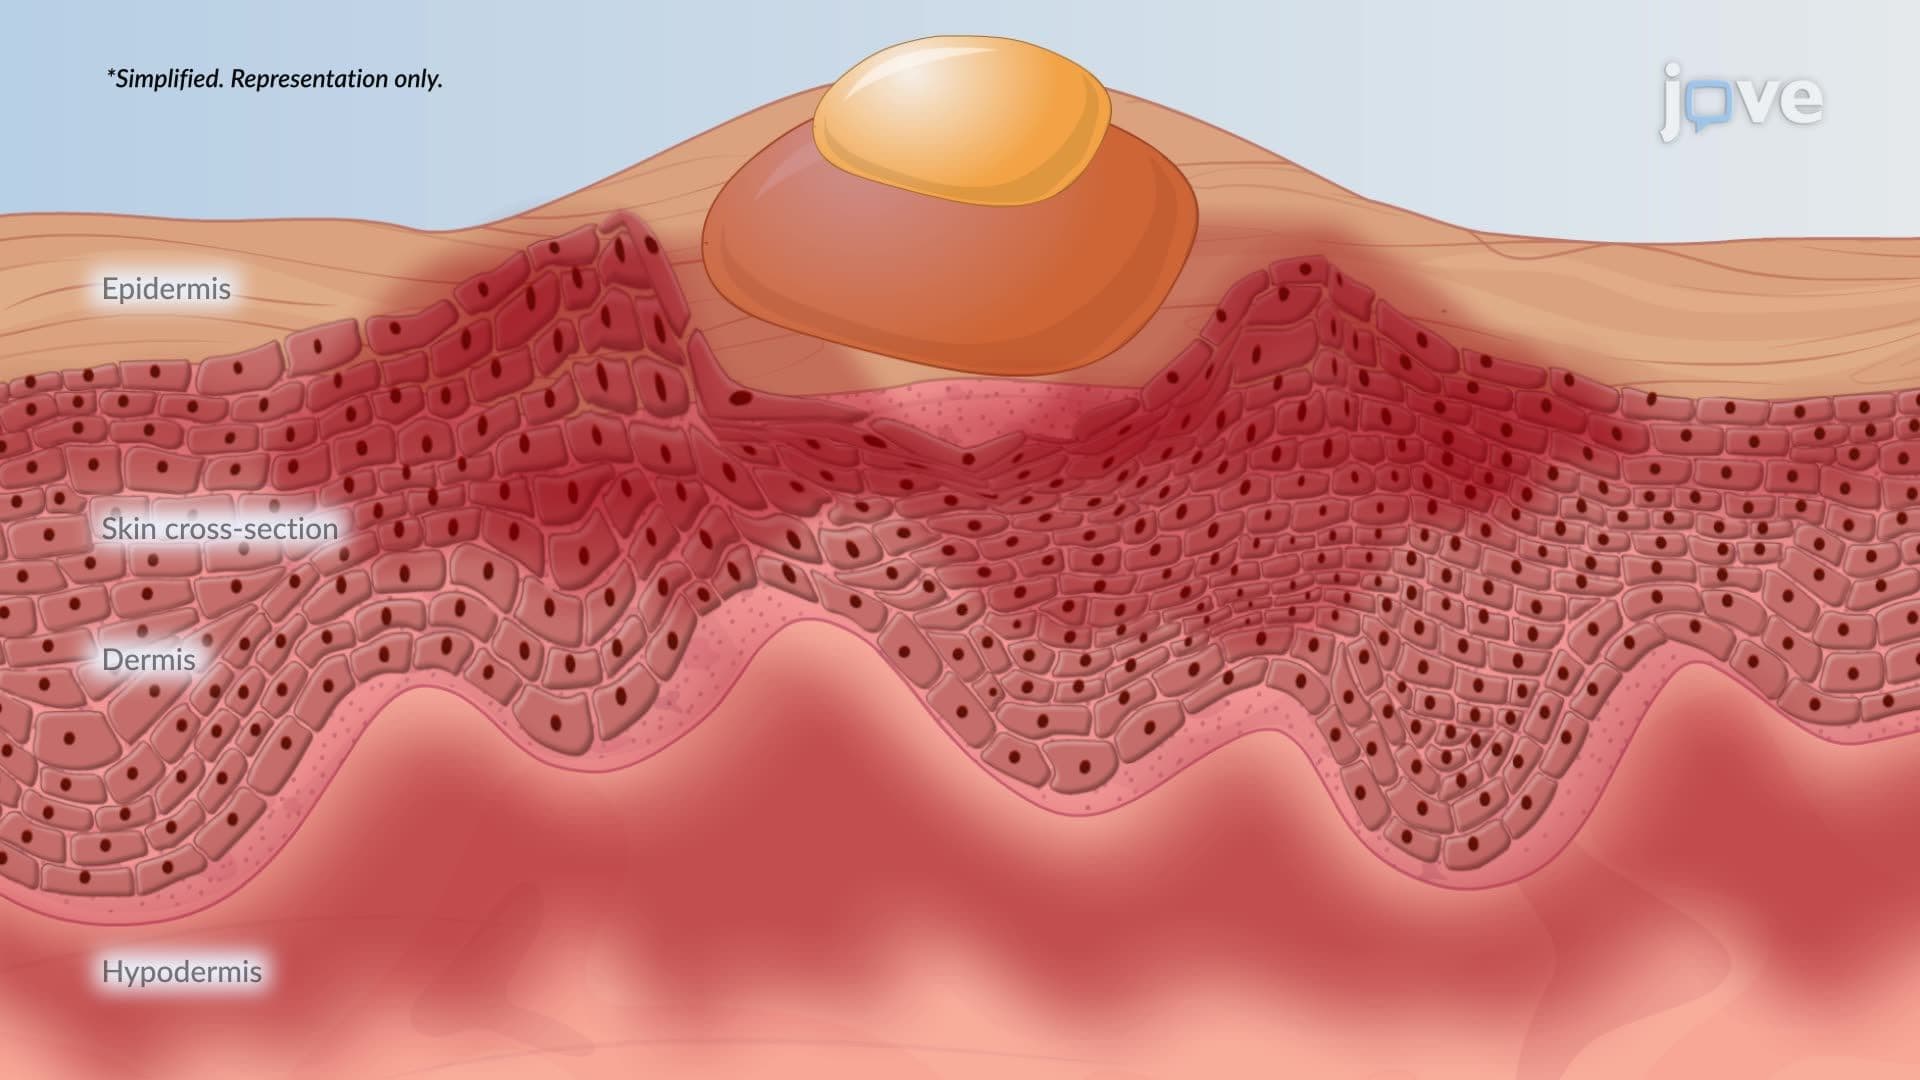 01:24
Smallpox
 01:17
Transmission-based Precautions I: Contact, Enteric, and Droplets
Contact Precautions:
Contact precautions are the measures taken to prevent the transmission of infectious agents, especially epidemiologically important microorganisms such as MRSA or influenza, primarily transmitted through direct or indirect contact with an...