Related Experiment Video
Updated: Aug 30, 2026

An Immunocompetent Murine Model for Laser Interstitial Thermal Therapy of Glioblastoma
Published on: November 15, 2024
Outcomes of Laser Interstitial Thermal Therapy-Augmented Surgery in the Management of Subcortical Glioblastoma
Hsien-Chung Chen1,2, Anudeep Yekula3, Marcus W Weimar1
1Department of Neurosurgery, Warren Alpert School of Medicine, Rhode Island Hospital, Brown University, Providence, Rhode Island, USA.

Background And Objectives:
Subcortical glioblastomas present surgical challenges owing to their proximity to critical anatomy. In this study, we assessed the utility of laser interstitial thermal therapy (LITT) in the management of subcortical glioblastomas.
Methods:
Clinical outcomes were evaluated in 80 consecutive patients with subcortical glioblastoma (isocitrate dehydrogenase wild-type, H3K27 nonmutant) treated surgically between 2017 and 2025. During this time period, LITT was increasingly incorporated into stereotactic needle biopsy (SNB) and surgical resection (SR) workflows, enabling comparisons between SNB vs SNB + LITT and between SR only vs planned subtotal resection (STR) + LITT.
Results:
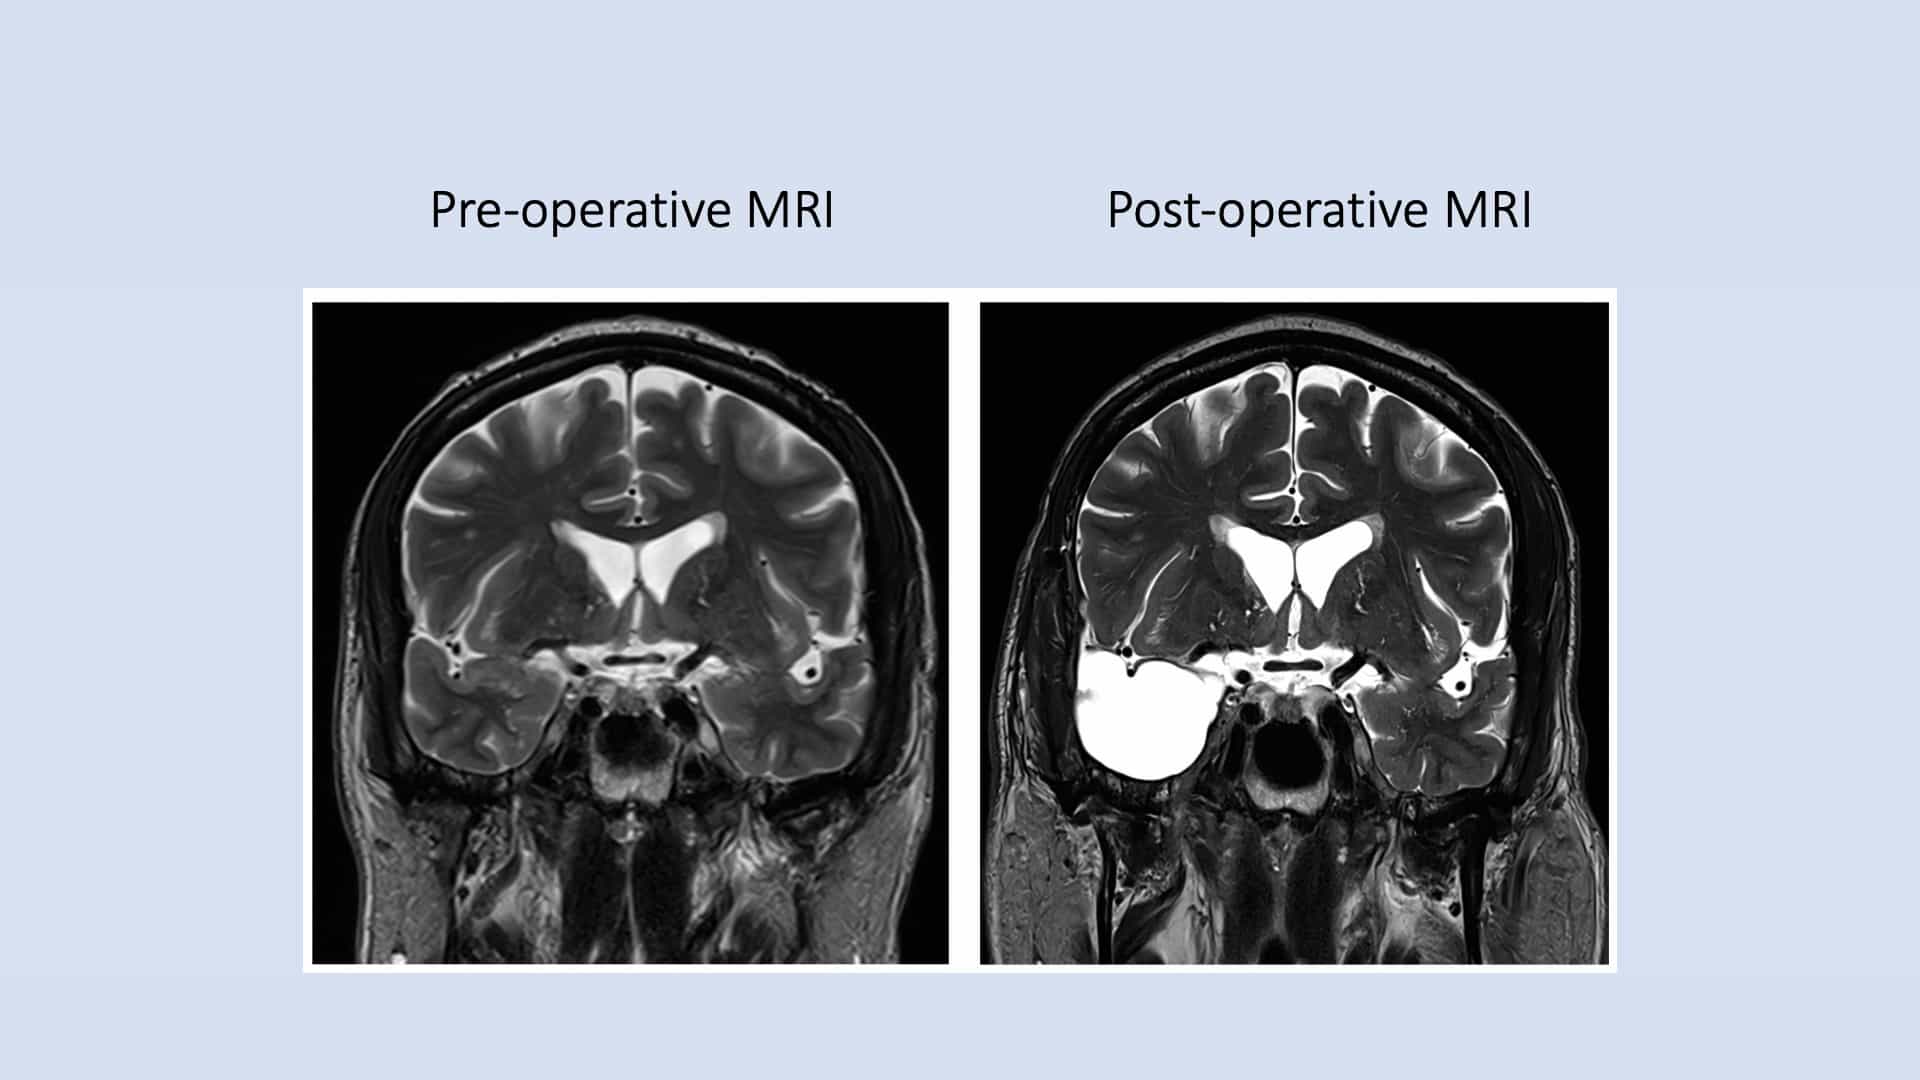
Among 46 treatments involving SNB, 24 underwent SNB only and 22 SNB + LITT. Lesion size was similar between these groups (1.72 ± 0.38 vs 1.92 ± 0.36 cm, P = .07), with comparable procedural morbidity (4.2% vs 4.5%, P = 1.0). In newly diagnosed glioblastoma, SNB + LITT was associated with improved overall survival compared with SNB alone (median 375 vs 162 days, P = .0012). Thirty-four patients underwent resections (18 SR, 16 STR + LITT). Lesion size was comparable between these cohorts (3.77 ± 0.68 vs 3.74 ± 0.83 cm, P = .9) as was the extent of cytoreduction (77.8% vs 93.8%, P = .34), but STR + LITT was associated with fewer permanent postoperative deficits (0% vs 27.8%, P = .047). Survival did not differ between STR + LITT and SR (median 368 vs 289 days, P = .43). Across all patients, postoperative motor deficits were associated with worse survival (112 vs 254 days, P < .001).
Conclusion:
Our results support incorporating LITT as a staged procedure into planned STR or in conjunction with SNB in the management of subcortical glioblastoma. Postoperative motor deficit is associated with poor survival outcomes.