Related Experiment Video
Updated: Aug 31, 2026
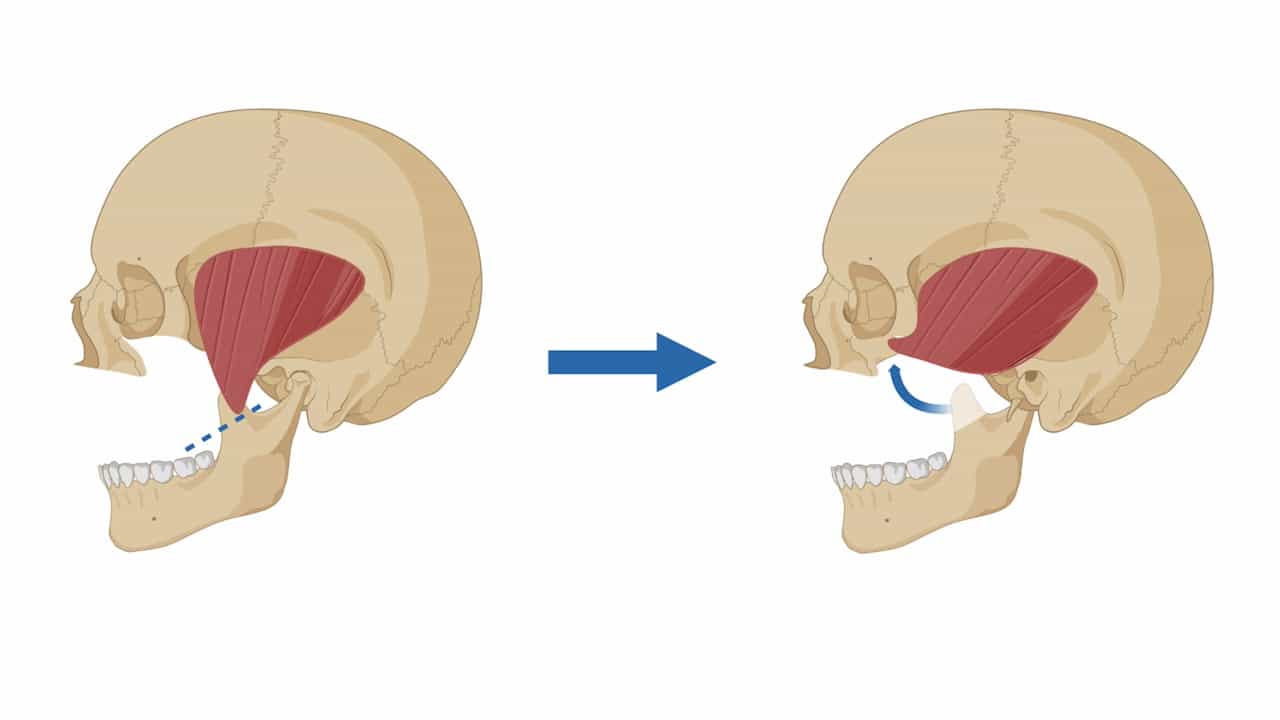

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
What are the local surgical adjuncts to enhance paranasal augmentation in Le Fort 1 osteotomies? A systematic review
Celestine Yu Qing Teo1, Shili Ng1, Cheryl Ker Jia Lee2
1National Dental Centre Singapore, Department of Oral and Maxillofacial Surgery, 5 Second Hospital Ave, Singapore 168938; National University of Singapore, Faculty of Dentistry, Discipline of Oral and Maxillofacial Surgery, 9 Lower Kent Ridge Road, Singapore, 119085.

Background:
Adjunctive surgical procedures may be performed simultaneously with Le Fort I osteotomy (LF1) to ensure adequate paranasal augmentation.
Aims:
The objective of this systematic review is to integrate current knowledge on concurrent local surgical methods to supplement LF1 to enhance paranasal volume.
Results:
Twenty-two studies involving 463 patients were reviewed. Four subgroups of local surgical adjuncts were identified. Subgroup 1 (9 studies, 245 patients) consisted of high and quadrangular Le Fort I modifications. This subgroup had the most robust evidence in terms of paranasal volume augmentation and stability. Subgroup 2 (6 studies, 83 patients) consisted of pedicled buccal fat pad (BFP) and free intra-oral autogenous bone block grafts. While the two types of grafts were shown to be useful in paranasal augmentation, there are insufficient long-term studies to demonstrate their stability. The third subgroup (4 studies, 103 patients) had no reported complications and showed good stability, but the amount of augmentation was modest. The last subgroup (3 studies, 32 patients) had the weakest degree of evidence.
Conclusion:
All four types of surgical adjuncts demonstrated clinical benefit based on subjective outcome assessments. However, given the predominance of low-level evidence, firm conclusions regarding efficacy cannot be drawn. When compared, subgroup 1 showed the best evidence whereas subgroup 4 showed the least. Subgroup 2 lacked evidence in stability while subgroup 3 showed limited amount of paranasal augmentation.