Related Experiment Video
Updated: Sep 2, 2026
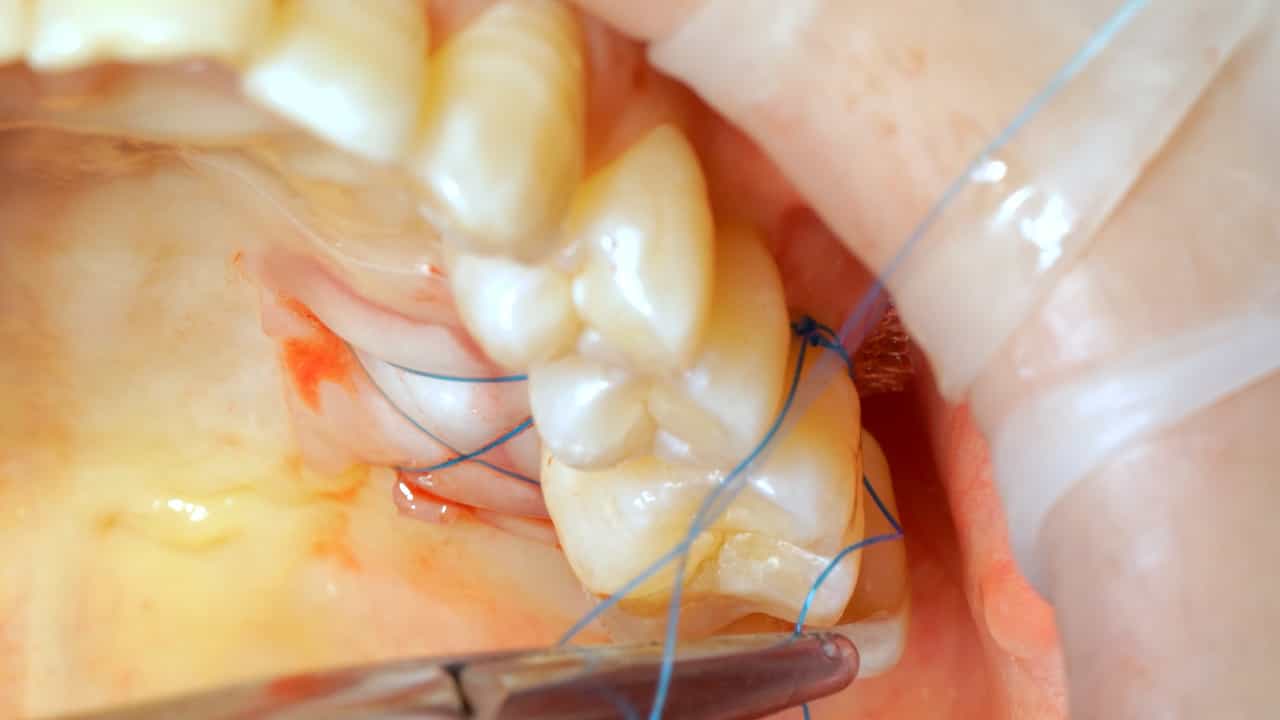

A Simplified Protocol for Protecting Palatal Soft Tissue Donor Sites Using an Oral Mucoadhesive Bandage
Published on: February 17, 2026
Emergency management protocols for major complications after oral and maxillofacial surgery: emphasis on airway and
Sungyeop Lee1, Sung-Yun Hwang1, Kyu-Bum Kim1
1Department of Oral and Maxillofacial Surgery, Pusan National University, Yangsan, Korea.

Objectives:
Postoperative hemorrhage and airway obstruction remain major life-threatening complications following oral and maxillofacial surgery despite advances in surgical techniques and perioperative care. This study aimed to retrospectively characterize the clinical patterns, timing, and management of postoperative hemorrhagic and airway emergencies over a 15-year period and, based on these institutional data and a review of the literature, to propose a practical integrated framework for postoperative emergency management.
Materials And Methods:
A retrospective review was conducted of patients who underwent major oral and maxillofacial surgery at a university dental hospital between 2010 and 2025. Major bleeding events were defined as postoperative hemorrhage requiring reoperation or embolization, while major airway events included unplanned airway intervention or emergency tracheostomy. For airway analysis, patients undergoing malignant tumor resection were divided into an emergency tracheostomy group and an elective tracheostomy group. The Cameron scoring system was retrospectively applied.
Results:
Twenty patients required intervention for postoperative bleeding, with 70% of events occurring after major surgery. Five of eight orthognathic surgery patients developed hemorrhage within 72 hours postoperatively and required surgical hemostasis. Most bleeding events occurred independently of coagulation disorders. Transarterial embolization was performed in 13 patients, although only one case was directly related to emergency postoperative hemorrhage. Tracheostomy was performed in 24 patients, including 13 following oral cancer surgery. Emergency tracheostomy was most frequently required in patients with malignant tumors or severe infections. Mean Cameron scores were comparable between the emergency and elective tracheostomy groups (6.00 and 6.17, respectively).
Conclusion:
Postoperative hemorrhage and airway compromise remain significant complications in oral and maxillofacial surgery. Bleeding events were more closely associated with surgical extent than patient-related comorbidities. While the Cameron score may assist preoperative airway planning, postoperative clinical assessment remains essential. A structured approach incorporating bleeding control, airway protection, and selective use of embolization may improve patient safety and postoperative outcomes.
Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:26
Tonsillitis II: Management
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:22
Aneurysm IV: Nursing Management
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.