Related Experiment Video
Updated: Sep 2, 2026


Body Composition and Metabolic Caging Analysis in High Fat Fed Mice
Published on: May 24, 2018
Mapping organ fat distribution and body composition: towards precision profiling of cardiometabolic disease risk
Yeshe Manuel Kway1, Zahra Raisi-Estabragh2, Georgios Vavilis1,3
1Oxford Centre for Clinical Magnetic Resonance Research (OCMR), Division of Cardiovascular Medicine, Radcliffe Department of Medicine, University of Oxford, Oxford, UK.

Background And Aims:
Adiposity exerts multisystem insults that influence multiple organs and physiological pathways. This underscores the need for a systems-level framework integrating key organ fat measurements to disentangle the heterogeneous pathways through which adiposity shapes differential cardiometabolic risk profiles. Such an approach could advance mechanistic understanding and enable more precise risk stratification.
Methods:
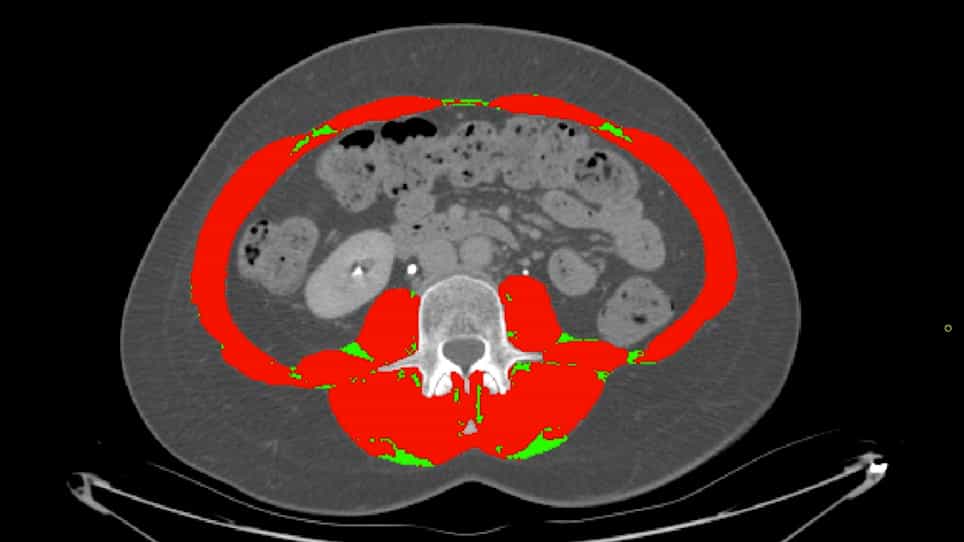
In the UK Biobank, 24 935 participants without overt cardiac disease were studied. Six adiposity phenotypic groups were identified using unsupervised clustering of magnetic resonance imaging-derived adiposity measures (subcutaneous, visceral, pericardial, liver, pancreatic, and muscle fat). These phenotypes were characterised in terms of body composition, cardiac remodelling, and the development of major cardiometabolic diseases.
Results:
Each phenotype showed distinct organ-dominant fat accumulation and body composition pattern. A pancreatic fat dominant phenotype, marked by visceral adiposity and sarcopenic features, showed a cardiorenal-metabolic risk profile. A muscle fat dominant phenotype, characterised by subcutaneous adiposity and sarcopenic features, was associated with increased heart failure risk. While pericardial fat dominant and liver fat dominant phenotypes did not associate with cardiac disease risk, they exhibited distinctive cardiac remodelling patterns, revealing phenotypespecific metabolic-cardiac interactions. Lastly, normal-weight individuals with mild multi-organ fat showed elevated chronic ischaemic heart disease risk, highlighting the value of phenotype-based risk assessment beyond general weight measures.
Conclusions:
Distinct patterns of multi-organ fat accumulation were associated with differential body composition, cardiac remodelling, and cardiometabolic disease risk profiles. The identified adiposity phenotypic groups capture clinically meaningful heterogeneity across the cardiorenal-metabolic spectrum and may inform future personalised, multisystem approaches to prevention and management.