Related Experiment Video
Updated: Sep 2, 2026
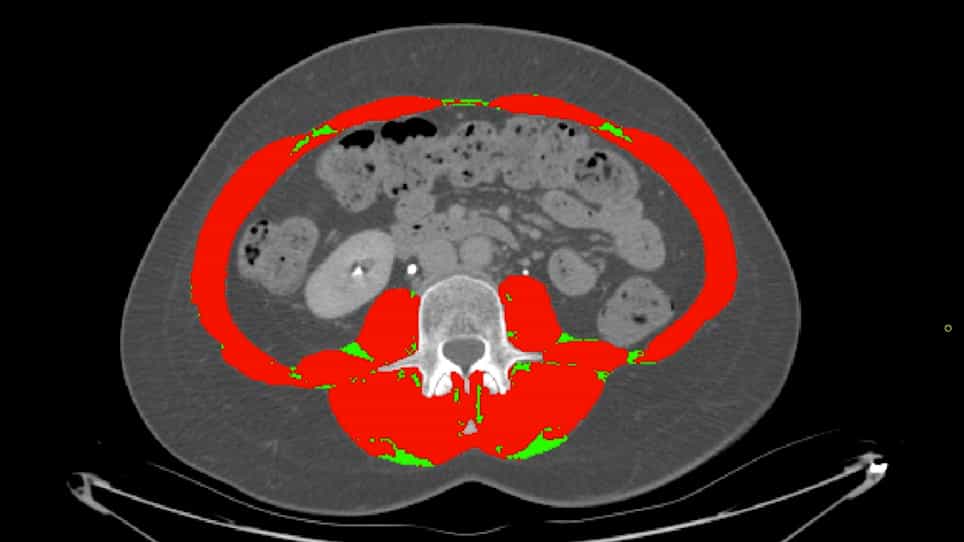

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Computed tomography-defined sarcopenia is associated with nutritional vulnerability and short-term clinical burden in
Ruoxiang Sun1,2, Hua Jiang1,2, Xu Li1
1Department of Clinical Nutrition, The Second Hospital of Dalian Medical University, Dalian, China.

Introduction:
Sarcopenia in lymphoma remains insufficiently characterized, particularly when defined by both computed tomography-derived skeletal muscle mass and muscle strength. This study aimed to investigate the prevalence, nutritional correlates, auxiliary discriminatory indicators, and short-term clinical implications of computed tomography-defined sarcopenia in hospitalized patients with lymphoma.
Methods:
This single-center cohort study included 136 hospitalized patients with lymphoma. Sarcopenia was defined as reduced skeletal muscle index at the third lumbar vertebra combined with low handgrip strength. Clinical, nutritional, laboratory, lymphoma-specific, and short-term outcome variables were compared between patients with and without sarcopenia. Multivariable logistic regression, receiver operating characteristic curve analysis, and Spearman correlation analysis were performed.
Results:
Computed tomography-defined sarcopenia was present in 24.26% of patients. Patients with sarcopenia more frequently had reduced recent food intake, reduced protein intake, poorer performance status, nutritional risk, and Global Leadership Initiative on Malnutrition-defined malnutrition. In the nutritional extension model, Geriatric Nutritional Risk Index below 98 (OR 8.238, 95% CI 2.748-24.690, p < 0.001) and reduced food intake during the previous week (OR 10.189, 95% CI 2.926-35.478, p < 0.001) were independently associated with sarcopenia. Geriatric Nutritional Risk Index and Patient-Generated Subjective Global Assessment showed comparable auxiliary discriminatory performance, with AUCs of 0.781 (95% CI 0.681-0.873) and 0.777 (95% CI 0.688-0.862), respectively. Baseline computed tomography-defined sarcopenia was associated with infection or febrile neutropenia (adjusted OR 2.82, 95% CI 1.20-6.60), in-hospital infection (adjusted OR 2.48, 95% CI 1.06-5.79), treatment tolerance events (adjusted OR 3.35, 95% CI 1.46-7.68), and treatment interruption (adjusted OR 2.73, 95% CI 1.09-6.82). Coexisting sarcopenia and Global Leadership Initiative on Malnutrition-defined malnutrition was observed in 16.2% of the cohort.
Discussion:
Computed tomography-defined sarcopenia was common in hospitalized patients with lymphoma and was associated with nutritional vulnerability, impaired treatment tolerance, and greater short-term clinical burden. These findings support integrating computed tomography-based muscle assessment with nutritional evaluation in this population.
