Related Experiment Video
Updated: Sep 3, 2026
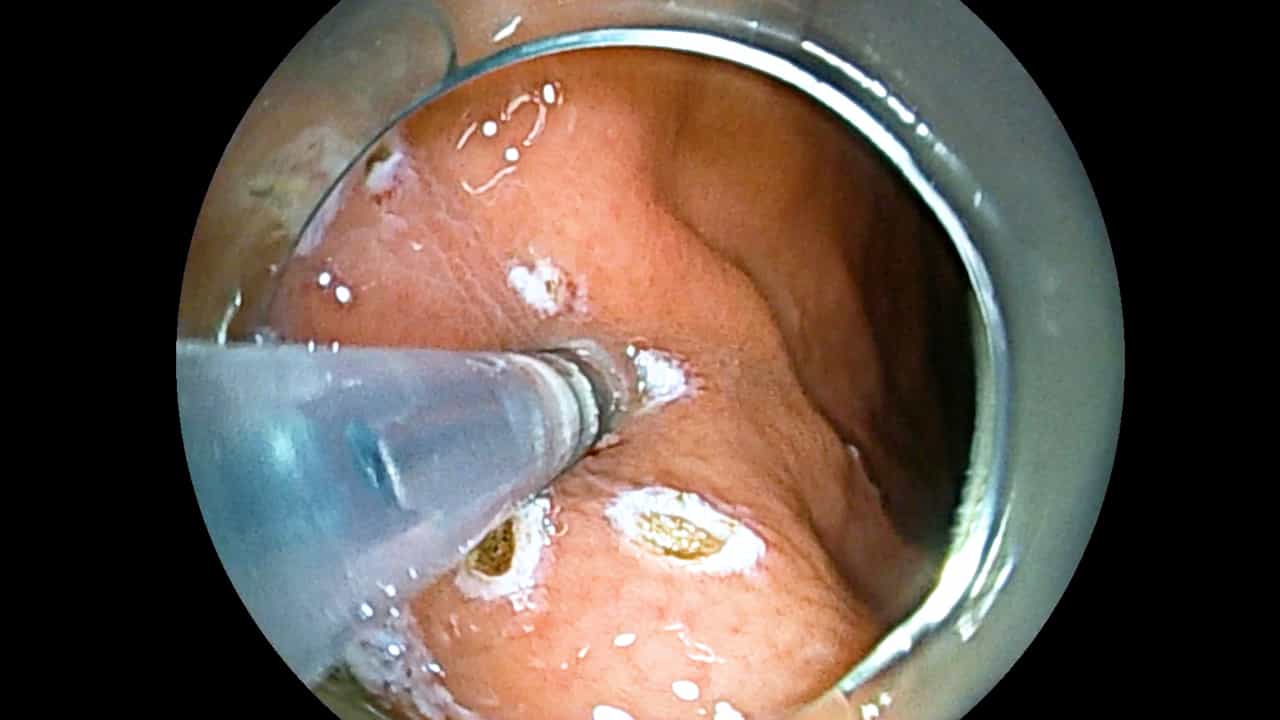

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Analysis of differences between early-onset and late-onset early gastric cancer treated with endoscopic submucosal
Linzhen Li1, Xuhua Xiao2, Yan Zhang1
1Department of Gastroenterology, First Affiliated Hospital of Wannan Medical College, Wuhu, Anhui Province, China.

Background And Purpose:
Gastric cancer is one of the most common cancers worldwide, with high incidence and mortality rates. The aim of this study was to analyze the differences in demographics, lesion morphology, and pathology between early-onset and late-onset early gastric cancer.
Patients And Methods:
A total of 37 early-onset early gastric cancer (EO-EGC) patients who underwent endoscopic submucosal dissection (ESD) were included in the study. For comparison, 37 late-onset early gastric cancer (LO-EGC) patients who underwent ESD during the same period were randomly selected as the control group. We compared EO-EGC and LO-EGC with respect to lesion size, location, color, postoperative pathological type, depth of invasion, and postoperative complications.
Results:
The LO-EGC group had significantly more hypertensive patients (P = 0.030) and larger lesions (P = 0.025) than the EO-EGC group. Pathologically, high-grade intraepithelial neoplasia was predominant in the EO-EGC group, while differentiated tubular adenocarcinoma was the main type in the LO-EGC group (P < 0.01). Lesions were mainly in the antrum in the EO-EGC group, and evenly distributed in the antrum, incisura angularis, and cardia in the LO-EGC group (P = 0.092, no statistical significance). No significant differences were observed between the two groups in gender (P = 0.183), diabetes mellitus (P = 1.000), coronary artery disease (P = 0.615), current or prior Helicobacter pylori infection (P = 0.485), lesion color (P = 0.358), invasion depth (P = 0.613), delayed postoperative bleeding (P = 1.000), delayed postoperative perforation (P = 0.247), or the need for additional surgery (P = 0.057).
Conclusions:
EO-EGC and LO-EGC exhibit significant differences in hypertension comorbidity, lesion size and pathological type, while their lesion distribution and perioperative clinical outcomes remain similar.
