Related Experiment Video
Updated: Sep 3, 2026

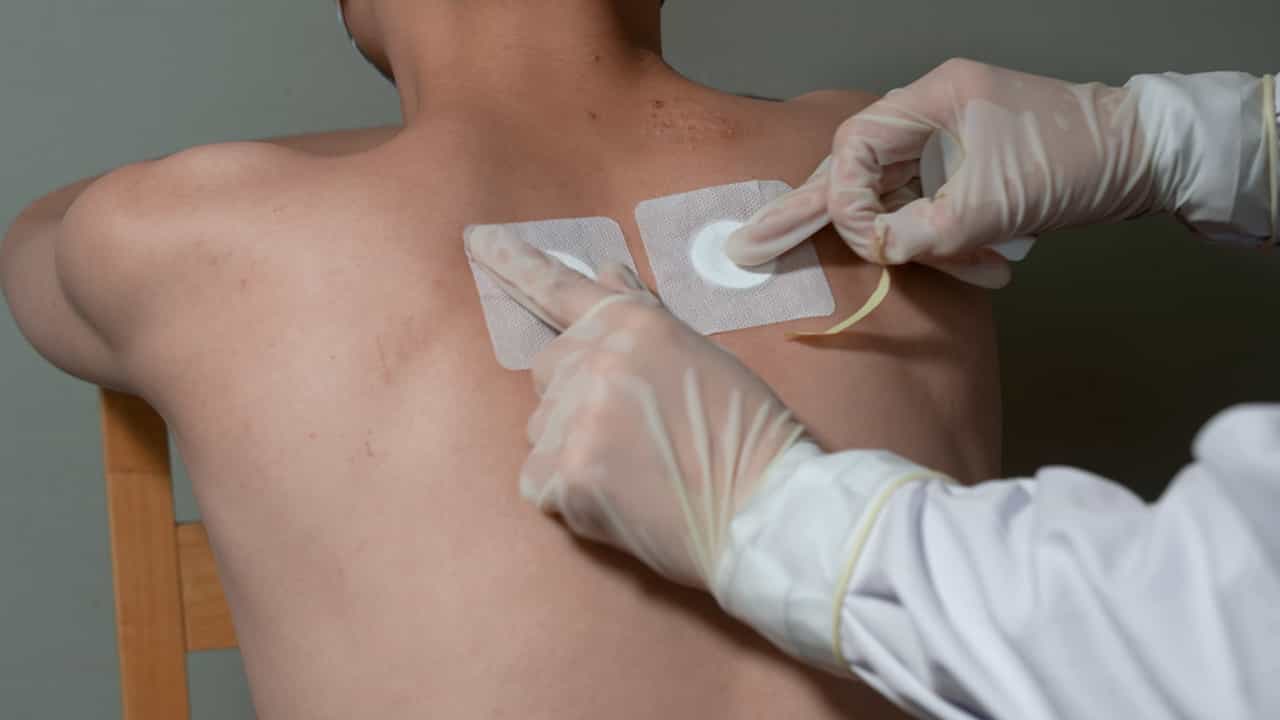
Auricular Acupuncture as a Traditional Chinese Medicine Therapy for Chronic Obstructive Pulmonary Disease Combined with Sleep Disorders
Published on: August 18, 2023
Network Structure of Dyspnea-Related Fear in Older Adults with Acute Exacerbation of COPD: A Biopsychosocial Network
Yuqing Yang1, Yu Zhang2,3, Qi Wu4
1Huzhou Central Hospital, Fifth School of Clinical Medicine of Zhejiang Chinese Medical University, Huzhou, Zhejiang, People's Republic of China.

Objective:
This study aimed to construct a biopsychosocial network model of dyspnea-related fear in older adults with acute exacerbation of chronic obstructive pulmonary disease (AECOPD), identify central and bridge nodes within the psychological system, and explore structural associations linking fear symptoms to emotional distress and functional impairment.
Methods:
A total of 317 hospitalized older adults with AECOPD were enrolled. Eight variables were assessed, including fear of dyspnea (Fear-D), fear of activity (Fear-A), anxiety (Anx), depression (Dep), psychological resilience (Psy-R), self-efficacy (Self-E), social support (Social-S), and activities of daily living (ADL). Gaussian Graphical Models (GGM) were estimated using EBICglasso. Centrality indices, bridge strength, node predictability (R2), and non-parametric bootstrap procedures were applied to evaluate network stability and accuracy.
Results:
Anxiety demonstrated the highest expected influence (z = 1.34), functioning as the most central node. Fear-D and Fear-A formed a cohesive dyad (edge weight = 0.51), while Anx and Dep exhibited the strongest edge (0.76). Protective factors (Self-E and Psy-R) showed negative associations with fear and anxiety nodes and significant bridge strength across communities. ADL was structurally embedded between psychological and emotional domains. Network stability analysis confirmed high robustness (CS coefficient > 0.70). The topology reflects a "indicating a structured pattern of fear-emotion co-occurrence and resource-related associations" configuration. Social support (Social-S) demonstrated near-zero centrality, suggesting minimal structural integration within the network under acute hospitalization conditions.
Conclusion:
Dyspnea-related fear in older AECOPD patients operates within a structured pattern of emotional and resource co-occurrence rather than a simple linear fear-disability pathway. Anxiety serves as the most central node, whereas self-efficacy functions as a cross-domain bridge node. Targeting high-centrality emotional nodes and strengthening resource bridges may optimize precision psychological intervention in AECOPD.
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction