Related Experiment Video
Updated: Sep 4, 2026
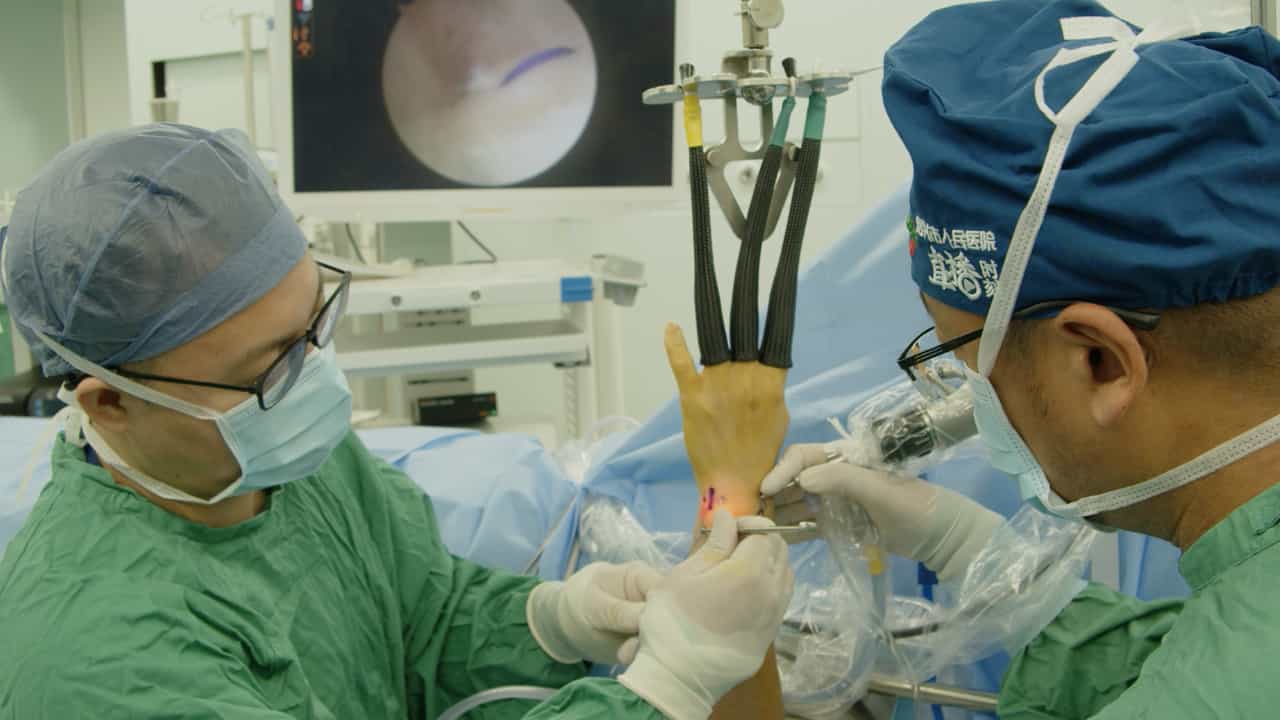

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Technical Factors Associated with Non-Union in Lunocapitate Fusion: A Retrospective Comparison with Four-Corner Wrist
Jian-Jiun Chen1,2, Jia-You Liou3, I-Ning Lo1,2
1School of Medicine, National Yang Ming Chiao Tung University, Taipei, Taiwan.

Abstract:
Background: Wrists with scapholunate advanced collapse (SLAC) and scaphoid non-union advanced collapse (SNAC) are frequently managed using either lunocapitate fusion (LCF) or four-corner fusion (4CF). However, technical factors within the LCF may have an important influence on union and complication rates. Methods: This retrospective study evaluated the radiographic and functional outcomes of 28 patients (LCF = 19, 4CF = 9) treated between 2015 and 2023, with particular emphasis on technical observations within the LCF group. The 4CF cohort was primarily included to provide a clinical context. Results: The fusion rates were significantly lower in the LCF group (47% vs. 100%, p = 0.0098), and the reoperation rates were higher (32% vs. 0%, p = 0.136). In the LCF group, all patients treated with a single screw (3/3) or with two partial-threaded screws (3/3) developed non-union. In contrast, the non-union rate was 43.8% (7/16) in the two-screw subgroup and 30.8% (4/13) when at least one fully threaded screw was used. Both procedures yielded comparable improvements in wrist range of motion (ROM), visual analogue scale (VAS), quick disabilities of the arm, shoulder and hand (QuickDASH), modified Mayo wrist scores (MMWS) and patient satisfaction at 1-year follow-up. Although LCF is less extensive, its outcomes in this study appear to be influenced by technical factors. Conclusions: The main finding of this study was that non-union and reoperation in the LCF group were clustered in cases with less robust fixation constructs and potentially insufficient preparation of fusion surfaces. These observations imply that the outcome of LCF may depend more on the surgical execution than on the procedure itself. These findings should be considered hypothesis-generating. Larger studies are required to clarify the potential technical risk factors for surgical failure. Level of Evidence: Level IV (Therapeutic).
