Related Experiment Video
Updated: Sep 4, 2026

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Blood pressure in haemodialysis: measurement, volume control and drug selection
Yoshitaka Furuto1, Daiki Yoshino1, Akio Namikawa1
1Department of Hypertension and Nephrology, NTT Medical Center Tokyo, Tokyo Japan.

Abstract:
Hypertension in haemodialysis is common, prognostically important, and difficult to manage because blood pressure measurement is often imprecise, extracellular volume is dynamic, and low blood pressure may reflect heart failure, frailty, impaired forward flow, autonomic dysfunction, or excessive ultrafiltration rather than therapeutic success. Contemporary evidence supports ambulatory blood pressure monitoring as the reference standard and home blood pressure monitoring as the most practical longitudinal method, while accepted targets remain unsettled. Treatment should begin with standardised assessment of interdialytic blood pressure burden and sodium-volume control through dietary sodium restriction, dialysate sodium consideration, dry-weight reassessment, ultrafiltration management, and adequate treatment time. This sequence helps distinguish true treatment resistance from pseudoresistance caused by dialysis-unit measurement artefacts, volume excess, short treatment time, sodium burden, medication nonadherence, poorly timed dosing, or dialytic drug removal. Once persistent hypertension is confirmed despite sodium-volume and dry-weight-oriented care, pharmacotherapy becomes necessary. Beta-blockers have the strongest outcome-linked support in haemodialysis, whereas calcium channel blockers (CCBs) are practical complementary agents, and conventional renin-angiotensin system (RAS) blockade is best reserved for selected indications. Mineralocorticoid receptor antagonists (MRAs) should be considered cautiously because recent large dialysis trials and updated meta-analytic evidence have not confirmed clear cardiovascular benefit. Sacubitril/valsartan is biologically plausible when hypertension coexists with heart failure with reduced ejection fraction, left ventricular dysfunction, recurrent congestion, or high natriuretic peptide burden. However, it should be framed as a promising but not yet established selective option rather than routine escalation therapy.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:18
Hypertension and Regulation of Blood Pressure
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:30
Blood Pressure
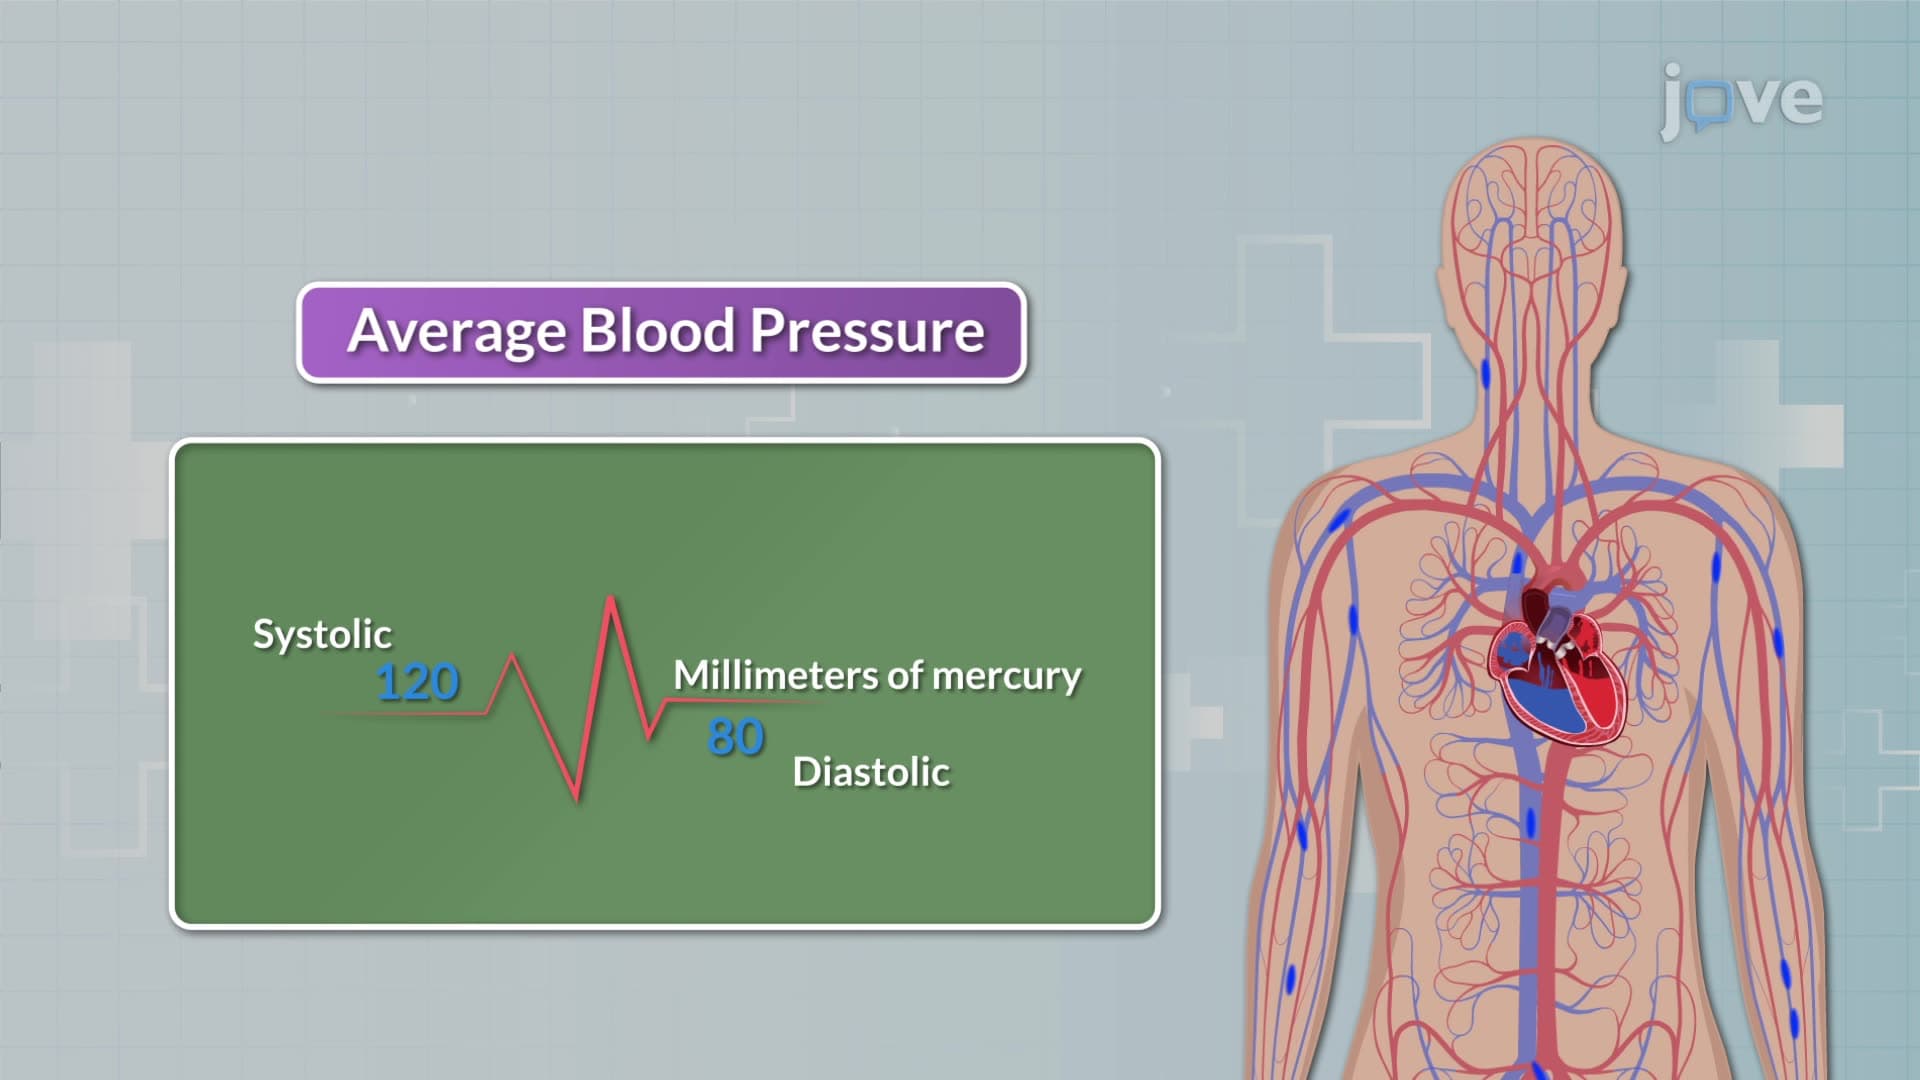
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:24
Blood Pressure
 01:24
Hemodialysis II: Procedure and Complications