Related Experiment Video
Updated: Sep 4, 2026
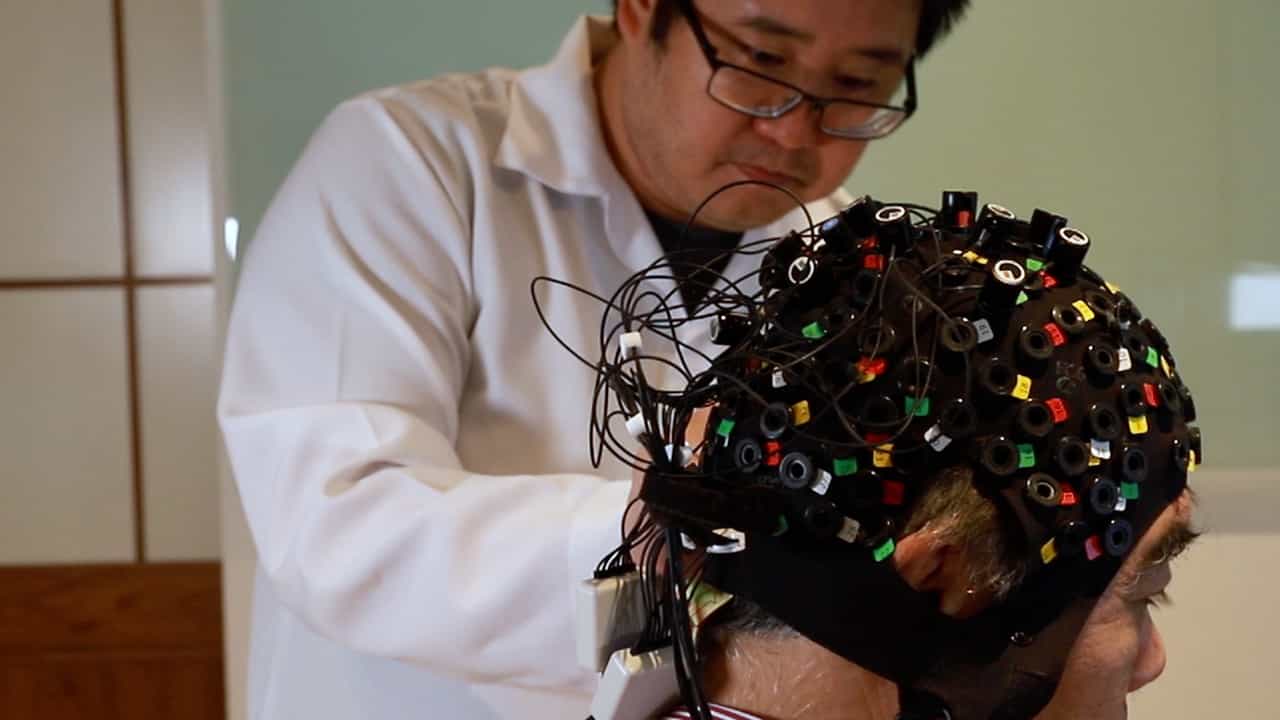

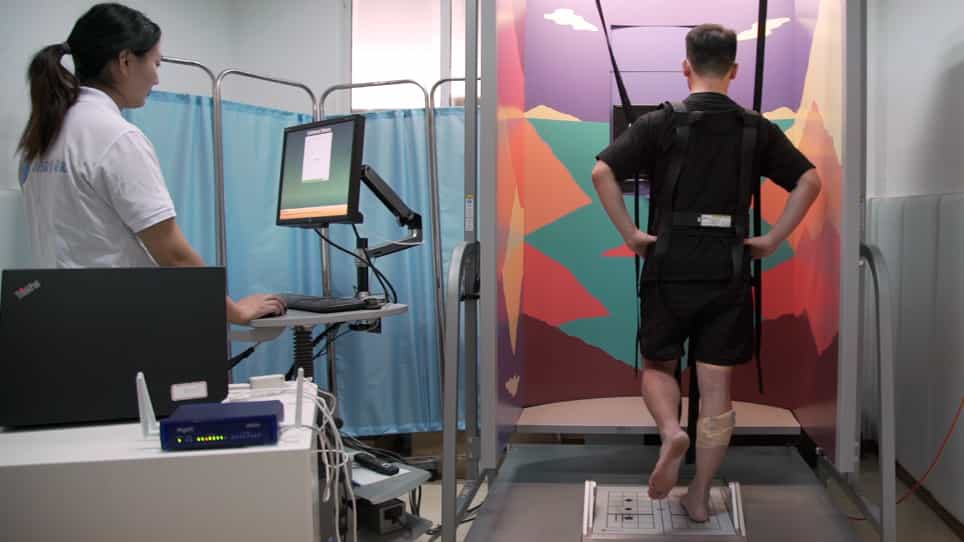
An Experiment Using Functional Near-Infrared Spectroscopy and Robot-Assisted Multi-Joint Pointing Movements of the Lower Limb
Published on: June 7, 2024
Altered activation patterns of sensorimotor cortex during level walking and stair climbing in patients with knee
Liming Jiang1, Kun Yang1, Tianzhong Zi1
1Department of Rehabilitation, Seventh People's Hospital of Shanghai University of Traditional Chinese Medicine, Shanghai, China.

Background:
Knee osteoarthritis (KOA) is characterized not only by peripheral joint pathology but also by mechanisms related to central sensitization. Previous studies have reported reduced activation of sensorimotor cortex during isolated joint movements in patients with KOA. However, cortical activation during walking remains unclear. This study aimed to investigate sensorimotor cortex activation during different walking tasks in patients with KOA to identify potential targets for central interventions.
Methods:
Nineteen patients with KOA and 18 demographically matched healthy controls (HCs) were recruited. Functional near-infrared spectroscopy (fNIRS) was used to monitor hemodynamic activity in bilateral primary motor cortex (M1), primary sensory cortex (S1), and somatosensory association cortex (SAC). Paired t-tests and mixed analysis of variance were performed to examine interhemispheric and between-group differences. Clinical assessments included pain intensity assessed by VAS and functional status assessed by WOMAC. Pearson correlation analyses were performed to examine associations between cortical activation and clinical scores.
Results:
HCs showed symmetrical bilateral cortical activation across tasks, whereas patients with KOA exhibited reduced cortical activation in the left hemisphere compared with the right. During stair tasks, activation in the left M1, S1, and SAC in patients with KOA was significantly lower than that in the right (P < 0.05). During level walking, only left S1 activation was significantly lower than the right (P < 0.05). Compared with HCs, patients with KOA also exhibited reduced activation in the left hemisphere, with significant lower activation in the left M1, S1, and SAC during stair tasks (P < 0.05), and reduced activation in the left S1 during level walking (P < 0.05). No significant between-group differences were observed in the right hemisphere. Additionally, activation in the left M1 and S1 was negatively correlated with VAS scores, and activation in the left M1 was negatively correlated with WOMAC function scores.
Conclusion:
Patients with KOA exhibit reduced contralateral sensorimotor cortex activation during walking tasks, with greater reductions as task difficulty increases. Lower activation in contralateral M1 and S1 is associated with higher pain and poorer functional status, highlighting the role of central mechanisms in KOA and potential targets for neuromodulatory interventions.