Related Experiment Video
Updated: Sep 5, 2026

Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
ICG Fluorescence-Guided Anatomical Navigation During Robotic Pancreatoduodenectomy: Pancreatic Head Arterial
Masahiro Yamane1,2, Kosuke Kobayashi3, Atsushi Oba1,4
1Division of Hepatobiliary and Pancreatic Surgery, Cancer Institute Hospital, Japanese Foundation for Cancer Research, Tokyo, Japan.

Background:
Robotic pancreatoduodenectomy demands precise orientation during uncinate/mesopancreatic dissection around the superior mesenteric artery (SMA)/vein (SMV) axis, where neural and lymphatic plexus dissection is technically and oncologically important.1,2In this deep field, small pancreatic head arterial branches and jejunal mesenteric arteries are useful landmarks but are difficult to recognize under the limited tactile feedback of robotic surgery.
Methods:
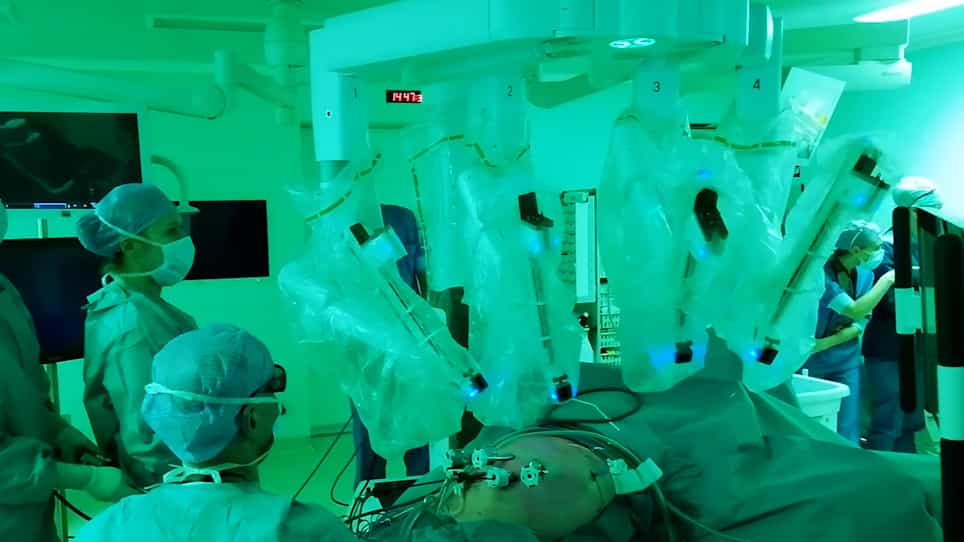
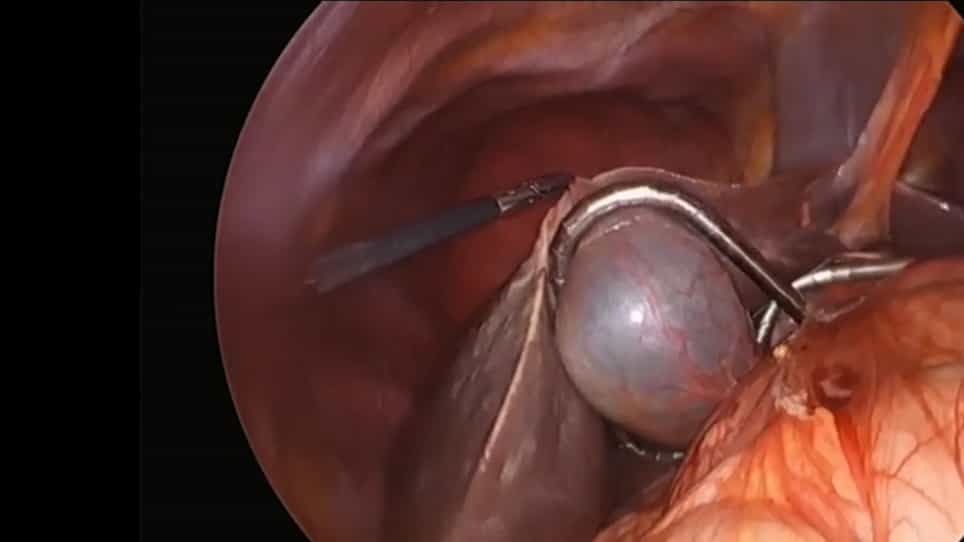
This video demonstrates indocyanine green (ICG) fluorescence-guided navigation at two demanding steps of robotic pancreatoduodenectomy using the da Vinci Xi Firefly system, with low-dose boluses (1.25-2.5 mg) followed by a rapid 10-20-mL saline flush.3 ICG was applied during uncinate/mesopancreatic dissection oriented to the peri-SMA nerve plexus (PL-phII) and during jejunal mobilization.4,5,6 RESULTS: In the presented case, ICG provided clear real-time confirmation of pancreatic head arterial landmarks-including the inferior pancreaticoduodenal artery (IPDA) and the dorsal pancreatic artery (DPA) right branch-in the deep uncinate and mesopancreatic field. The DPA right branch, running superficial to the PL-phII division plane, served as a representative orientation marker around the SMA/SMV axis.5,6 In the jejunal mesentery, fluorescence visualized the first and second jejunal arterial (J1A/J2A) branching, facilitating selection of the intended mesenteric division line.4 CONCLUSIONS: ICG fluorescence may offer useful real-time anatomical confirmation during these two demanding steps. It should be regarded as an adjunct to preoperative imaging and surgical anatomy, not as evidence of improved perioperative or oncologic outcomes.