Related Experiment Video
Updated: Sep 5, 2026
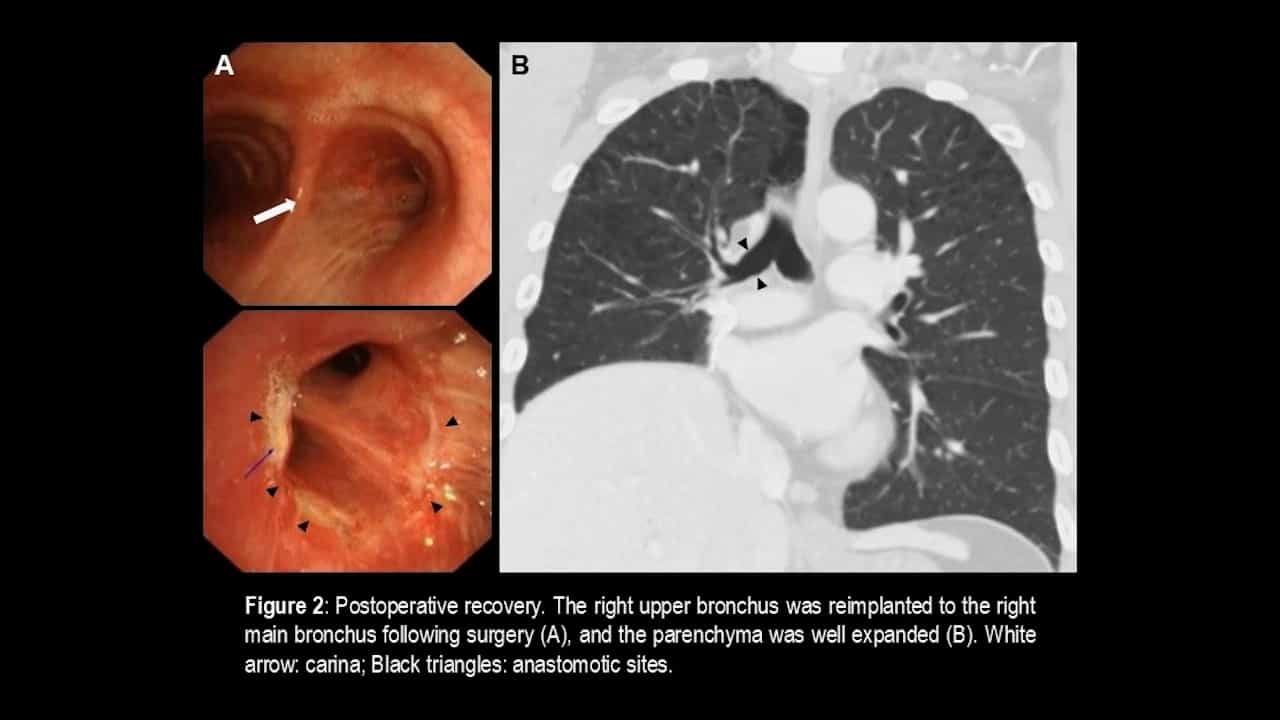

Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Subtyping limited stage small cell lung cancer (LS SCLC) reveals inflammatory subtypes with improved
Rafael Oliveira1, Tarje Halvorsen1, Kristin Killingberg1
1Department of Clinical and Molecular Medicine, Norwegian University of Science and Technology (NTNU), Trondheim, Norway; Department of Oncology, St. Olavs Hospital HF, Trondheim University Hospital, Trondheim, Norway.

Background:
Concurrent chemoradiotherapy (CRT) remains the primary treatment for limited stage (LS) small cell lung cancer (SCLC). Although most patients respond, the majority relapse and die from the disease, and treatment-related toxicity is common. Molecular subtyping has been extensively investigated in SCLC, but its clinical relevance remains uncertain, and most studies have focused on systemic treatment of extensive-stage SCLC. We analysed baseline tumor samples from a subset of participants (n = 77) in a randomized trial (n = 170) comparing high-dose (60 Gy/40 fractions) with standard-dose (45 Gy/30 fractions) twice-daily thoracic radiotherapy given concurrently with platinum-etoposide chemotherapy for LS SCLC, aiming to characterize molecular subtypes of LS SCLC and evaluate their association with time to progression (TTP) and overall survival (OS).
Methods:
Molecular subtypes were defined in 81 samples using non-negative matrix factorization on gene expression data, supported by differential expression and known SCLC markers.
Results:
Inflamed subtypes were associated with better treatment outcomes. Univariable analysis indicate that SCLC-I-NE (inflamed neuroendocrine) was associated with longer TTP (HR 0.10, 95 % CI 0.01-0.80, p = 0.03), and SCLC-I-nNE (inflamed non-neuroendocrine) was associated with improved OS (HR 0.16, 95 % CI 0.03-0.77, p = 0.02). By contrast, SCLC-N (NEUROD1-driven) was consistently associated with both shorter TTP (HR 6.90, 95 % CI 1.49-31.92, p = 0.01) and OS (HR 4.89, 95 % CI 1.24-19.21, p = 0.02).
Conclusions:
For LS SCLC patients receiving CRT, tumors of inflamed subtypes were associated with improved outcomes, whereas SCLC-N tumors were linked to unfavorable TTP and OS.
