Related Experiment Videos
Early laboratory trajectories and short-term tolerability after finerenone initiationin diabetic kidney disease: the
Serap Yadigar1, Suat Akgür2, Felemez Arslan3
1Department of Nephrology, Doktor Lütfi Kırdar City Hospital, Hamidiye International School of Medicine, University of Health Sciences, D-100 Güney Yanyol No: 47 Cevizli Mevkii, Kartal, Istanbul, 34865, Türkiye. serapsert2000@yahoo.com.

Background:
Real-world evidence describing the early laboratory course after finerenone initiation in contemporary nephrology practice remains limited, particularly in cohorts with high background use of sodium-glucose co transporter 2 inhibitors (SGLT2i). We evaluated early kidney-function, potassium, and albuminuria trajectories and short-term treatment tolerability.
Methods:
FINE-TURK was a multicenter retrospective cohort study without a comparator group. Adults with diabetes and chronic kidney disease who initiated finerenone in routine care were evaluated at baseline and using the first available values recorded in the 1-3-month follow-up fields. Primary outcomes were within-patient changes in estimated glomerular filtration rate (eGFR), serum potassium, and urinary albumin-to-creatinine ratio (UACR). Complete and incomplete follow-up groups were compared, UACR responder analyses were performed, and exploratory multivariable and subgroup models were fitted.
Results:
The analytic cohort contained 1,091 patients (mean age 60.6 ± 11.5 years; 55.0% male), and documented SGLT2i use was 87.0% among 1,075 patients with available data. Paired data were available for eGFR in 571 patients (52.3%), potassium in 647 (59.3%), and UACR in 476 (43.6%). Median eGFR changed from 53.5 [41.0-74.5] to 51.0 [38.0-73.0] mL/min/1.73m² (median change -2.0 [-6.0 to 1.0]; P<0.001). Median potassium changed from 4.50 [4.20-4.80] to 4.80 [4.50-5.10] mEq/L (mean change +0.30 ± 0.46; P<0.001). Median UACR changed from 777.8 [327.2-1539.5] to 461.2 [154.7-1040.0] mg/g; 297/476 (62.4%, 95% CI 58.0-66.6) achieved a ≥30% reduction and 184/476 (38.7%, 95% CI 34.4-43.1) achieved a ≥50% reduction. A recorded follow-up potassium >5.5 mEq/L occurred in 27/653 (4.1%), >6.0 mEq/L in 5/653 (0.8%), and finerenone discontinuation in 39/1,091 (3.6%).
Conclusions:
Early laboratory changes and treatment persistence after finerenone initiation were describable in routine specialist care, but incomplete outcome ascertainment and the absence of a comparator group preclude causal or comparative-effectiveness conclusions. The albuminuria findings apply only to patients with paired measurements and remain vulnerable to selection bias and regression to the mean.
Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:25
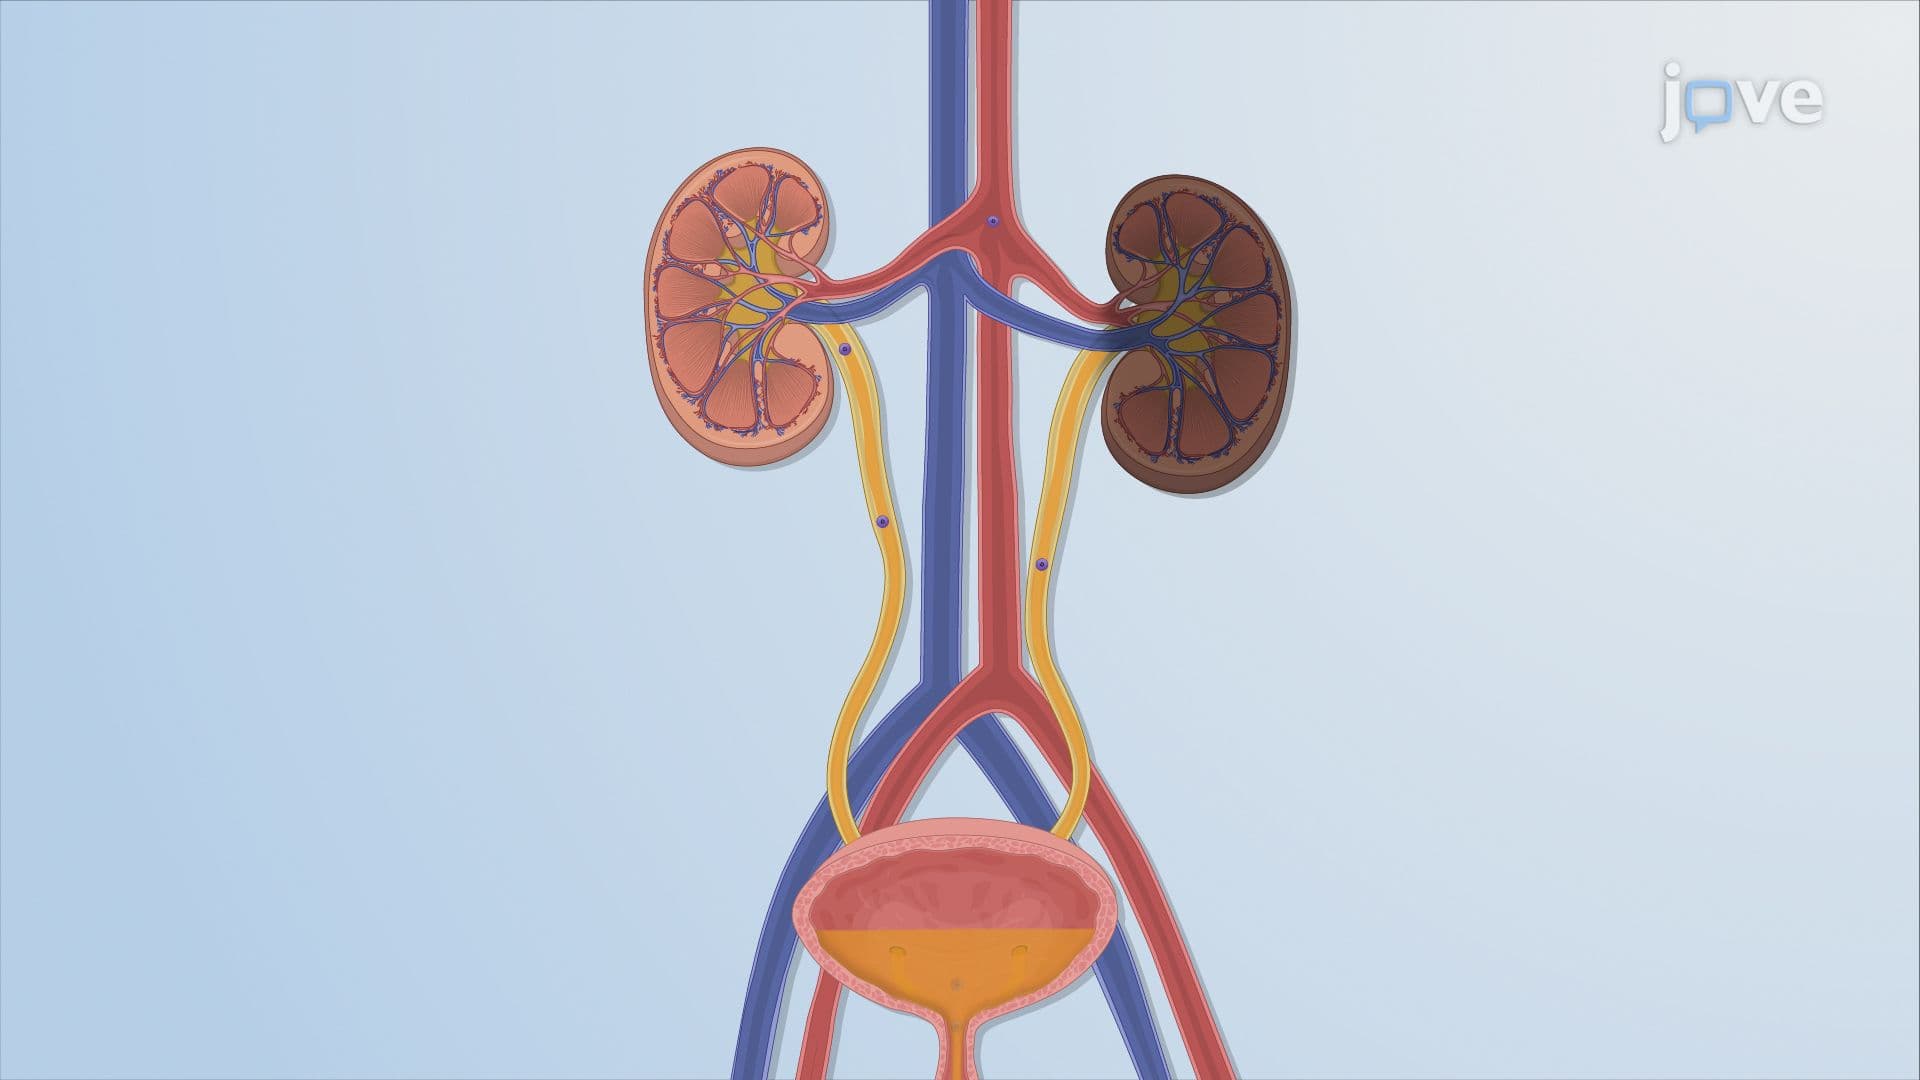
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Kidney Transplant I: Introduction
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration