Related Experiment Video For Hashimoto’s thyroiditis
Updated: Sep 5, 2026
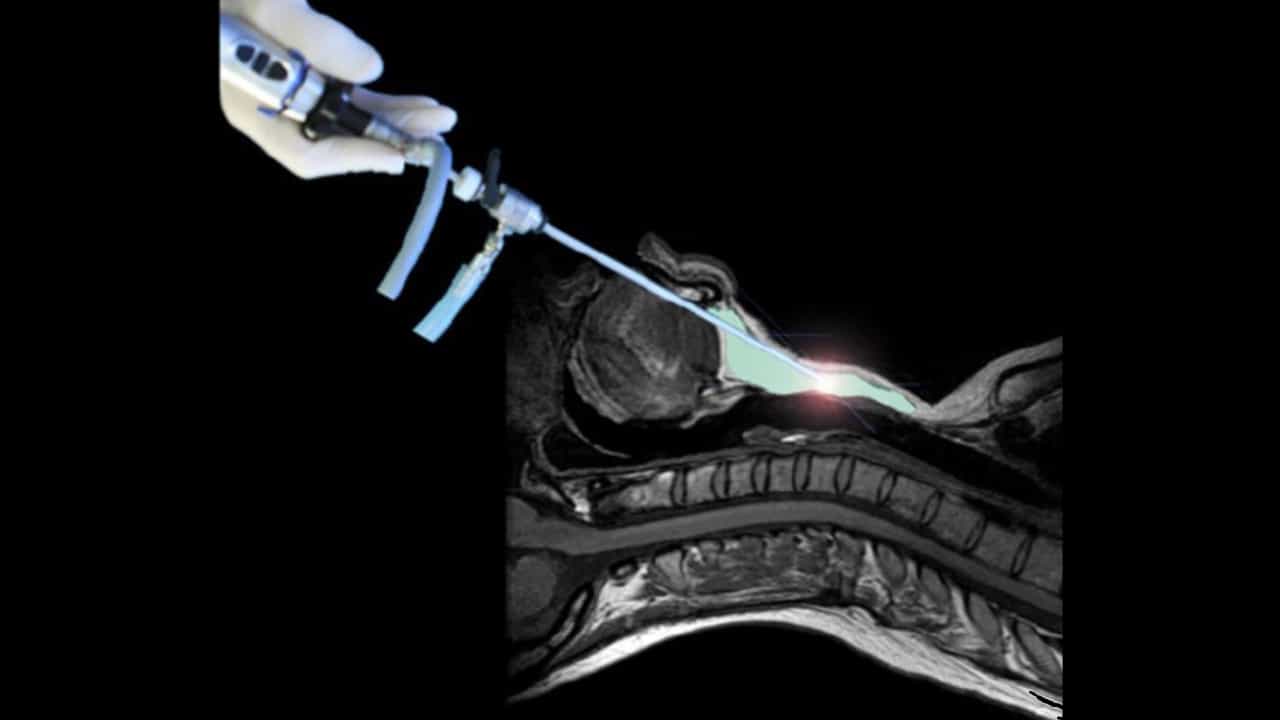

Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Coexistent Hashimoto's thyroiditis modulates lymph node metastasis burden in papillary thyroid carcinoma: a
Tianyu Gan1, Dongyuan Gan2, Guansheng Liao1
1Department of Thyroid Surgery, Huizhou Central People's Hospital, Huizhou, China.

Objective:
To investigate the impact of Hashimoto's thyroiditis (HT) on central lymph node metastasis (CLNM) patterns and identify independent risk factors for CLNM in patients with papillary thyroid carcinoma (PTC).
Methods:
This retrospective study enrolled 668 cN0 PTC patients who underwent initial surgery at Huizhou Central People's Hospital between August 2024 and July 2025. Patients were stratified into an HT-PTC group (n = 117) and a PTC-only group (n = 551) based on postoperative histopathological findings. Clinicopathological features and CLNM characteristics were systematically compared. Multivariable logistic regression was utilized to identify independent risk factors for CLNM in patients with HT-PTC, and the predictive efficacy of the resulting model was validated using ROC curves.
Results:
The HT-PTC group exhibited significantly higher rates of multifocality and central lymph node dissection, alongside lower BMI and serum thyroglobulin (Tg) levels, compared with the PTC-only group (all P < 0.05). While the incidence of CLNM did not differ significantly between groups (35.0% vs. 33.9%, P = 0.819), the metastatic lymph node ratio (LNR) was significantly lower in the HT-PTC group (P < 0.001). Multivariate analysis identified tumor diameter > 1 cm as an independent risk factor for CLNM among HT-PTC patients (OR = 3.678; 95% CI: 1.587-8.520, P = 0.002). The predictive model demonstrated moderate efficacy (AUC = 0.649). Notably, the incidence of CLNM in HT-PTC patients with microcarcinoma (≤ 1 cm) was only 25.9%.
Conclusion:
Concomitant HT is associated with a reduced metastatic burden rather than an increased prevalence of CLNM in patients with PTC. Tumor diameter > 1 cm serves as an independent predictor of CLNM. For HT-PTC patients with tumors ≤ 1 cm and no other high-risk factors, the necessity of prophylactic central lymph node dissection warrants individualized assessment combining clinical data and intraoperative observations to avoid overtreatment.
