Related Experiment Video
Updated: Sep 6, 2026
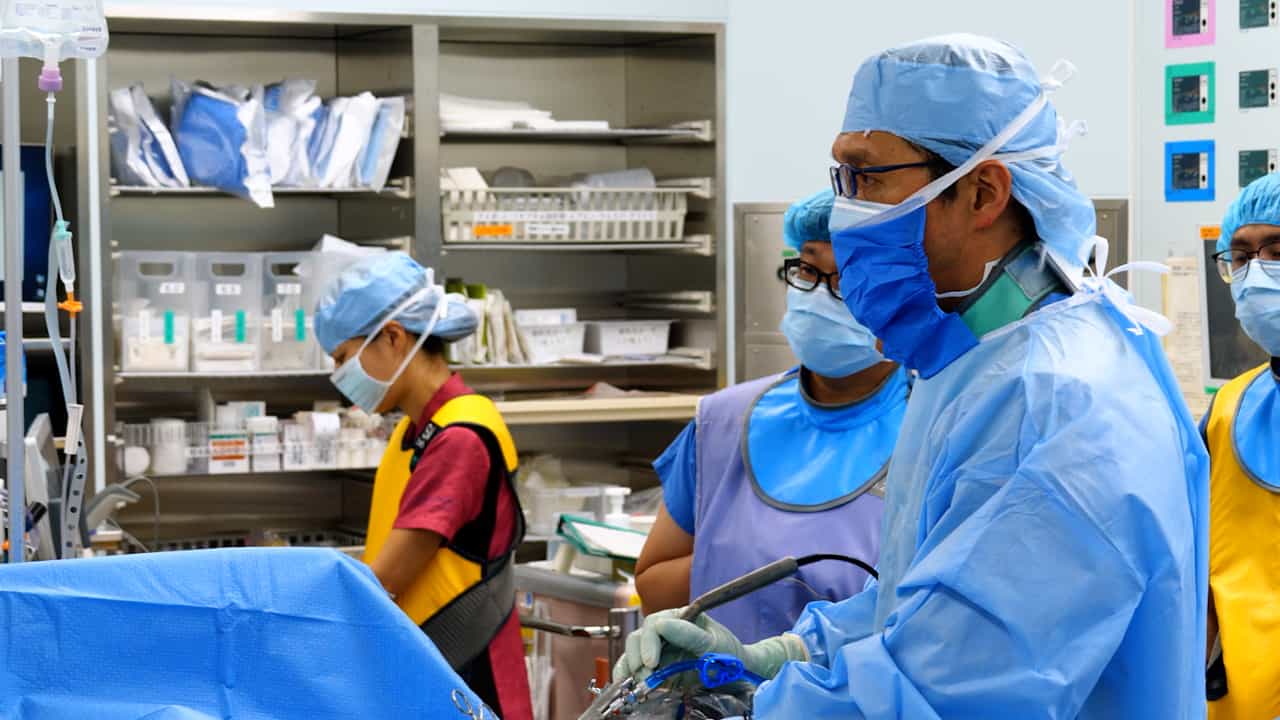

Transforaminal Full-Endoscopic Lumbar Foraminotomy Under Local Anesthesia for L5/S1 Adjacent Segment Foraminal Stenosis
Published on: October 17, 2025
Implications of asymptomatic radiographic foraminal stenosis: outcomes after single-level minimally invasive
Tejas Subramanian1,2, Stephane Owusu-Sarpong1, Atahan Durbas1
11Department of Spine Surgery, Hospital for Special Surgery, New York.

Objective:
Foraminal stenosis (FS) is commonly identified in patients undergoing lumbar decompression, but its clinical significance when deemed "asymptomatic" remains unclear. Minimally invasive surgery techniques for decompression, including unilateral laminotomy for bilateral decompression, aim to relieve neural compression while preserving soft tissue. However, the impact of preoperative FS on postoperative outcomes following minimally invasive decompression is not well-established. The aim of this study was to evaluate the effect of preoperative FS on patient-reported outcome measures (PROMs) and revision surgery rates following single-level minimally invasive lumbar decompression.
Methods:
Patients who underwent primary single-level minimally invasive decompression for degenerative lumbar conditions between February 2017 and September 2022 at a single institution were included. Preoperative FS severity was graded from 0 (none) to 3 (severe) on MRI, and patients were stratified into FS+ (any FS ≥ grade 1) and FS- (no FS) groups. Patients in the FS+ and FS- groups were matched 1:1 based on demographic characteristics and preoperative radiographic parameters and compared for all outcome measures. Outcomes included PROMs (Oswestry Disability Index [ODI], visual analog scale [VAS] for back and leg pain, and SF-12 Physical Component Score [PCS]) at short-term and long-term follow-up time points and revision surgery rates. Multivariable logistic regression analysis was conducted for predictors of nonachievement of the minimal clinically important difference (MCID) and patient acceptable symptom state (PASS).
Results:
Of 320 patients included in the analysis, FS was present in 234 (73.1%, mean age 68.52 years). After matching, the FS+ group (n = 71) and FS- group (n = 71) were compared. Both groups demonstrated significant postoperative improvement in PROMs; however, patients with FS had worse ODI (p = 0.001), VAS-back (p = 0.003), and SF-12 PCS (p = 0.004) outcomes at long-term follow-up. In addition, the FS+ group had higher revision surgery rates at the index level (p = 0.003) and greater likelihood of requiring fusion (p = 0.005). An FS grade of 2 or 3 independently predicted failure to achieve the MCID for ODI, VAS Back, SF-12 PCS and the PASS for ODI.
Conclusions:
Radiographic FS, even when deemed asymptomatic, was associated with worse long-term functional outcomes and higher revision rates following minimally invasive decompression. These findings underscore the need for careful preoperative assessment and surgical planning, particularly for patients with moderate-to-severe FS, to optimize long-term outcomes.