Related Experiment Video
Updated: Sep 7, 2026
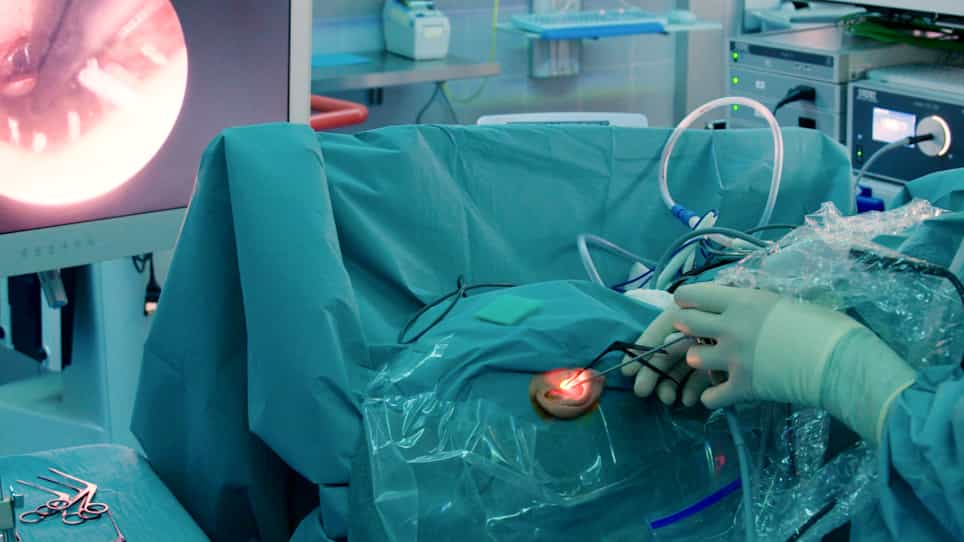

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
External auditory canal cholesteatoma presenting with facial nerve palsy: rare clinical entity
Rim Marouf1, Walid Bijou1, Youssef Oukessou1
1Department of Otolaryngology, Head and Neck Surgery, Ibn Rochd University Hospital, Faculty of Medicine and Pharmacy, Hassan II University, Casablanca, Morocco.

Introduction And Importance:
External auditory canal cholesteatoma (EACC) is a rare, non-neoplastic lesion representing 0.1%-0.5% of otologic cases. Despite its rarity, EACC can be highly destructive, similar to middle ear cholesteatoma. Owing to its proximity to vital structures such as the facial nerve, severe complications, including facial paralysis, may occur, although such presentations remain exceptionally uncommon and scarcely reported.
Case Presentation:
We report the case of a 45-year-old male patient who presented to our ENT department with right-sided facial paralysis. Otoscopic examination revealed cholesteatoma debris filling the right external auditory canal (EAC), with posterior and inferior canal wall erosion but an intact tympanic membrane. CT imaging demonstrated EAC erosion extending to the vertical segment of the facial nerve, while the tympano-mastoid cavity remained intact. Surgical exploration confirmed an extensive EACC with complete destruction of the posterior wall and erosion of the inferior wall, surrounding the exposed vertical segment of the facial nerve. Complete removal of the cholesteatoma was achieved via canal-wall-down mastoidectomy, followed by facial nerve decompression and canaloplasty.
Clinical Discussion:
EACC is a rare lesion of keratinizing epithelium confined to the bony canal, typically presenting with chronic otorrhea and dull otalgia. The diagnosis is primarily clinical, supported by high-resolution CT to assess bone erosion and disease extent. EACC is classified into three stages: stage 1, limited to the canal; stage 2, with bone erosion and/or middle ear involvement; and stage 3, extending to adjacent structures, with or without complications such as facial paralysis. EACC may be primary or secondary to factors such as surgery or radiotherapy. Management ranges from conservative debridement to surgical intervention, including canaloplasty or mastoidectomy, depending on the extent of disease.
Conclusion:
Facial paralysis (FP) is a rare complication of EACC, occurring in fewer than 1% of cases. Early surgical removal, ideally within 1 month of FP onset, significantly improves facial nerve recovery. Clinicians should consider EACC in patients with suspicious otoscopic findings or chronic otorrhea unresponsive to medical treatment.
Related Concept Videos
 01:22
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:03
Olfactory Receptors: Location and Structure
 01:16
Anatomy of the Ear
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:27
Esophageal Achalasia