Related Experiment Video
Updated: Sep 7, 2026
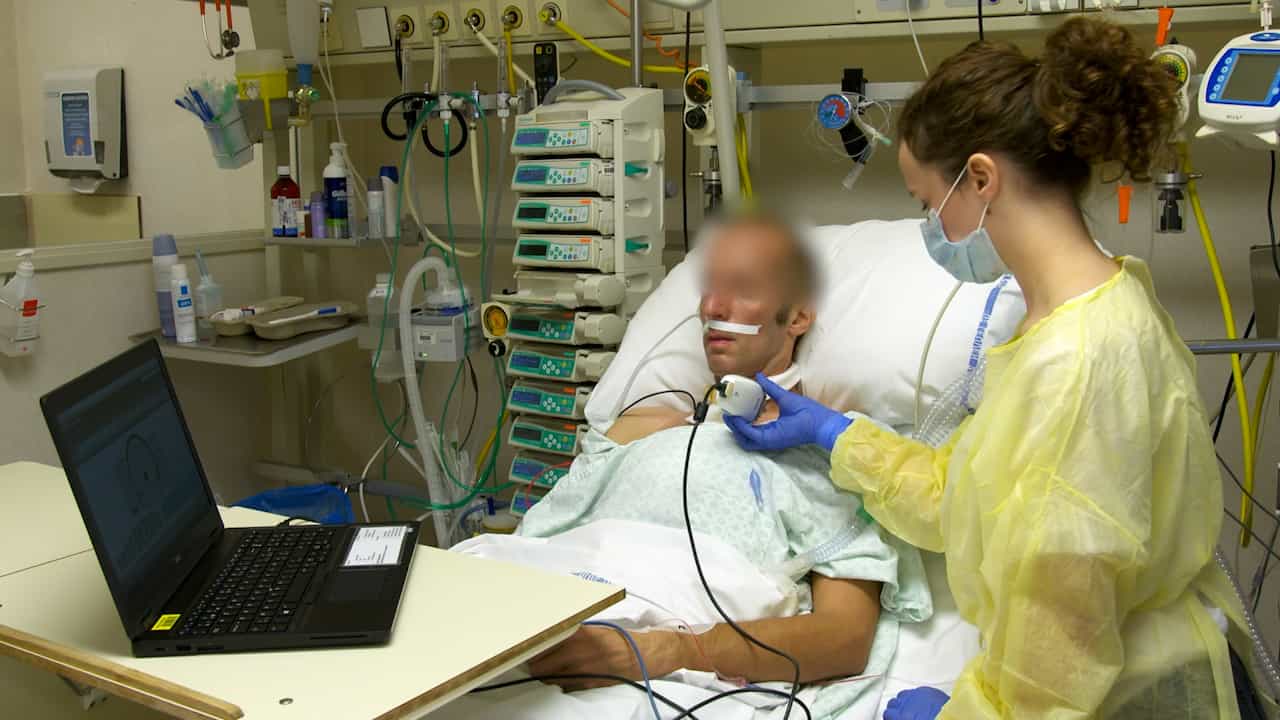

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Midaxillary-to-midclavicular diaphragmatic mobility ratio predicts weaning success in invasive mechanical
Lanyan Huang1, Liqun Chen1, Yuanlve Chen1
1Department of Critical Care Medicine, Zhangzhou Affiliated Hospital of Fujian Medical University, Zhangzhou, China.

Background:
A high proportion of patients undergoing invasive mechanical ventilation (IMV) experience weaning failure. As the primary respiratory muscle, the diaphragm rapidly atrophies under the influence of IMV, analgesics/sedatives/muscle relaxants, and nutritional depletion. The accurate assessment of diaphragmatic function is critical for predicting weaning success. Previous studies have primarily focused on diaphragmatic mobility (DM) and diaphragmatic thickening fraction (DTF), both limited by substantial inter-individual variability and regional contractile heterogeneity. This study introduces a novel parameter-the ratio of DM measured at the midaxillary line (MAL; reflecting domed portion mobility) to that at the midclavicular line (MCL; reflecting posterior wall mobility)-as a predictor of weaning outcomes, and evaluates its statistical discriminative ability.
Methods:
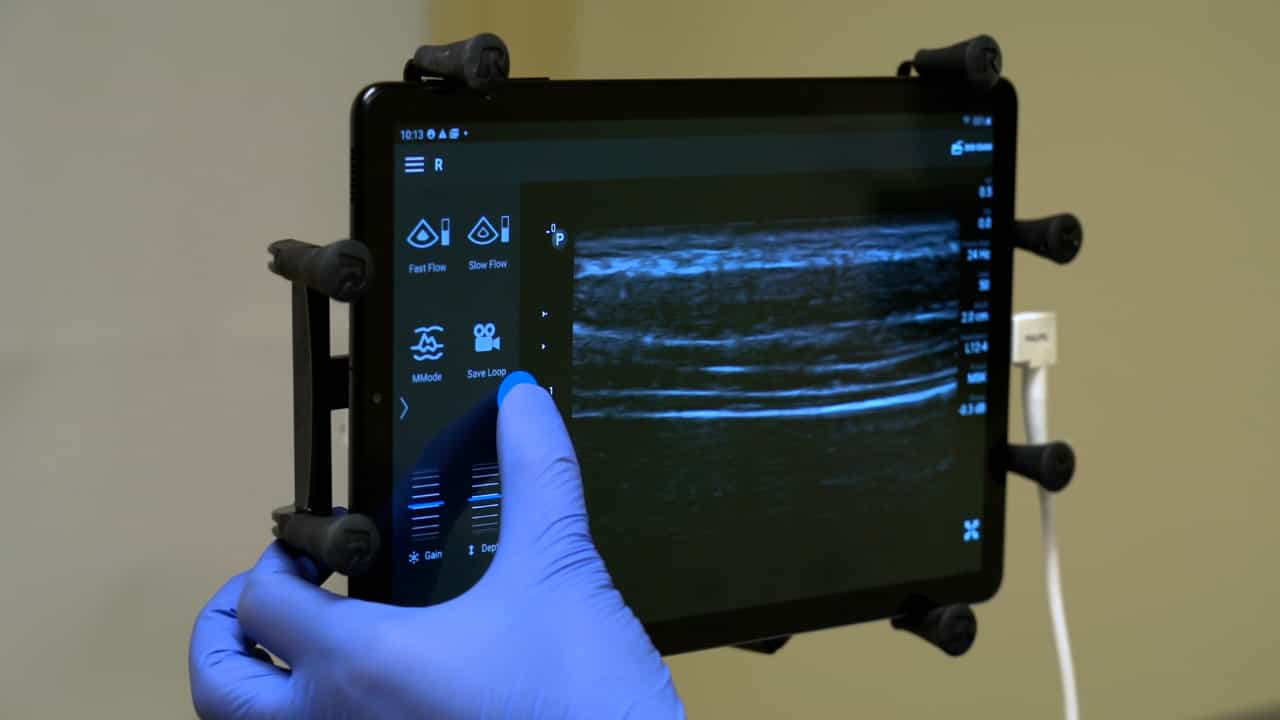
This observational cohort study enrolled patients receiving IMV for >72 hours in the intensive care unit (ICU) of our hospital between 18 September 2025 and 10 April 2026. Patients were divided into success and failure groups based on the outcome of the first weaning attempt. Clinical data including sex, age, Acute Physiology and Chronic Health Evaluation version II (APACHE II) score, and primary etiology for IMV were collected. Bedside ultrasound measurements of MAL, MCL, and the MAL/MCL ratio were performed at 24 and 72 hours after ICU admission, and during spontaneous breathing trial (SBT) (awake state, minimal sedatives/analgesics). Serum potassium (K+), prealbumin (Pa), partial pressure of oxygen/fraction of inspired oxygen (PaO2/FiO2), and left ventricular ejection fraction (LVEF) were also recorded. The study involved only diagnostic data and routine samples, with no interventional procedures.
Results:
(I) No significant differences were observed between groups in age or APACHE II score. (II) At 24 hours and during SBT, Pa, MAL, MCL, LVEF, and K+ showed no intergroup differences, whereas the MAL/MCL ratio differed significantly. (III) At 72 hours, none of the parameters, including MAL/MCL, showed significant intergroup differences. (IV) During SBT, the area under the curve (AUC) of MAL/MCL was 0.945, with a cutoff value >1.11 yielding a specificity of 94.44%.
Conclusions:
As a novel diaphragmatic ultrasound parameter, the MAL/MCL ratio, which mitigates inter-individual baseline variability, demonstrated excellent discriminative performance in this single-center cohort. Clinicians may consider incorporating MAL and MCL measurements with ratio calculation during weaning assessment. However, calibration analysis indicated that its clinical utility lies primarily in identifying patients at high risk of weaning failure rather than providing precise individual risk probabilities. These findings warrant validation in larger, multicenter studies before routine clinical adoption.
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:10
Atelectasis II: Pathophysiology