Related Experiment Video
Updated: Sep 8, 2026
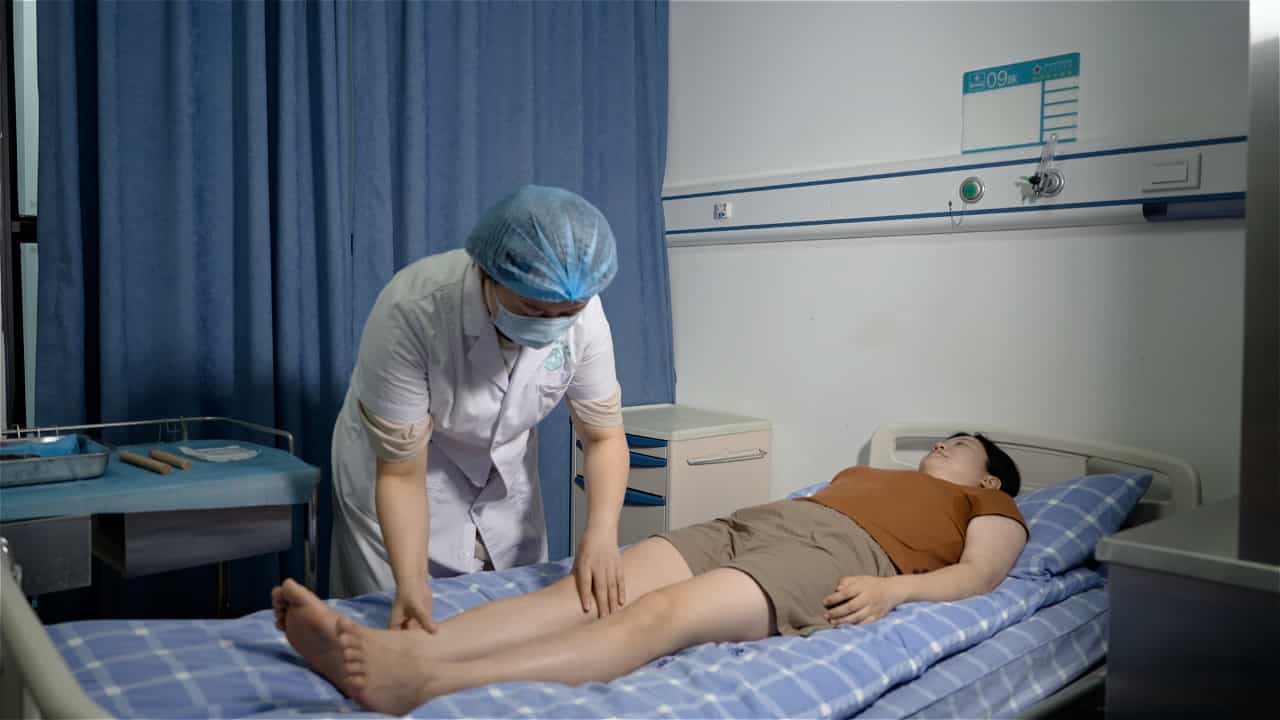

A Traditional Chinese Medicine Characteristic Therapy for Bronchial Asthma: Moxibustion
Published on: May 12, 2023
Pharmacokinetic and Pharmacodynamic Interactions Between Anti-Asthma Drugs and Medicinal Plants: A Comprehensive
Emine Kocyigit1, Aylin Bülbül1, Betul Kocaadam-Bozkurt2
1Department of Nutrition and Dietetics, Ordu University, Ordu, Türkiye.

Abstract:
Asthma affects 260-300 million people worldwide. About 20%-35% of patients use medicinal plants with their asthma medication, often without telling their clinicians. Disclosure rates are low; up to 42% of asthma outpatients use herbal products, with no records in their charts. Previous reviews discussed herb-drug interactions and asthma phytotherapy separately. There is no combined pharmacokinetic, pharmacodynamic, and toxicological evidence for all modern anti-asthma agents. This review closes that gap. It draws from mechanistic, preclinical, and clinical data. It looks at eight common botanicals: Glycyrrhiza glabra, Curcuma longa, Nigella sativa, Boswellia serrata, Tylophora indica, Adhatoda vasica, Astragalus membranaceus, and Piper nigrum. The review explains how these botanicals affect cytochrome P450 isoenzymes, Phase II conjugative enzymes, and membrane transporters, including P-glycoprotein. It also considers shared adrenergic, glucocorticoid-receptor, and inflammatory targets of inhaled corticosteroids, β2-agonists, leukotriene receptor antagonists, theophylline, and biologic agents. These interactions create clinical hazards. For example, Hypericum perforatum increases CYP3A4 activity by up to 11-fold and can destabilize theophylline and corticosteroid levels. Ephedra sinica causes dose-dependent sympathomimetic toxicity, which worsens β2-agonist cardiovascular risk. Glycyrrhiza glabra may trigger pseudoaldosteronism and hypokalaemia by inhibiting 11β-hydroxysteroid dehydrogenase type 2. Ginkgo biloba has been tied to bleeding events. Turmeric, previously seen as safe, now appears in drug-induced liver injury registries. Compositional variability adds to the risk; for example, hyperforin content can range from 0.01% to 1.89%, and ephedrine content varies by more than 12-fold across products. This review places its findings in the context of the WHO Global Traditional Medicine Strategy 2025-2034. It identifies important herb-anti-asthma drug pairs, defines monitoring endpoints, and proposes a pharmacogenetically informed framework for safely integrating medicinal plants into asthma care.
Related Concept Videos
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:20
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes: