Related Experiment Video
Updated: Sep 9, 2026
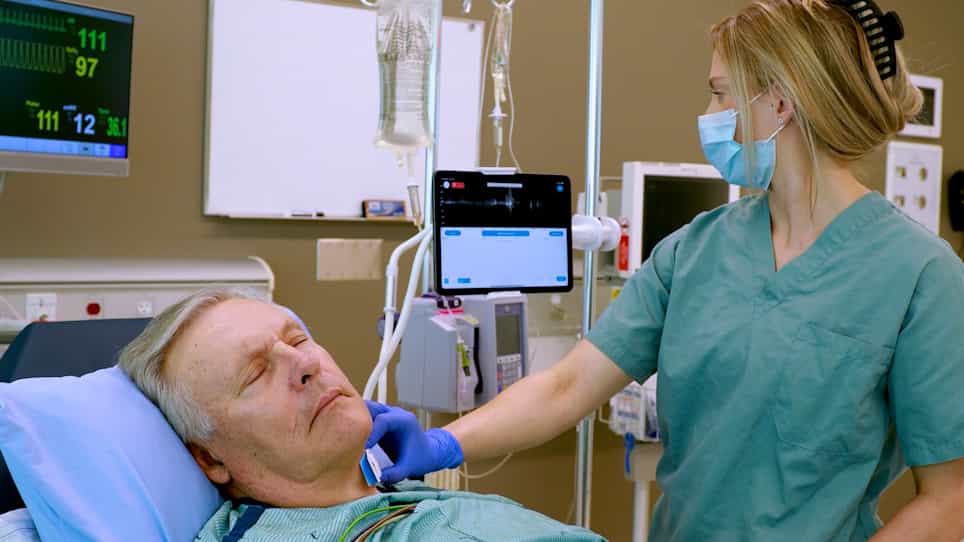
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Venous dimension of shock: Integrating arterial inflow and venous back-pressure in hemodynamic assessment
Sahil Kataria1, Saketh Vinjamuri2, Deven Juneja3
1Department of Critical Care Medicine, Holy Family Hospital, New Delhi 110025, Delhi, India.

Abstract:
Critical care hemodynamics has long been centered on arterial pressure, cardiac output, and systemic vascular resistance. While these variables remain fundamental, organ perfusion is determined not only by arterial inflow but also by the pressure opposing venous outflow at the microcirculatory level. Emerging clinical and physiological evidence indicates that elevated venous pressure may contribute to organ dysfunction even when arterial pressure appears adequate. Effective organ perfusion reflects the balance between arterial driving pressure and venous outflow pressure, further modified by microcirculatory factors such as capillary density, flow heterogeneity, and cellular oxygen utilization, which are usually inferred at the bedside rather than directly measured. Consequently, abnormal tissue perfusion may arise from reduced arterial inflow, elevated venous pressure, microcirculatory dysfunction, or a combination of these mechanisms. In this narrative review, we present the arterial-venous perfusion gradient as a pragmatic clinical synthesis that reintegrates established venous physiology into bedside hemodynamic interpretation. The review examines the physiological determinants of venous return, the consequences of venous congestion for organ function, and the clinical conditions in which elevated venous pressure contributes to organ injury. Particular attention is given to the effects of venous congestion on renal, hepatic, splanchnic, cerebral, and right-heart function, alongside bedside tools for evaluating venous hemodynamics, including point-of-care ultrasound, venous Doppler assessment, and ultrasound-based congestion scoring. We also propose a phenotype-based bedside approach for integrating arterial pressure, forward flow, venous congestion, and tissue perfusion during shock assessment and management. Recognizing discordant hemodynamic states may help clinicians identify patients whose organ dysfunction stems from elevated venous back-pressure or persistent microcirculatory impairment, rather than from impaired arterial inflow alone.


Related Concept Videos
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system as it...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:10
Veins as Blood Reservoirs
 01:24
Blood Pressure