Related Experiment Video
Updated: Sep 9, 2026


Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Galactocele Rupture Causing Milk Contamination of a Prepectoral Implant Pocket: Diagnostic Pitfall and Implant
1From the Division of Plastic and Reconstructive Surgery, Department of General Surgery, Nakornping Hospital, Chiang Mai, Thailand.

Abstract:
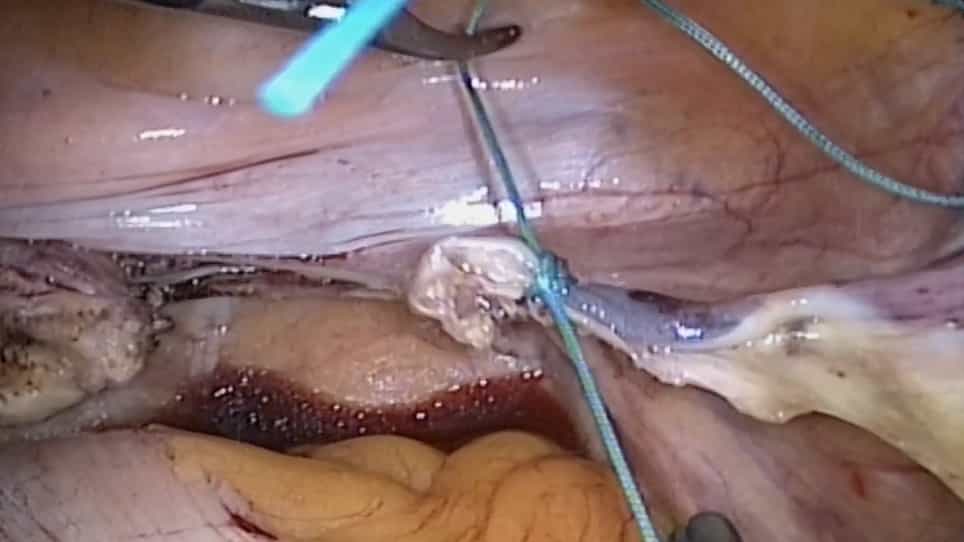
Galactocele is a benign milk retention cyst that may develop during or after lactation. In patients with breast implants, ruptured galactoceles can cause peri-implant fluid collections that mimic implant rupture or infection, creating a diagnostic challenge. This report describes a 37-year-old Asian woman, G1P1, with bilateral prepectoral smooth-surface silicone breast implants who presented 2 months postpartum with progressive left breast swelling that was initially diagnosed as mastitis. After noticing a palpable mass, the patient performed vigorous self-massage and increased breast pumping in an attempt to relieve presumed milk stasis, which precipitated acute breast enlargement. Despite antibiotic therapy, symptoms worsened, and evaluation by a radiologist and a general surgeon resulted in a diagnosis of implant rupture with infection and abscess; galactocele rupture was not considered. Surgical exploration revealed an intact implant with milk contamination of the implant pocket due to galactocele rupture and duct-capsule communication. No mature capsule was identified; the pocket was lined with granulation tissue. Fluid analysis demonstrated elevated triglyceride levels consistent with milk content, whereas bacterial cultures remained negative. Management included closure of the ductal communication, sequential antiseptic irrigation, drain placement, and lactation suppression with cabergoline. The implant was successfully salvaged, and the patient remained asymptomatic at 3-month follow-up without capsular contracture. Galactocele rupture should be considered in the differential diagnosis of peri-implant fluid collections in postpartum patients with breast implants. Vigorous manipulation over a palpable mass should be avoided, and timely lactation suppression is critical for implant salvage regardless of closure integrity.