Related Experiment Video
Updated: Sep 10, 2026
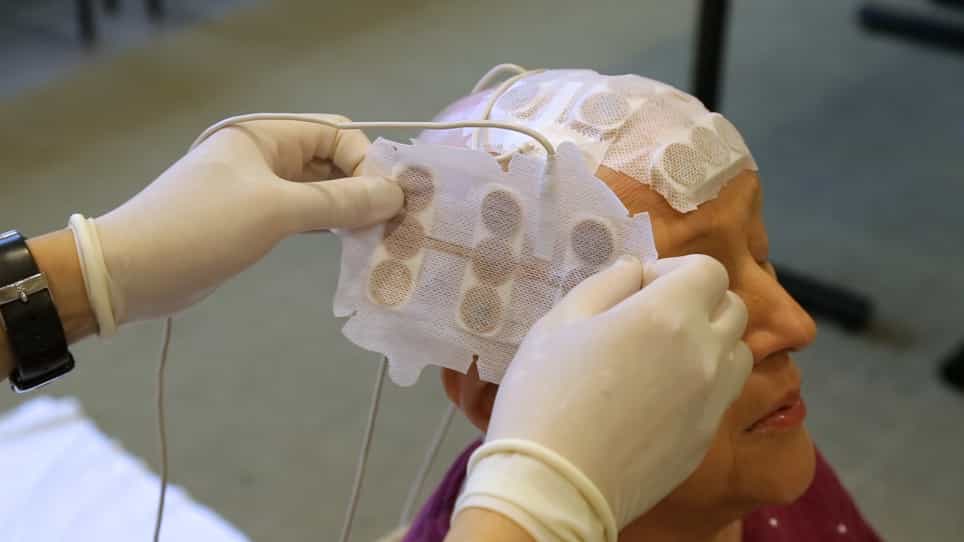

The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Treatment intensity and survival benefit among older adults with glioblastoma: A population-based analysis
Jianan Chen1, Qiong Wu1, Hannah M Cardenas2
1Department of Neuro-Oncology, H. Lee Moffitt Cancer Center and Research Institute, Tampa, FL, USA.

Background:
Older adults with glioblastoma (GBM) are frequently treated with de-escalated approaches. However, national trends in treatment intensity and the magnitude of absolute survival benefit across the older age spectrum remain unclear.
Methods:
We conducted a retrospective cohort study using the SEER database (2000-2020) including patients aged ≥65 years with GBM. Treatments were categorized as surgery (gross total resection [GTR], subtotal resection [STR], none), radiotherapy (RT), and chemotherapy (CT). Treatment intensity was defined by the number of modalities received (0-3); GTR-based trimodality therapy was defined as GTR combined with RT and CT. Temporal trends were assessed using logistic regression (odds ratio [OR] per year). Overall survival (OS) was evaluated using median OS and restricted mean survival time over 24 months (ΔRMST0-24), stratified by age group.
Results:
Among 21,206 patients, CT and GTR-based trimodality therapy increased annually (OR 1.09 and 1.03 per year, respectively). Triple-modality treatment intensity use declined sharply with age (54.3% in 65-69 vs. 8.3% in ≥85 years). Older age independently predicted lower odds of GTR-based trimodality therapy (adjusted OR 0.77 for 70-74, 0.53 for 75-79, 0.29 for 80-84, 0.09 for ≥85; all p < 0.001). Treatment intensity showed a dose-response association with survival. Compared with no treatment, GTR-based trimodality therapy conferred substantial absolute survival gains across all age strata, including ≥85 years (ΔRMST0-24 ranging from 11.1 to 8.2 months).
Conclusion:
In this SEER-based cohort, more intensive initial multimodality management was associated with greater survival time accrued within 24 months even at advanced age. Given unmeasured confounding and potential immortal time bias inherent to registry treatment classification, these findings support individualized consideration of multimodality therapy in appropriately selected older adults rather than reliance on chronological age alone.


