Related Experiment Videos
Finerenone-Based Dual Versus Triple Therapy with SGLT2 Inhibitors and GLP-1 Receptor Agonists in Type 2 Diabetes
Mohammed Khogalee1, Sami Mohamed2, Michael E Otim3
1Geriatrics and Internal Medicine Department, Queen Elizabeth The Queen Mother Hospital, East Kent Hospitals University, Margate, NHS Foundation Trust, United Kingdom.

Purpose:
Finerenone reduces Cardiovascular-Kidney-Metabolic (CKM) risk in type 2 diabetes mellitus (T2DM)-related chronic kidney disease (CKD). Evidence on its combined use with sodium-glucose cotransporter-2 inhibitors (SGLT2i) and glucagon-like peptide-1 receptor agonists (GLP-1 RA) in routine care remains limited. This study aimed to evaluate 6-month estimated glomerular filtration rate (eGFR), urinary albumin-to-creatinine ratio (UACR), and adverse outcomes among adults with T2DM-related CKD receiving finerenone + SGLT2i, with or without concomitant GLP-1RA.
Methods:
This retrospective cohort evaluated electronic medical records (EMR) from a UAE-based teaching hospital (November 2023 - January 2025). Adults with T2DM-related CKD receiving finerenone for ≥6 months were categorized at initiation into dual-therapy (Finerenone+SGLT2i), and triple-therapy (Finerenone+SGLT2i+GLP-1 RA), Patients receiving finerenone + GLP-1RA alone were excluded. Outcomes were 6-months eGFR, UACR and adverse events. Via Statistical Package for the Social Sciences (SPSS), means were analysed using paired t-tests, and between-group comparisons using adjusted analysis.
Findings:
Eighty-three patients were included after excluding 6 patients receiving finerenone + GLP-1RA only. Within-group ln(UACR) decreased in both regimens [dual-therapy (50.6%, 28.3-65.9; P < 0.001) and triple-therapy (46.9%, 27.0-61.3; P < 0.001)]. Mean 6-month eGFR changes were variable [dual-therapy (-6.12, -10.66 to -1.59; P = 0.010) and triple-therapy (-1.49, -5.19 to +2.21; P = 0.424)]. On adjusted analysis, triple-therapy was associated with higher 6-month eGFR compared with dual therapy (+6.407 mL/min/1.73 m²; 95% CI: +0.297 to +12.52; P = 0.040), whereas for ln(UACR) was not statistically significant (-0.323; 95% CI: -0.912 to +0.266; P = 0.277). Interpretation was limited by baseline imbalance and the retrospective observational design.
Implications:
Triple-therapy was associated with higher adjusted 6-month eGFR than dual-therapy, while UACR decreased without significant adjusted between-group differences. Findings were interpreted as associative rather than comparative superiority, given the observational design, baseline imbalance, and short follow-up. These results should be interpreted as hypothesis-generating associations, and future multicenter longitudinal studies with longer follow-up and assessment of medication continuation, and time-updated exposure are warranted.
Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Diabetic Nephropathy
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:02
Renal Drug Excretion: Glomerular Filtration
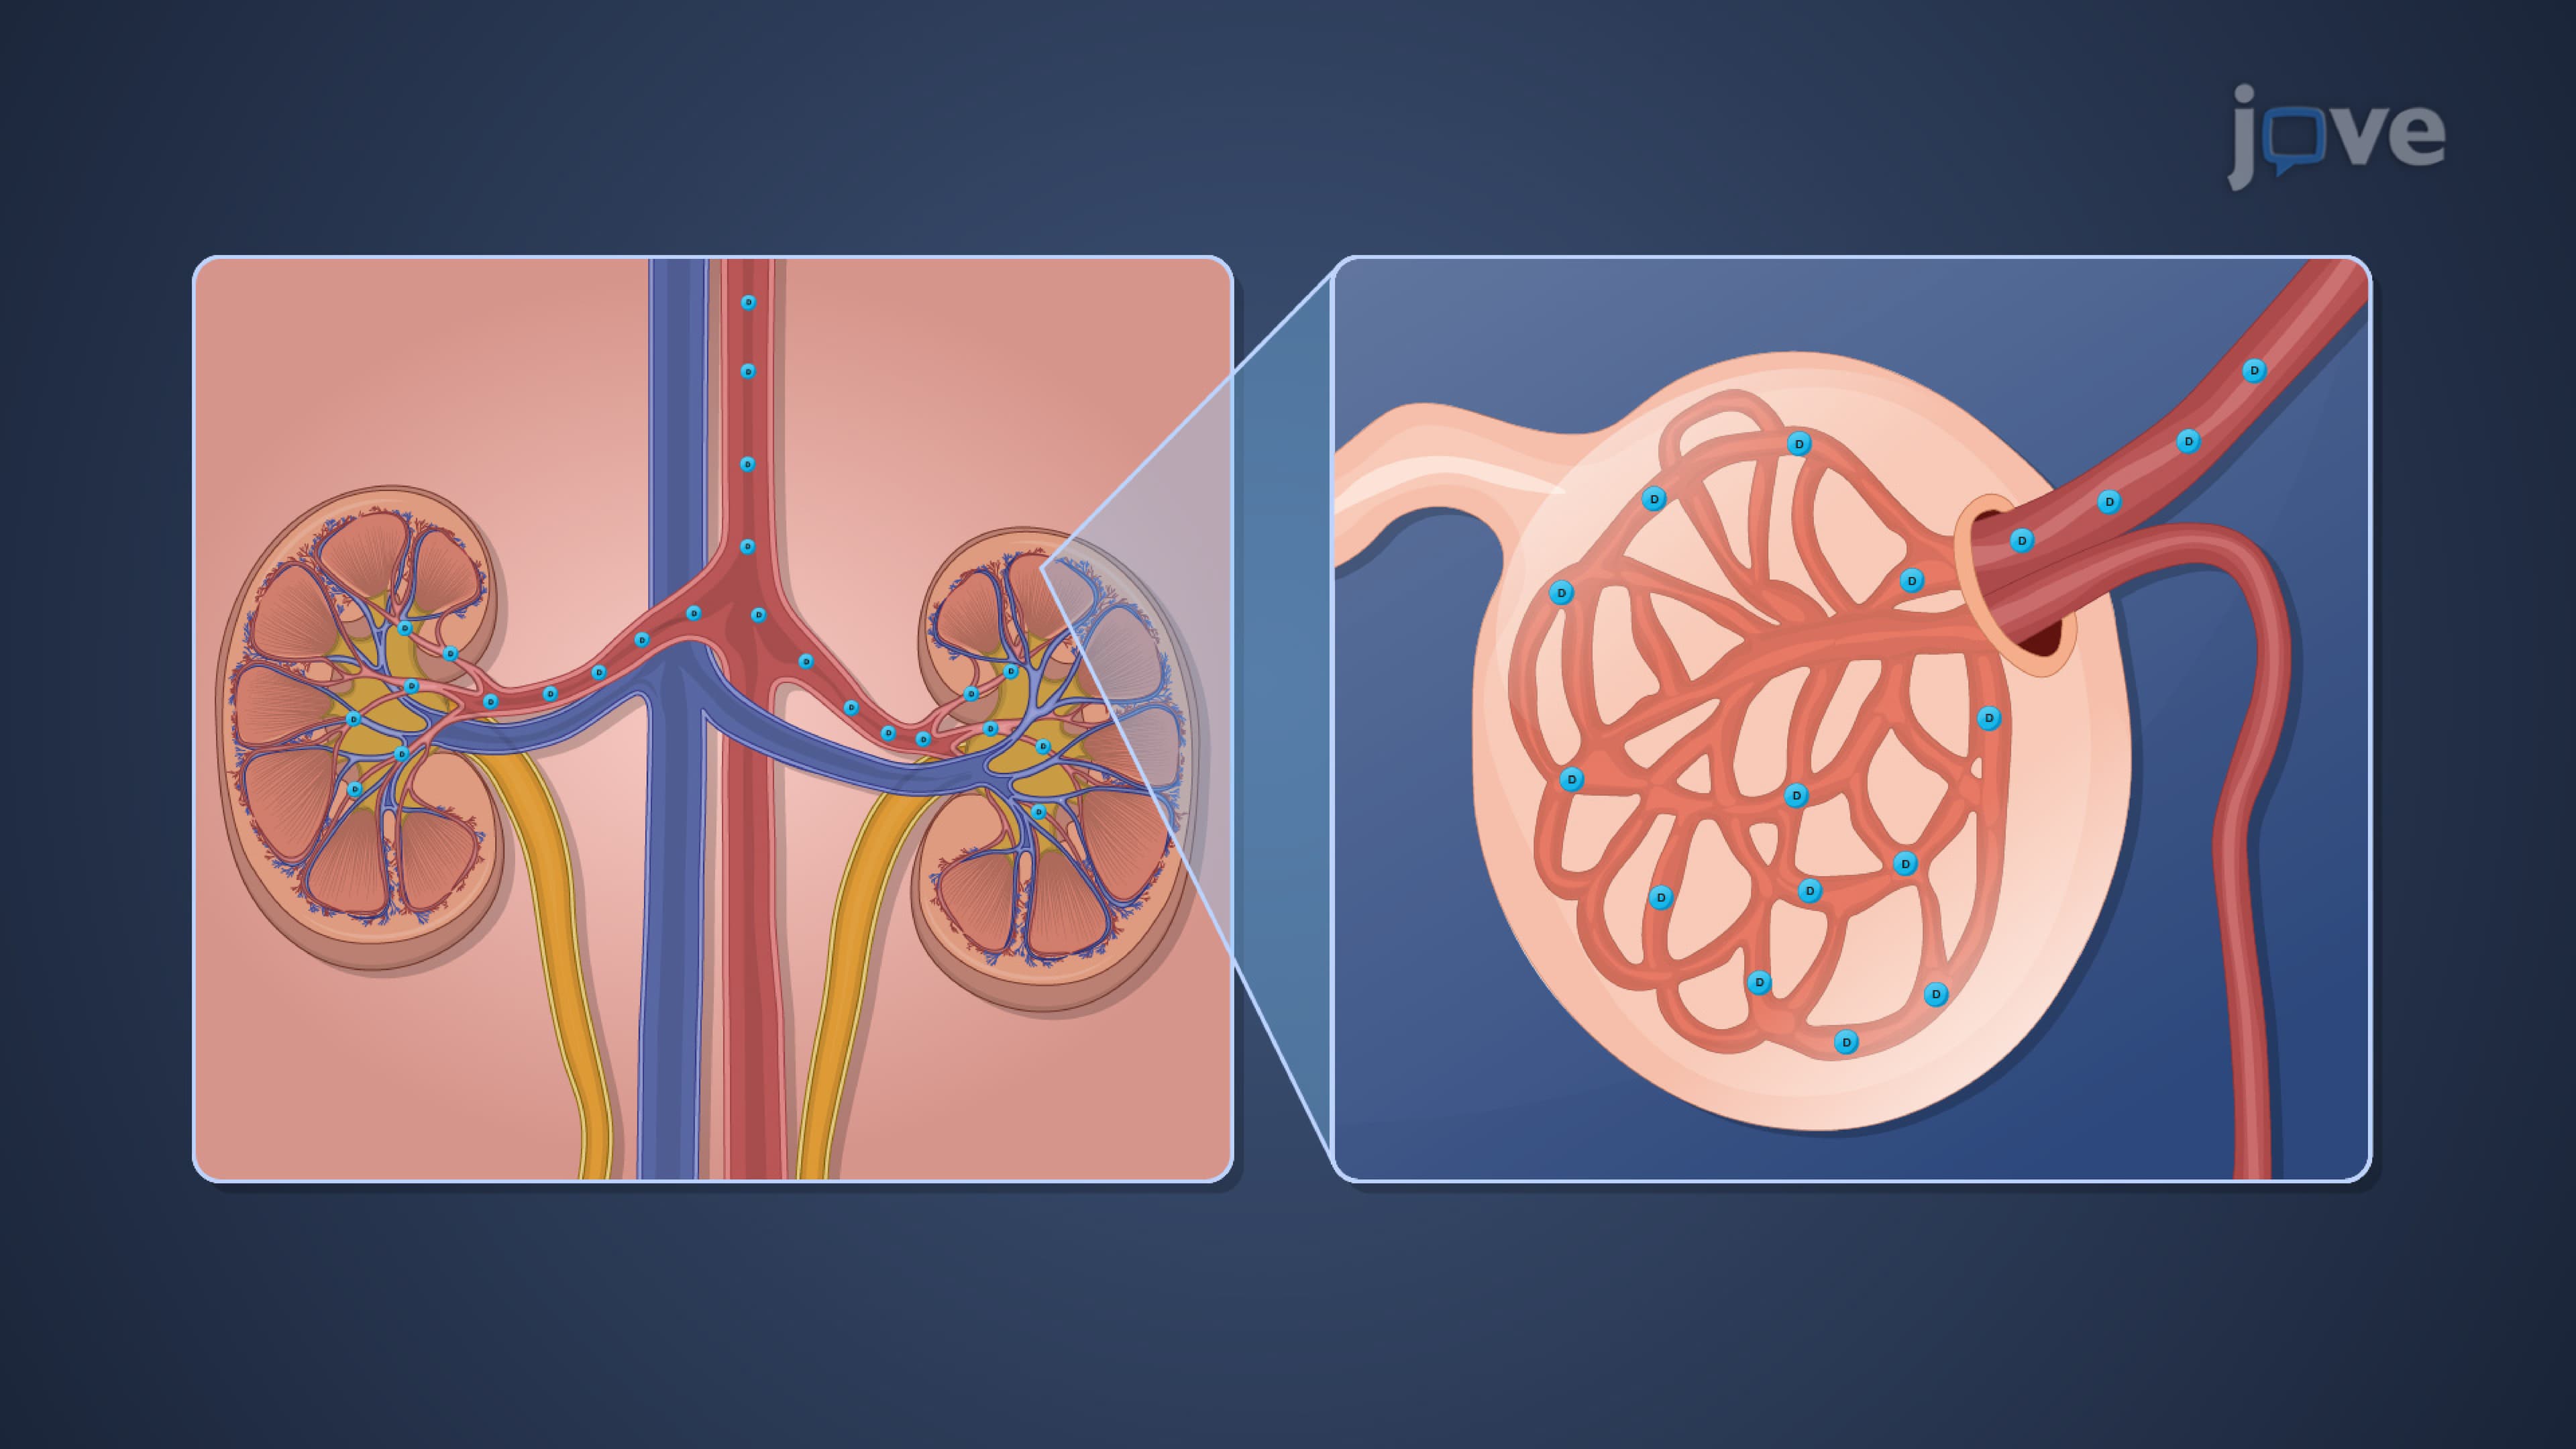
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles.