Related Experiment Videos
Acute Necrotizing Pancreatitis Presenting With Extensive Unilateral Lower Limb Myositis, Fasciitis, and Sterile
Vamsi K Uppati1, Anil K Abburi2, Lava K Pydi3
1Gastroenterology, Great Eastern Medical School and Hospital, Srikakulam, IND.

Abstract:
Musculoskeletal manifestations of acute pancreatitis are uncommon and are most frequently described as pancreatic panniculitis or pancreatic panniculitis-polyarthritis (PPP) syndrome. Diffuse inflammatory myositis with fascial involvement is exceedingly rare and may mimic cellulitis, pyomyositis, septic arthritis, necrotizing fasciitis, or deep venous thrombosis, leading to diagnostic uncertainty and potentially unnecessary surgical intervention. A 44-year-old man presented with severe epigastric pain radiating to the back for 15 days, followed by fever and rapidly progressive painful swelling of the left thigh, knee, and leg. Serum lipase was elevated (867 U/L). Contrast-enhanced computed tomography (CECT) demonstrated acute necrotizing pancreatitis with <30% pancreatic necrosis, multiple acute necrotic collections, a modified CT severity index (MCTSI) of 8/10, and partial thrombosis of the splenic, superior mesenteric, and portal veins. Venous Doppler excluded deep venous thrombosis. Magnetic resonance imaging (MRI) of the thigh and knee revealed diffuse multicompartment inflammatory myositis, extensive fascial fluid tracking, diffuse subcutaneous panniculitis, and mild knee joint effusion without osteomyelitis or drainable abscess. Knee ultrasonography showed quadriceps edema with mild suprapatellar effusion. Synovial fluid analysis demonstrated a leukocyte count of only 250 cells/mm³, while blood and urine cultures remained sterile. Based on the clinicoradiological findings and exclusion of infection, a diagnosis of pancreatic enzyme-mediated lower limb myositis, fasciitis, panniculitis, and sterile reactive synovitis was made. The patient was treated conservatively with supportive care for acute pancreatitis, therapeutic anticoagulation for splanchnic venous thrombosis, analgesia, nutritional support, and physiotherapy, resulting in progressive clinical recovery without surgical intervention. This case expands the recognized musculoskeletal spectrum of acute pancreatitis by demonstrating extensive MRI-confirmed myositis, fasciitis, panniculitis, and sterile synovitis occurring concurrently with necrotizing pancreatitis and splanchnic venous thrombosis. Recognition of this rare entity is essential because it closely mimics soft tissue infection but responds to treatment directed at the underlying pancreatic disease. Multimodality imaging and careful exclusion of infective etiologies are critical to establishing the diagnosis and avoiding unnecessary operative management.
Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Pancreatitis I: Introduction
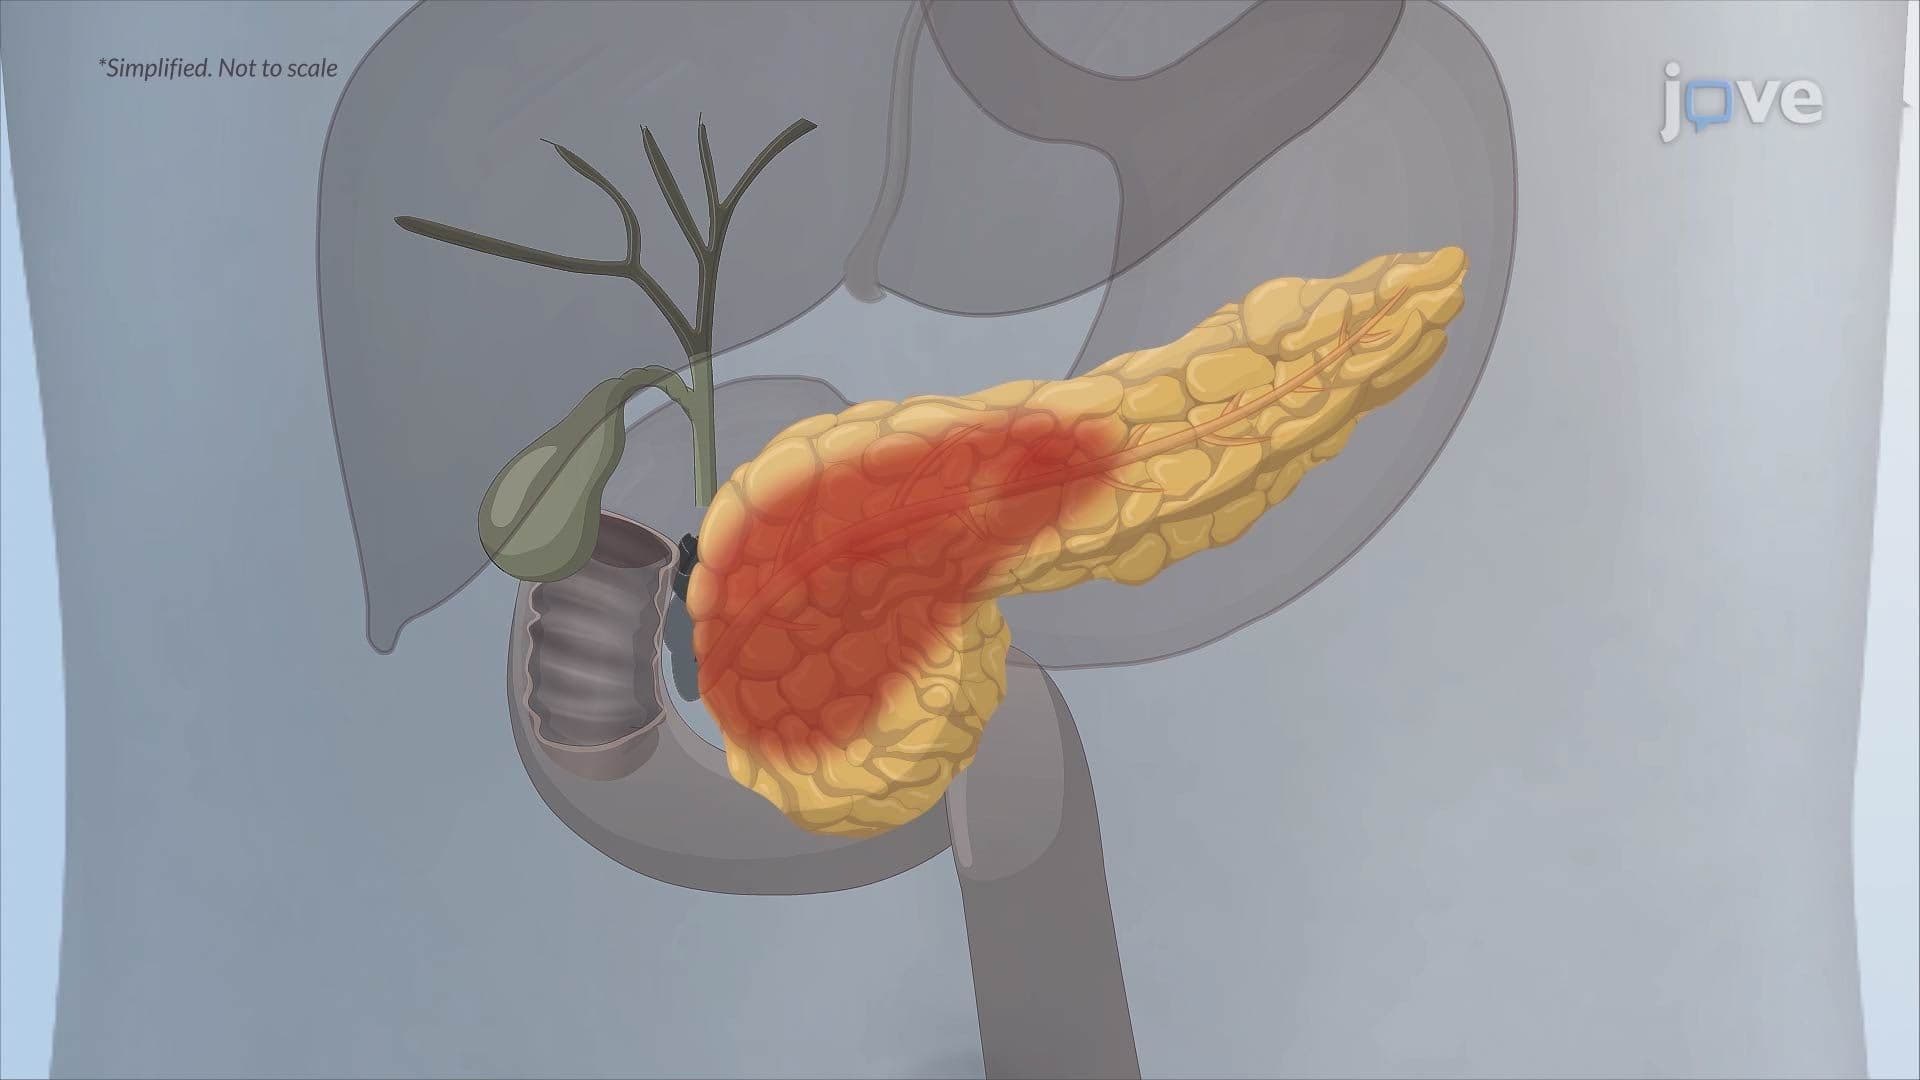
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction