Related Experiment Video
Updated: Sep 11, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Territorial inequality in oncology clinical trial participation and its ecological association with cancer mortality
Antonio David Lázaro-Sánchez1, Mahsa Fayaz Dastgerdi2, Alvaro Rodríguez-Lescure3
1Hospital Clínico Universitario Virgen de la Arrixaca, IMIB-Arrixaca, Murcia, Spain.

Background:
Spain's universal health system is delivered by 17 decentralised Autonomous Communities. We quantified territorial inequality in oncology trial-participation density and its ecological association with cancer mortality.
Methods:
In this longitudinal ecological study of the 17 regions, trial-participation density (participants actually enrolled per 100,000 population, 2016-2020) came from the Spanish Registry of Clinical Studies, allocated to the recruiting site's region; annual age-standardised cancer mortality (2015-2024) came from the National Statistics Institute. Inequality was summarised by the coefficient of variation; repeated-measures models included year indicators and region-clustered standard errors; with 17 clusters, wild cluster bootstrap and randomization inference were prespecified as primary. Sensitivity analyses addressed ageing, population weighting, gross domestic product, post-exposure years, leave-one-region-out and a negative control.
Results:
Density ranged from 0.2 to 41.9 per 100,000 (coefficient of variation 70.2%), whereas cancer mortality varied far less (5.1%). A 10-unit higher density was associated with 6.6 fewer cancer deaths (95% CI -12.0 to -1.3; cluster p = 0.019), but the randomization p-value was 0.039, and the ageing-adjusted estimate -5.5 (randomization p = 0.079). The association attenuated after adjustment for gross domestic product (-4.7; p = 0.332) and, at region level, after excluding Madrid (-0.22) - the only one of 17 leave-one-region-out fits compatible with the null. Mortality was already ordered by participation tertile in 2015, the low-to-high gap narrowing from 13.4 to 10.8 by 2024. Pre-exposure cardiovascular mortality showed an association of the same standardised magnitude.
Conclusions:
Oncology trial participation in Spain is markedly concentrated in a few Autonomous Communities; this descriptive inequality is the robust finding. The mortality association was not robust to conservative inference, to adjustment for regional scale or to exclusion of Madrid, preceded the exposure window, and was mirrored by a negative control. It is best regarded as exploratory and as a marker of health-system performance.
Related Concept Videos
 01:21
Cancer Survival Analysis
 01:20
Comparing the Survival Analysis of Two or More Groups
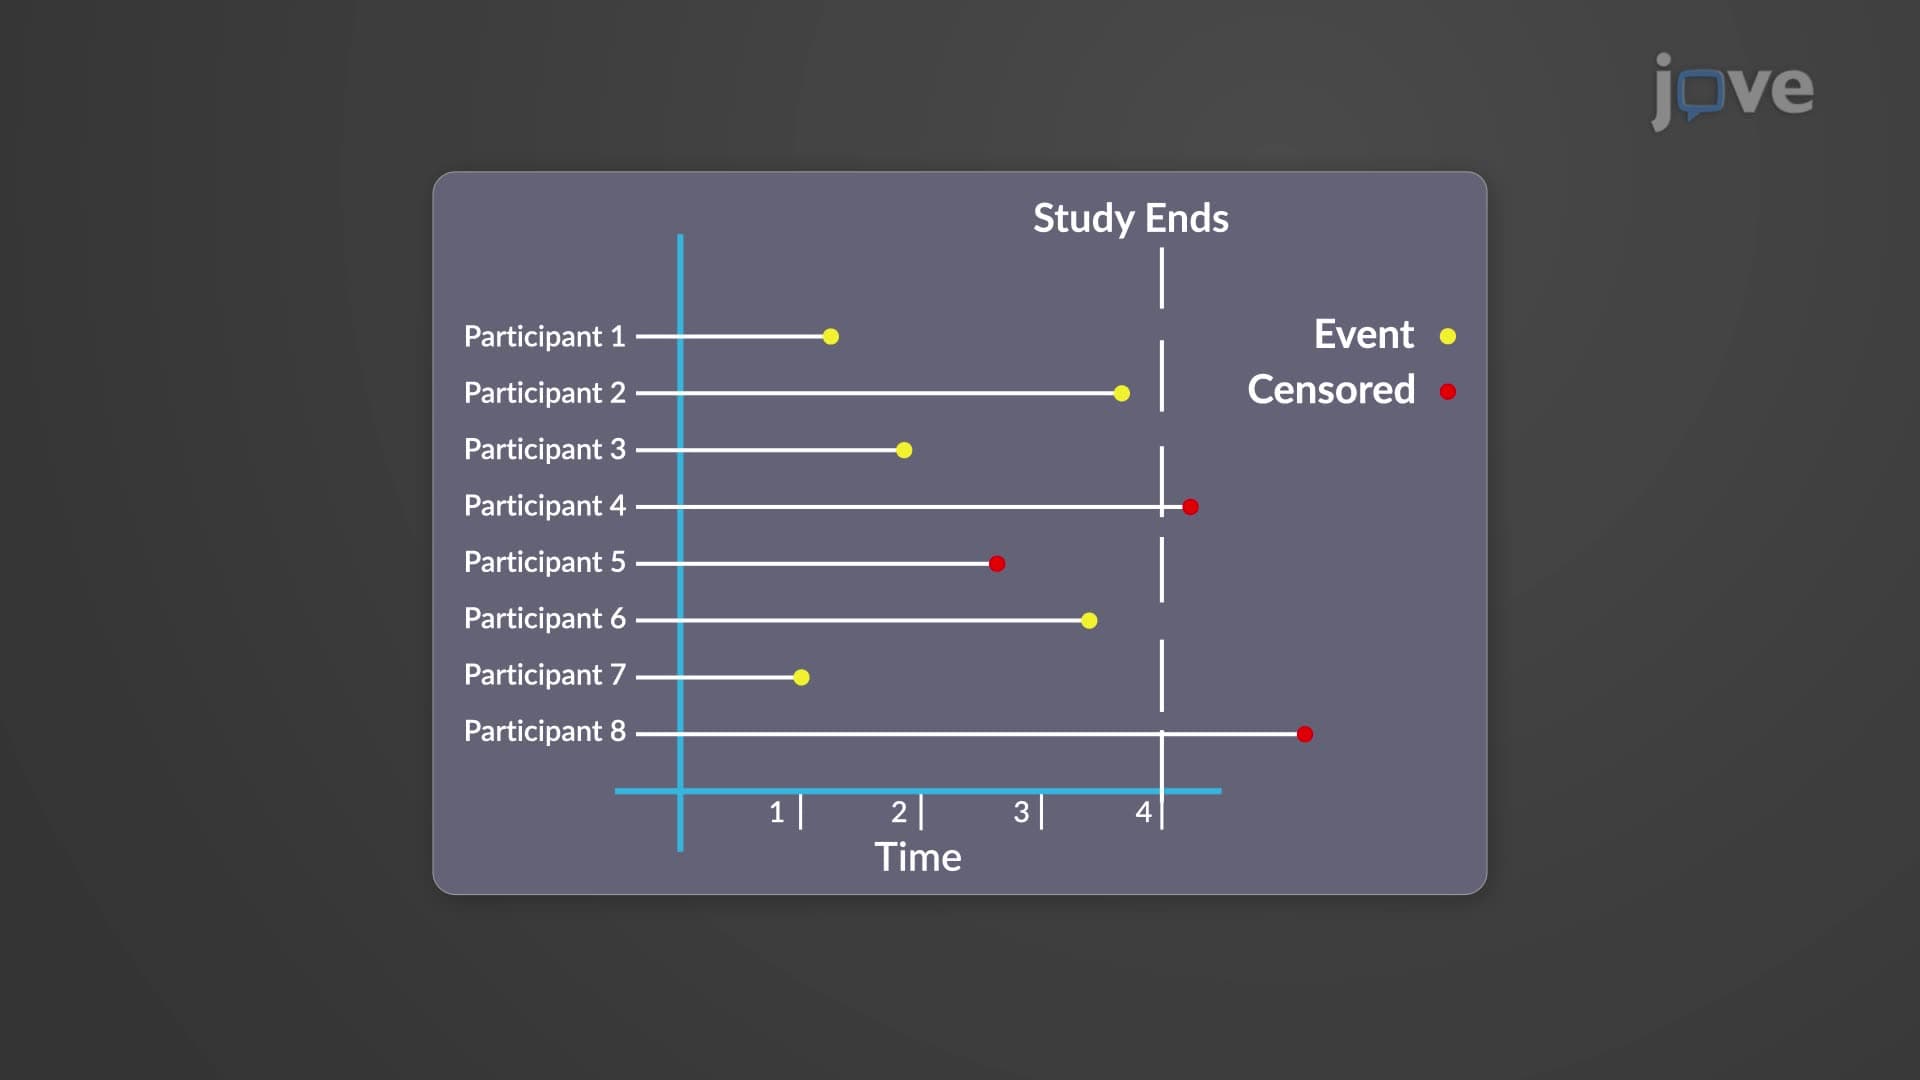 01:19
The Mantel-Cox Log-Rank Test