Related Experiment Video
Updated: Sep 11, 2026
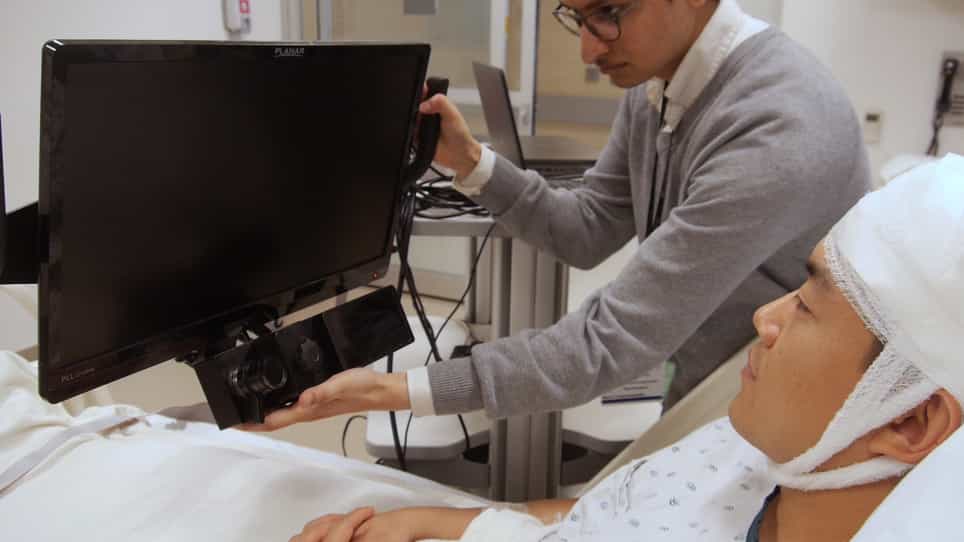

Simultaneous Eye Tracking and Single-Neuron Recordings in Human Epilepsy Patients
Published on: June 17, 2019
Continuous Eye Movement Monitoring via Superior Orbital Fissure Electrode Placement in Orbital and Cranio-orbital
Ken Matsushima1, Kyosuke Matsunaga1, Nobuyuki Nakajima1
1Department of Neurosurgery, Tokyo Medical University.

Abstract:
Orbital and cranio-orbital lesions are often benign, but postoperative ocular misalignment or diplopia can impair the quality of life. Eye movement monitoring has mainly been used for intermittent mapping for localization; however, serial, stimulus-evoked surveillance with prompt alerts remains challenging. We report an initial consecutive case series evaluating feasibility, safety, and early outcomes of continuous, stimulus-evoked electro-oculography monitoring using repetitive direct stimulation through an electrode placed adjacent to the superior orbital fissure. We retrospectively reviewed 17 consecutive orbital and cranio-orbital lesion surgeries over 2 years. Continuous electro-oculography monitoring was attempted when superior orbital fissure access was allowed, using periocular recording electrodes and serial stimulation (typically 1 Hz) via a superior orbital fissure-adjacent stimulating electrode. Outcomes were assessed preoperatively and 3-9 months postoperatively, focusing on ocular motility deficits, diplopia, perioperative adverse events, and monitoring-related complications. Continuous electro-oculography monitoring was implemented in 9/17 cases (53%) and was feasible in all monitored cases, providing serial responses throughout lesion resection. Non-implementation reflected lack of superior orbital fissure access in endoscopic transnasal procedures (n = 5) or a supraorbital keyhole approach (n = 1), clinical non-necessity (n = 1), or absent evoked responses with complete preoperative palsy (n = 1). No trigeminocardiac reflex events or monitoring-related complications occurred. The exploratory final amplitude preservation ratio was ≥50% in all monitored cases. No monitored patient had postoperative worsening of ocular motility (0/9) or diplopia; one non-monitored patient experienced mild recurrent diplopia, improving on follow-up. Continuous superior orbital fissure-adjacent stimulation-evoked electro-oculography monitoring was feasible and safe when superior orbital fissure access was obtained and it provided serial eye movement surveillance signals in this initial consecutive case series.

