Related Experiment Video
Updated: Sep 11, 2026
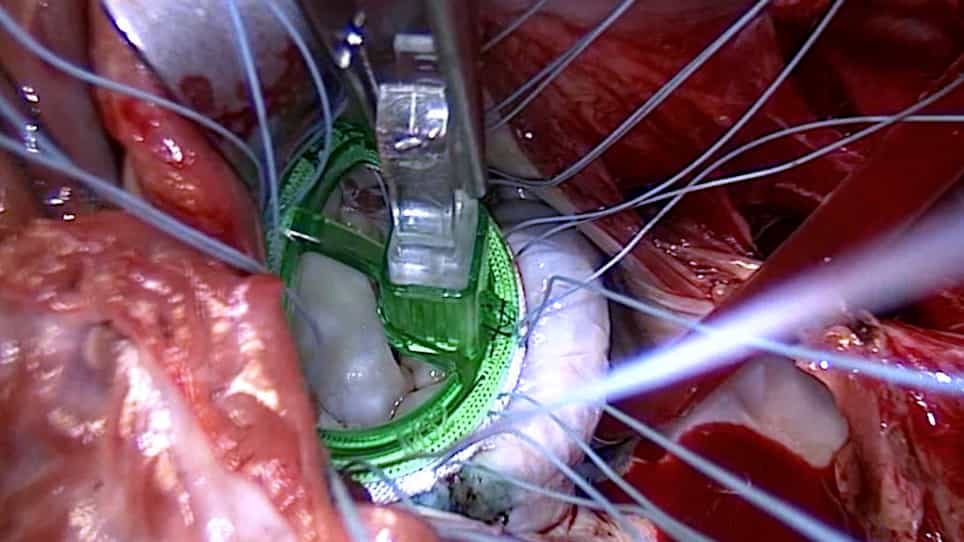
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
TRI-SCORE based risk stratification across contemporary treatment strategies for isolated tricuspid regurgitation: a
Sara Gharehdaghi1,2, Liesbeth Rosseel1, Monika Beles1
1Cardiovascular Center, AZORG Hospital, Aalst, Belgium.

Background:
The TRI-SCORE is a disease-specific risk model developed to predict outcomes after isolated tricuspid valve surgery. Although its prognostic value has been demonstrated across contemporary treatment strategies, independent external validation in multicenter cohorts across a broader clinical and etiological spectrum remains limited. We evaluated the prognostic performance of the TRI-SCORE in patients with isolated ≥ moderate tricuspid regurgitation (TR) treated with medical therapy, surgery, or transcatheter tricuspid edge-to-edge repair (T-TEER).
Methods:
In this retrospective multicenter study, 104 patients with isolated ≥ moderate TR treated between 2010 and 2024 were included. Patients underwent medical therapy (n = 31), isolated tricuspid valve surgery (n = 40), or T-TEER (n = 33). The primary endpoint was all-cause mortality, and the secondary endpoint was a composite of all-cause mortality or heart failure hospitalization. Multivariable Cox proportional hazards models included TRI-SCORE and selected clinically relevant covariates.
Results:
The median age was 77.0 years (IQR, 69.8-83.0), 62% of patients were women, and the median follow-up was 45 months (IQR, 27-63). During follow-up, all-cause mortality occurred in 37 (36%), and the composite endpoint in 40 (38%). One-year all-cause mortality increased across TRI-SCORE categories (7%, 13%, and 33% in the low-, intermediate-, and high-risk groups, respectively; P = 0.03). Baseline TRI-SCORE independently predicted all-cause mortality (HR 1.23; 95% CI 1.08-1.40) and the composite endpoint (HR 1.34; 95% CI 1.17-1.52). At 1 year, TR was reduced to < moderate severity in 60% of medically treated patients, 91% of surgically treated patients, and 68% of T-TEER-treated patients. Although surgery was associated with a lower risk of the composite endpoint (HR 0.39; 95% CI 0.17-0.89), Kaplan-Meier analysis showed no significant survival difference among treatment groups.
Conclusions:
In this multicenter real-world cohort of patients with isolated ≥ moderate TR, the TRI-SCORE provided independent prognostic information across medical therapy, surgery, and T-TEER. These findings provide external validation of the TRI-SCORE in a multicenter cohort representing a broader clinical and etiological spectrum than previously evaluated, supporting its use for baseline risk stratification across contemporary management strategies. Treatment comparisons should be interpreted cautiously because of the observational study design.
Related Concept Videos
 01:25
Mitral Regurgitation III: Medical Management
 01:25
Aortic Regurgitation III: Medical Management
 01:26
Mitral Stenosis III: Medical Management
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:20
Mitral Regurgitation I: Introduction