Related Experiment Video
Updated: Sep 12, 2026

Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Association between early body temperature dynamic trajectory and mortality and infection rates for patients with
Li Liu1, Bowen Li2, Shuhang Wang1
1Tianjin Medical University General Hospital, Tianjin, China.

Background:
In-hospital cardiac arrest (IHCA) is a common critical event with poor prognosis. Targeted temperature management (TTM) is the only approved therapy for cerebral ischemia post-cardiac arrest (CA). Body temperature (BT) is a key physiological indicator, but the dynamic evolution of BT is usually neglected, which may be closely associated with patient outcomes. This study aimed to investigate the dynamic BT trajectories within the first 72 hours after ICU admission in CA patients, identify distinct BT trajectory subphenotypes, and evaluate their associations with mortality and infection risk.
Methods:
A retrospective study was conducted using data from the Medical Information Mart for Intensive Care IV (MIMIC-IV) database and the eICU Collaborative Research Database (eICU-CRD), including 3,052 intensive care unit (ICU) CA patients. The time-series k-means algorithm combined with dynamic time warping (DTW) was used to cluster dynamic BT trajectories within the first 72 hours of ICU admission, identifying subphenotypes. To evaluate the association between BT trajectory subphenotypes and mortality, this study employed Kaplan-Meier analysis, Cox regression and logistic regression models, and sensitivity and subgroup analyses. The tabular prior-data fitted network (TabPFN) was used to construct prediction models for mortality and underwent external validation. Infection status was also compared across subphenotypes.
Results:
Four BT trajectory subphenotypes were identified, including "hyperthermia", "normothermia", "hypothermic, slow rise" (HSR), and "normothermic, rapid decline" (NRD). The NRD subphenotype had the highest in-hospital, 7-day, 28-day, and 180-day mortality rates, which remained robust across multiple models. There was no significant difference in infection incidence among subphenotypes, but pathogen distribution varied slightly. The TabPFN models showed excellent performance in predicting mortality, with the area under the receiver operating characteristic curve (AUC) values ranging from 0.840 [95% confidence interval (CI): 0.688-0.979] to 0.991 (95% CI: 0.982-1.000). The above results remained consistent in external validation.
Conclusions:
The NRD subphenotype is significantly associated with higher mortality in ICU CA patients. Dynamic BT trajectories can provide insights for personalized clinical management and timely intervention in ICU patients with CA.
Related Concept Videos
 01:19
Assessing Body Temperature - Temporal Artery
Step 1: Perform hand hygiene and don a fresh pair of gloves to prevent cross-infection and ensure patient safety.
Step 2: Explain the procedure to the patient to establish trust. Clear communication establishes trust with the patient, ensures they understand what to expect, promotes cooperation, and enhances comfort during the procedure.
Step 3: Assess the patient's forehead...
 01:28
Factors Affecting Body Temperature
Factors may include:
 01:29
Decreased Body Temperature
 01:14
Assessing Body Temperature - Axilla
Step 1: Perform hand hygiene and put on clean gloves to maintain infection control and prevent cross-contamination.
Step 2: Prepare the patient by explaining the procedure to ensure understanding and cooperation. Ensure privacy, expose the axilla, and inform the patient that minimal movement is crucial for an accurate reading.
Step 3: Adjust the patient’s clothing to expose only the axilla. It minimizes...
 01:27
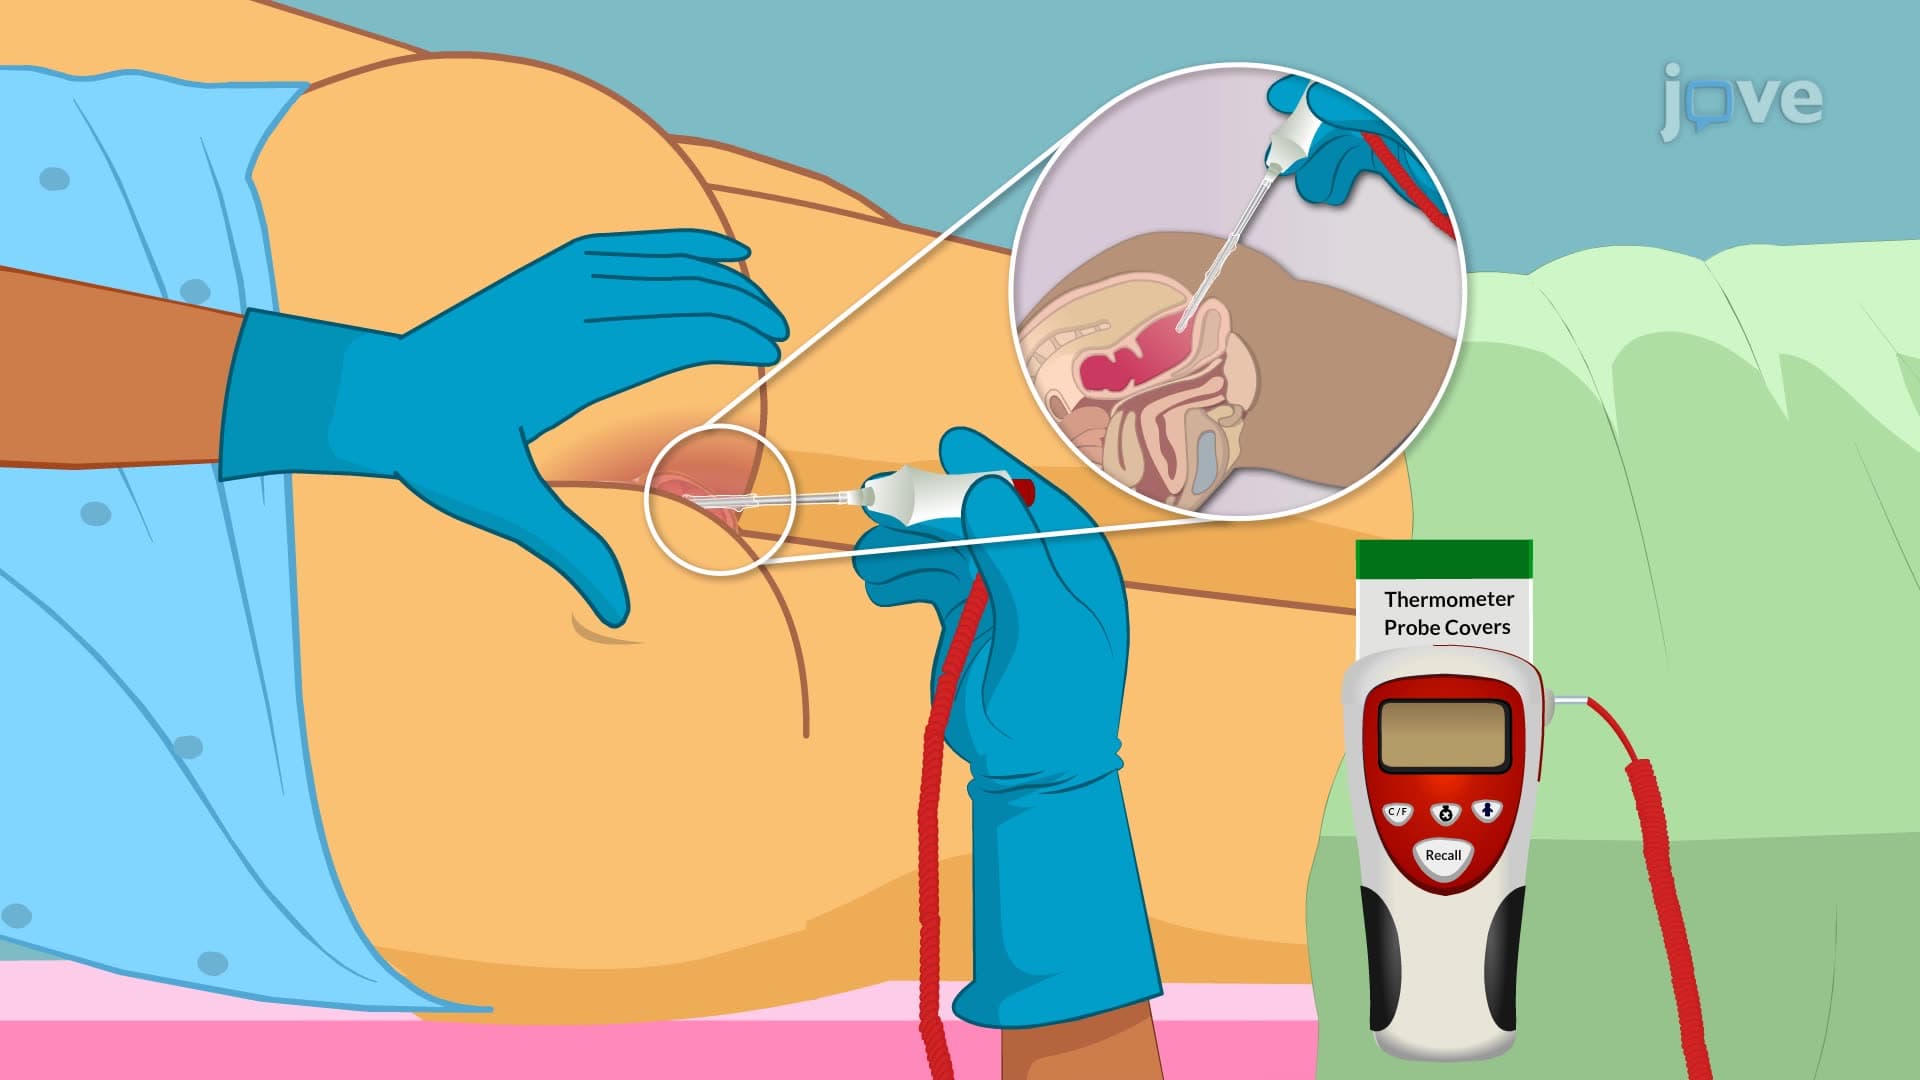
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:25
Increased Body Temperature