Related Experiment Video
Updated: Sep 13, 2026
Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Concurrent Long Thoracic and Lateral Cutaneous Intercostal Nerve Entrapment After Chest Tube Thoracostomy Causing
Yonghyun Yoon1,2,3,4, King Hei Stanley Lam4,5,6,7, Daniel Chiung-Jui Su4,8,9
1Hallym University College of Medicine, Chuncheon-si, Republic of Korea.

Background:
Chest tube thoracostomy may cause iatrogenic nerve injury, resulting in persistent pain and functional impairment. Long thoracic nerve (LTN) palsy after chest tube placement has been described, but concurrent involvement of the LTN and the lateral cutaneous branch of an intercostal nerve (LCIN) appears to be rarely reported. We describe a patient with persistent post-thoracostomy chest wall pain and scapular winging in whom musculoskeletal ultrasonography identified entrapment of both nerves.
Case Presentation:
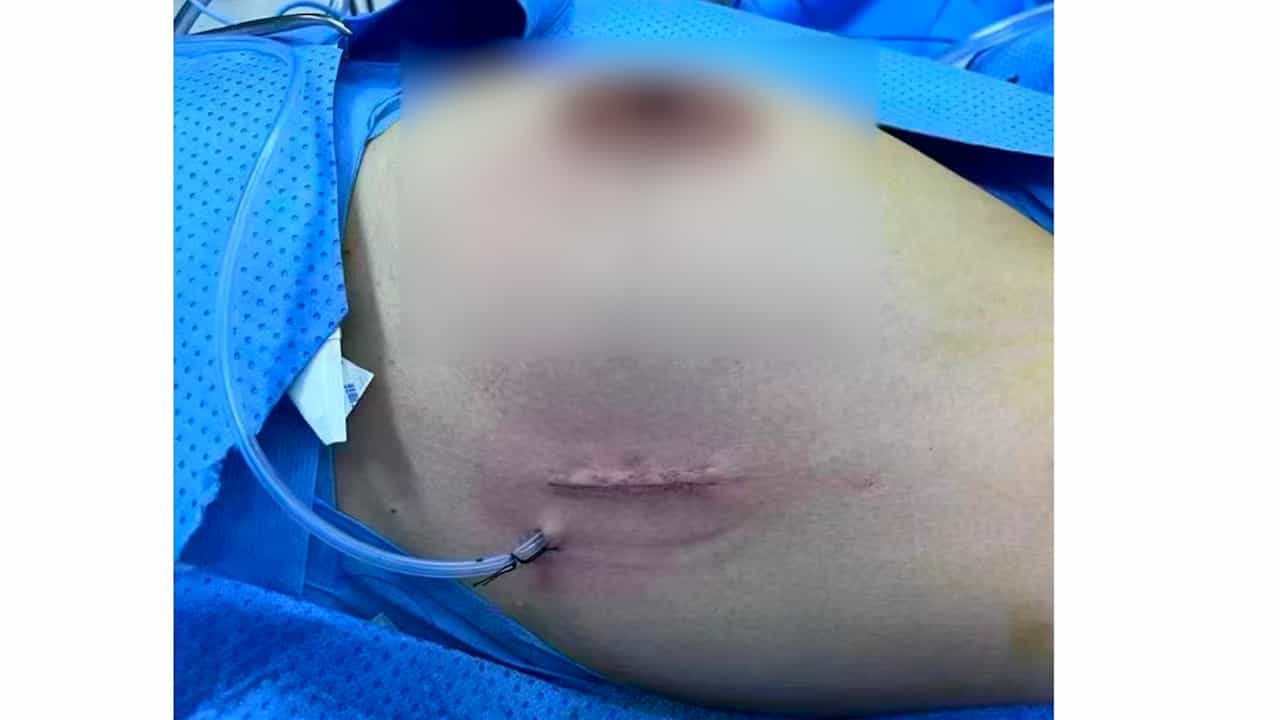
A 43-year-old man presented with severe left shoulder and chest wall pain 6 months after chest tube placement for traumatic hemopneumothorax. Examination demonstrated focal tenderness, dysesthesia, and mechanical allodynia at the chest tube scar, along with medial/inferior scapular winging during serratus anterior provocative testing. Shoulder range of motion was full on examination; however, forward flexion beyond 15° markedly aggravated pain, resulting in pain-related reluctance to move the shoulder. Manual muscle testing was 4+/5 before treatment because pain limited force generation. Musculoskeletal ultrasound demonstrated focal abnormality of the LTN where it pierced the axillary fascia over the sixth rib, with loss of fascicular definition and reduced glide, and tethering/thickening of the LCIN within scar tissue at the prior tube insertion site. Symptom reproduction with sonopalpation supported the clinical relevance of both findings.
Intervention And Results:
Ultrasound-guided hydrodissection using 5% dextrose in water was performed around both nerves. A total of approximately 40 mL of 5% dextrose in water was used, with 20 mL administered per nerve. Immediately after the first procedure, pain improved from NRS 9/10 to 2/10, with marked reduction in pain during shoulder movement, including forward flexion. The patient subsequently underwent 5 treatment sessions at 2-week intervals over 10 weeks. During follow-up, manual muscle testing improved to 5/5 without pain, scapular winging was no longer evident on provocative testing, and the Shoulder Pain and Disability Index improved from pain/disability scores of 25/15 to 6/4. At the sixth follow-up visit, pain and function were satisfactory, and the patient elected continued monitoring without further intervention. At 1-year follow-up, treatment efficacy remained sustained without recurrence.
Conclusion:
In patients with persistent shoulder or chest wall pain after chest tube thoracostomy, iatrogenic peripheral nerve entrapment should be considered. This case highlights the value of a focused neuromuscular examination and musculoskeletal ultrasound for identifying concurrent motor and sensory nerve involvement and suggests that ultrasound-guided hydrodissection may be a useful minimally invasive treatment. Because electrodiagnostic studies were not performed, the findings are most consistent with entrapment/neurapraxia with dynamic tethering rather than electrodiagnostically proven axonal palsy.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...